Related Experiment Video
Updated: Sep 30, 2025
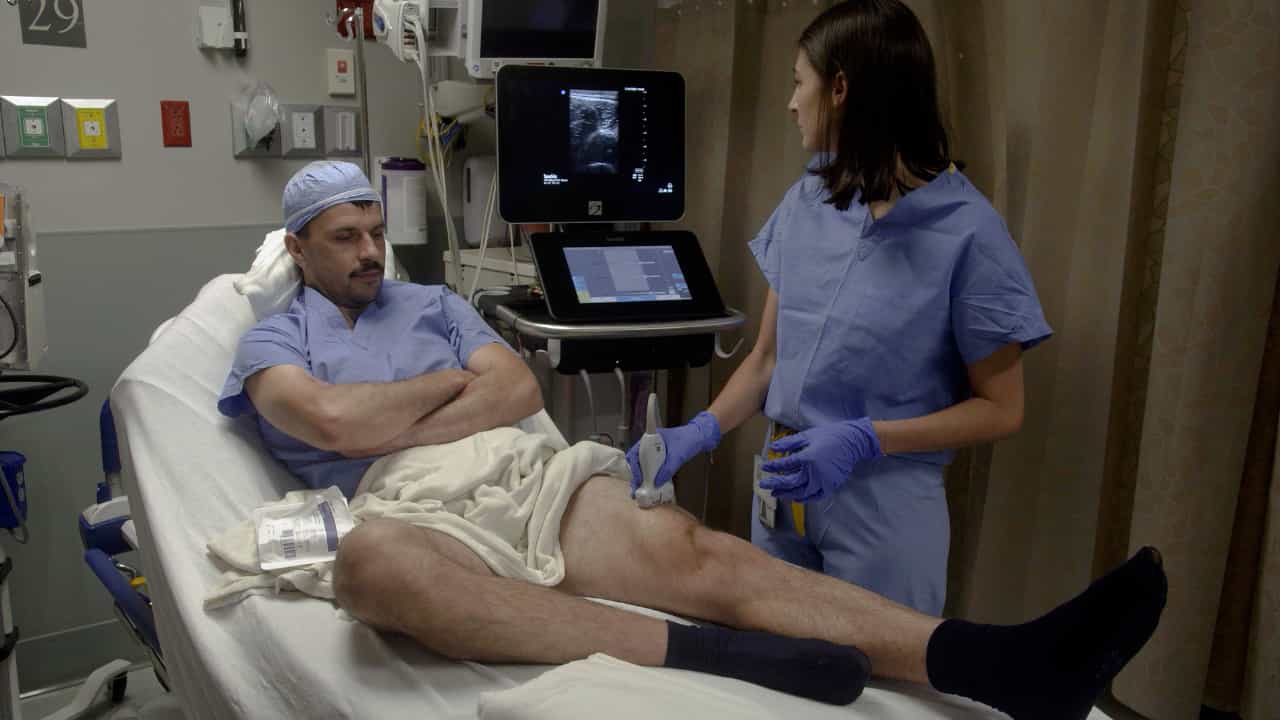

Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
The Geriatric Nutritional Risk Index as a predictor of complications in geriatric trauma patients
Heather R Kregel1, Patrick B Murphy, Mina Attia
1From the Division of Acute Care Surgery, Department of Surgery (H.R.K., M.A., D.E.M., E.C.O., S.D.A., C.E.W., J.A.H., L.S.K., T.J.P.), and Center for Surgical Trials and Evidence-based Practice (H.R.K., M.A., D.E.M., S.D.A., J.A.H., L.S.K., T.J.P.), McGovern Medical School at UTHealth; Center for Translational Injury Research (H.R.K., D.E.M., S.D.A., C.E.W., J.A.H., L.S.K., T.J.P.), Houston, Texas; and Department of Surgery (P.B.M., R.S.M.), Medical College of Wisconsin, Milwaukee, Wisconsin.

Background:
Malnutrition is associated with increased morbidity and mortality after trauma. The Geriatric Nutritional Risk Index (GNRI) is a validated scoring system used to predict the risk of complications related to malnutrition in nontrauma patients. We hypothesized that GNRI is predictive of worse outcomes in geriatric trauma patients.
Methods:
This was a single-center retrospective study of trauma patients 65 years or older admitted in 2019. Geriatric Nutritional Risk Index was calculated based on admission albumin level and ratio of actual body weight to ideal body weight. Groups were defined as major risk (GNRI <82), moderate risk (GNRI 82-91), low risk (GNRI 92-98), and no risk (GNRI >98). The primary outcome was mortality. Secondary outcomes included ventilator days, intensive care unit length of stay (LOS), hospital LOS, discharge home, sepsis, pneumonia, and acute respiratory distress syndrome. Bivariate and multivariable logistic regression analyses were performed to determine the association between GNRI risk category and outcomes.
Results:
A total of 513 patients were identified for analysis. Median age was 78 years (71-86 years); 24 patients (4.7%) were identified as major risk, 66 (12.9%) as moderate risk, 72 (14%) as low risk, and 351 (68.4%) as no risk. Injury Severity Scores and Charlson Comorbidity Indexes were similar between all groups. Patients in the no risk group had decreased rates of death, and after adjusting for Injury Severity Score, age, and Charlson Comorbidity Index, the no risk group had decreased odds of death (odds ratio, 0.13; 95% confidence interval, 0.04-0.41) compared with the major risk group. The no risk group also had fewer infectious complications including sepsis and pneumonia, and shorter hospital LOS and were more likely to be discharged home.
Conclusions:
Major GNRI risk is associated with increased mortality and infectious complications in geriatric trauma patients. Further studies should target interventional strategies for those at highest risk based on GNRI.
Level Of Evidence:
Prognostic and Epidemiologic; Level III.

Related Concept Videos
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:24
Nephrotic Syndrome I : Introduction
 01:27
Urinary Tract Calculi IV: Nutrition Therapy and Prevention
 01:30
Inflammatory Bowel Disease III: Diagnostic Studies and Management I-Nutritional Therapy
Diagnostic studies
A colonoscopy is the definitive screening test, distinguishing ulcerative colitis from other colon diseases with similar symptoms. During a colonoscopy test, inflamed mucosa with exudate ulcerations can be observed, and biopsies are taken to determine the histologic characteristics of the...
 01:26
Enteral Nutrition I: Orogastric and Nasogastric Feeding
Orogastric (OG) and nasogastric (NG) feeding are two standard methods used for enteral nutrition. Enteral nutrition is often preferred over...