Related Experiment Video
Updated: Sep 23, 2025
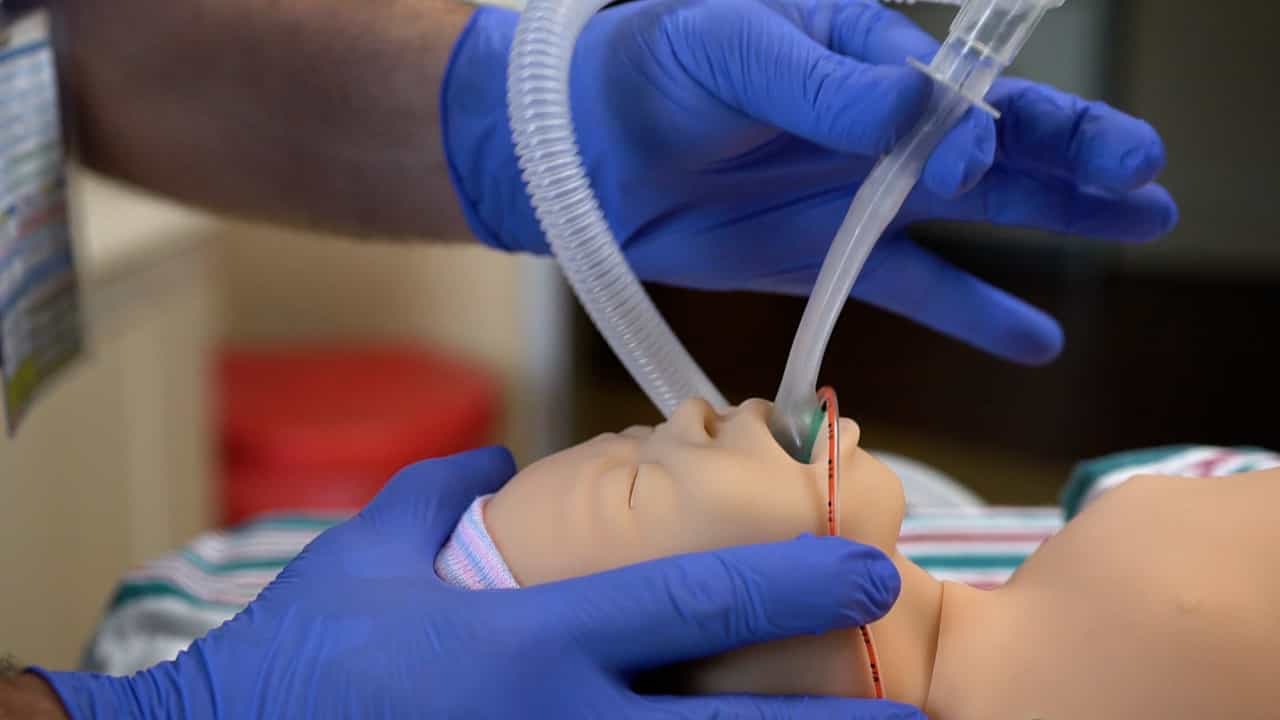

Laryngeal Mask Airway LMA Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway SGA
Published on: July 14, 2023
Supraglottic Airway Device to Improve Ventilation Success and Reduce Pulmonary Aspiration during Cardio-Pulmonary
N Segond1,2, A Bellier2,3, H Duhem1,2
1Emergency Department and Mobile Intensive Care Unit, University Hospital of Grenoble Alpes, Grenoble, France.

Objectives:
Early airway management during cardiopulmonary resuscitation (CPR) prevents aspiration of gastric contents. Endotracheal intubation is the gold standard to protect airways, but supraglottic airway devices (SGA) may provide some protection with less training. Bag-mask ventilation (BMV) is the most common method used by rescuers. We hypothesized that SGA use by first rescuers during CPR could increase ventilation success rate and also decrease intragastric pressure and pulmonary aspiration.
Methods:
We performed a randomized cross-over experimental trial on human cadavers. Protocol A: we assessed the rate of successful ventilation (chest rise), intragastric pressure, and CPR key time metrics. Protocol B: cadaver stomachs were randomized to be filled with 300 mL of either blue or green serum saline solution through a Foley catheter. Each rescuer was randomly assigned to use SGA or BMV during a 5-minute standard CPR period. Then, in a crossover design, the stomach was filled with the second color solution and another 5-minute CPR period was performed using the other airway method. Pulmonary aspiration, defined as the presence of colored solution below the vocal cords, was assessed by a blinded operator using bronchoscopy. A generalized linear mixed model was used for statistical analysis.
Results:
Protocol A: Forty-eight rescuers performed CPR on 11 cadavers. Median ventilation success was higher with SGA than BMV: 75.0% (IQR: 59.8-87.3) vs. 34.7% (IQR: 25.0-50.0), (p = 0.003). Gastric pressure and differential (maximum minus minimum) gastric pressure were lower in the SGA group: 2.21 mmHg (IQR: 1.66; 2.68) vs. 3.02 mmHg (IQR: 2.02; 4.22) (p = 0.02) and 5.70 mmHg (IQR: 4.10; 7.60) vs. 8.05 mmHg (IQR: 5.40; 11.60) (p = 0.05). CPR key times were not different between groups. Protocol B: Ten cadavers were included with 20 CPR periods. Aspiration occurred in 2 (20%) SGA procedures and 5 (50%) BMV procedures (p = 0.44).
Conclusion:
Use of SGA by rescuers improved the ventilation success rate, decreased intragastric pressure, and did not affect key CPR metrics. SGA use by basic life support rescuers appears feasible and efficient.


Related Concept Videos
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...