Related Experiment Video
Updated: Sep 22, 2025


Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
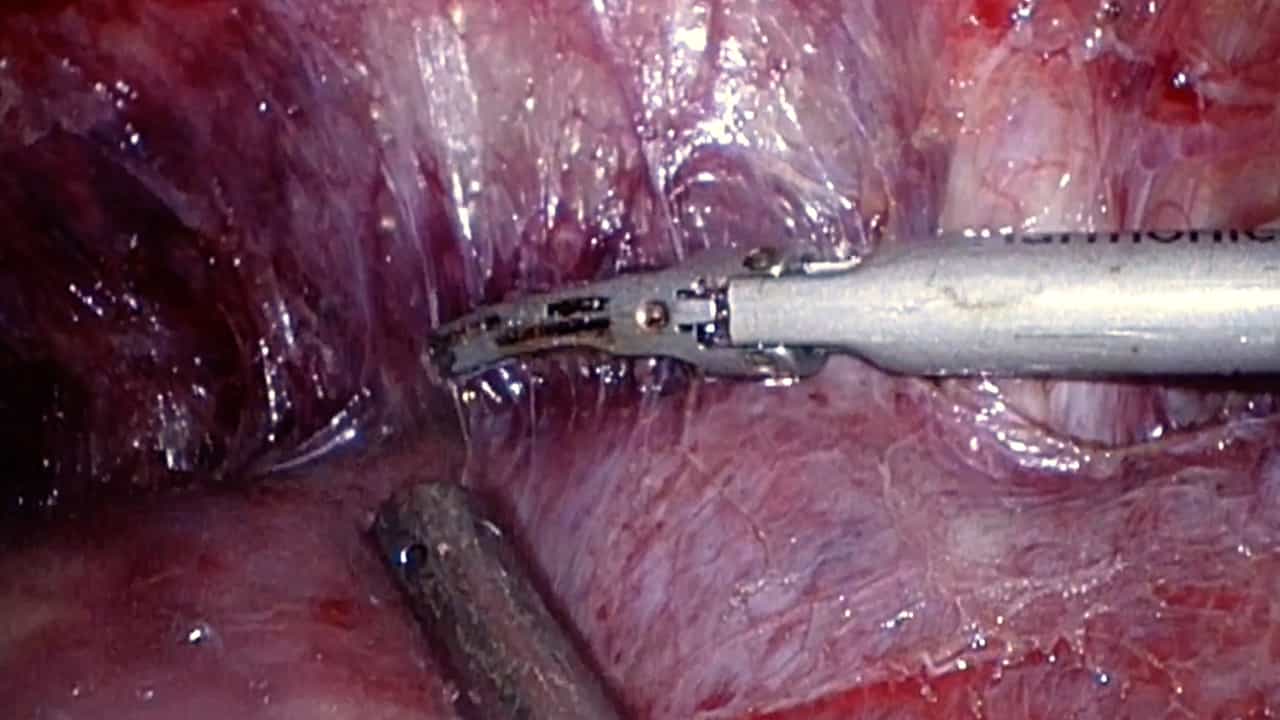
Totally laparoscopic resection of right-sided colon cancer using transvaginal specimen extraction with a 10-mm-long
A Nishimura1, M Kawahara2, Y Kawachi2
1Department of Surgery, Institute of Gastroenterology, Nagaoka Chuo General Hospital, 2041 Kawasaki-cho, Nagaoka, Niigata, 940-8653, Japan. a-west@next.odn.ne.jp.

Background:
Natural orifice specimen extraction (NOSE) has been developed as a means of decreasing the incidence of surgical wound complications. We refined the procedure for totally laparoscopic colectomy with transvaginal specimen extraction using the reduced port surgery technique with the ultimate goal of attenuating damage to the abdominal wall. We herein report this innovative technique and its short- and long-term outcomes.
Methods:
We prospectively collected data on seven patients who underwent totally laparoscopic colectomy using transvaginal specimen extraction with a 10-mm-long abdominal incision for right-sided colon cancer from January 2014 to December 2021. Two 5-mm ports were used in the procedure without laparotomy. Transverse transabdominal posterior colpotomy was then performed. We introduced a GelPOINT Mini advanced access platform (Applied Medical, Rancho Santa Margarita, CA, USA) into the transvaginal route for the insertion of a laparoscope, forceps, and stapling device. Lymph node dissection and transection of the ileum and distal colon were performed with transvaginal assistance. A specimen was then extracted transvaginally. Intracorporeal functional end-to-end anastomosis was conducted using a linear stapler through the vagina. After the removal of GelPOINT Mini, the vaginal incision was closed transvaginally.
Results:
Seven patients successfully underwent this procedure. Median operative time was 219 min (range 174-255 min), median blood loss was 23 ml (range 10-37 ml), median number of harvested lymph nodes was 21 (range 17-35 lymph nodes) and median margins were 17.0 cm (range 9.0-25.0 cm) for the proximal margin and 9.5 cm (range 5.0-13.0 cm) for the distal margin. There were no complications more severe than Clavien-Dindo Grade II and there was no mortality. The median frequency of use intravenous analgesics from postoperative day 1 to discharge was once. Two patients did not require analgesics. A node-positive patient developed recurrence at the lung and paraaortic lymph nodes.
Conclusions:
This procedure appears to be feasible, safe, and oncologically acceptable for selected cases.
More Related Videos
 03:48
Techniques of Laparoscopic Right Posterior Sectionectomy: Glissonian Approach and a Parenchymal Transection Technique
Published on: October 6, 2023
 12:45
Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022