

Not T too! False elevations in high-sensitivity cardiac troponin T (hs-TnT) following specimen transport
Heather A Paul1, Qingli Chi2, Jessica L Gifford1
1Alberta Precision Laboratories and Department of Pathology and Laboratory Medicine, University of Calgary, Calgary, Alberta, Canada.

Abstract:
Though false elevations attributed to preanalytical specimen handling have been widely reported for Troponin I (TnI), Troponin T (TnT) has appeared more robust to falsely elevated Tn. We describe reproducible false elevations in high sensitivity TnT (hs-TnT) in specimens after courier transport in plasma separator tubes (PST) off-site for testing. Hs-TnT was measured under 5 different conditions: 1) at collection location (N = 24); 2) after transport upright in racks (N = 66); 3) after transport with no control over tube agitation (N = 69); 4) on transported aliquots (N = 84); or 5) immediately after transport with no control over tube agitation (N = 16), followed by keeping the specimen upright and re-measuring at 1hr, 2hr, 4hr, and 20-24hrs (N = 6). To assess the degree of discrepancy, plasma from the original PST was aliquotted, re-centrifuged, potential debris removed, and hs-TnT re-measured. 43% of PST specimens collected offsite and transported with no control over tube agitation had clinically significant false elevations of hs-TnT which subsequently decreased following aliquotting and re-centrifugation (median decrease = 9.9 ng/L). Onsite testing or transported aliquots demonstrated no discrepancy. After being kept upright, discrepant specimens were not different from re-centrifuged aliquots by 4hrs (p = 0.6141, repeated measures ANOVA with Dunn's multiple comparisons). Clinically significant false elevations of hs-TnT occurred in approximately 40% of separated PSTs that were transported in containers where specimens are transported with no control over tube agitation. This interference does not occur if plasma is aliquoted or if hs-TnT is tested at the collection site. In order to prevent these false elevations, and their potential patient impact on the diagnosis of acute myocardial infarction, specimens for hs-TnT measurement should be aliquoted at the collection location prior to transport.
More Related Videos
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
 09:23
Using Extraordinary Optical Transmission to Quantify Cardiac Biomarkers in Human Serum
Published on: December 13, 2017
Related Concept Videos
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:26
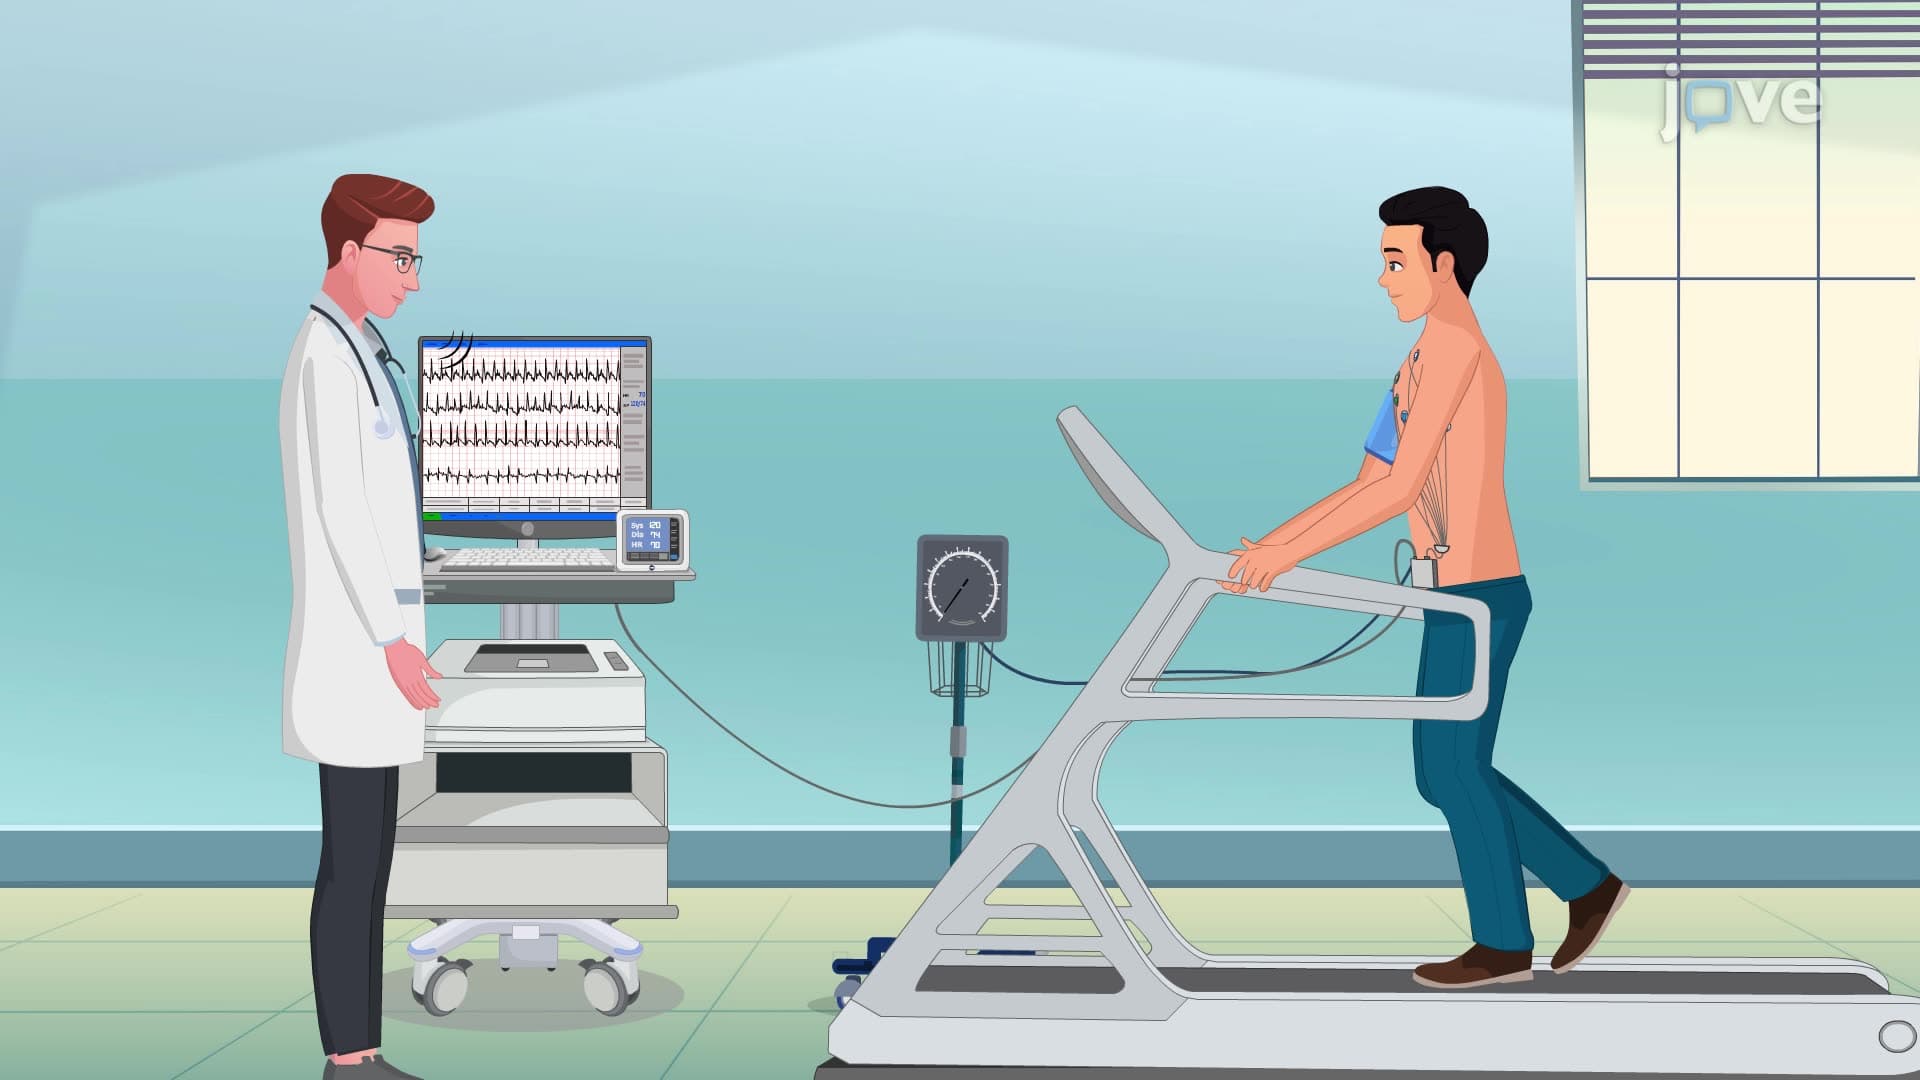
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes