

Impact of QRS Duration on Non-ST-Segment Elevation Myocardial Infarction (from a National Registry)
Saadiq M Moledina1, Fahmida Mannan2, Nicholas Weight1
1Keele Cardiovascular Research Group, Centre for Prognosis Research, Institute for Primary Care and Health Sciences, Keele University, Keele, United Kingdom; Division of Cardiology, Royal Stoke University Hospital, Staffordshire, United Kingdom.

Abstract:
QRS duration (QRSd) is ill-defined and under-researched as a prognosticator in patients with non-ST-segment myocardial infarction (NSTEMI). We analyzed 240,866 adult (≥18 years) hospitalizations with non-ST-segment elevation myocardial infarction using data from the United Kingdom Myocardial Infarction National Audit Project. Clinical characteristics and all-cause in-hospital mortality were analyzed according to QRSd, with 38,023 patients presenting with a QRSd >120 ms and 202,842 patients with a QRSd <120 ms. Patients with a QRSd >120 ms were more frequently older (median age of 79 years vs 71 years, p <0.001), and of white ethnicity (93% vs 91%, p <0.001). Patients with a QRSd <120 ms had higher frequency of use of aspirin (97% vs 95%, p <0.001), P2Y12 inhibitor (93% vs 89%, p <0.001), angiotensin-converting enzyme inhibitor/angiotensin receptor blocker (82% vs 81%, p <0.001) and β blockers (83% vs 78%, p <0.001). Invasive management strategies were more likely to be used in patients with QRSd <120 ms including invasive coronary angiography (72% vs 54%, p <0.001), percutaneous coronary intervention (46% vs 33%, p <0.001) and coronary artery bypass graft surgery (8% vs 6%, p <0.001). In a propensity score matching analysis, there were no differences between the 2 groups in the adjusted rates of in-hospital all-cause mortality (odds ratio 0.94, 95% confidence interval 0.86 to 1.01) or major adverse cardiac events (odds ratio 0.94, 95% confidence interval 0.85 to 1.02) during the index admission. In conclusion, prolonged QRSd >120 ms in the context of non-ST-segment myocardial infarction is not associated with worse in-hospital mortality or the outcomes of major adverse cardiac events.
More Related Videos
 05:41
Left Anterior Descending Coronary Artery Ligation for Ischemia-Reperfusion Research: Model Improvement via Technical Modifications and Quality Control
Published on: December 16, 2022
 09:23
Confirmation of Myocardial Ischemia and Reperfusion Injury in Mice Using Surface Pad Electrocardiography
Published on: November 24, 2016
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:29
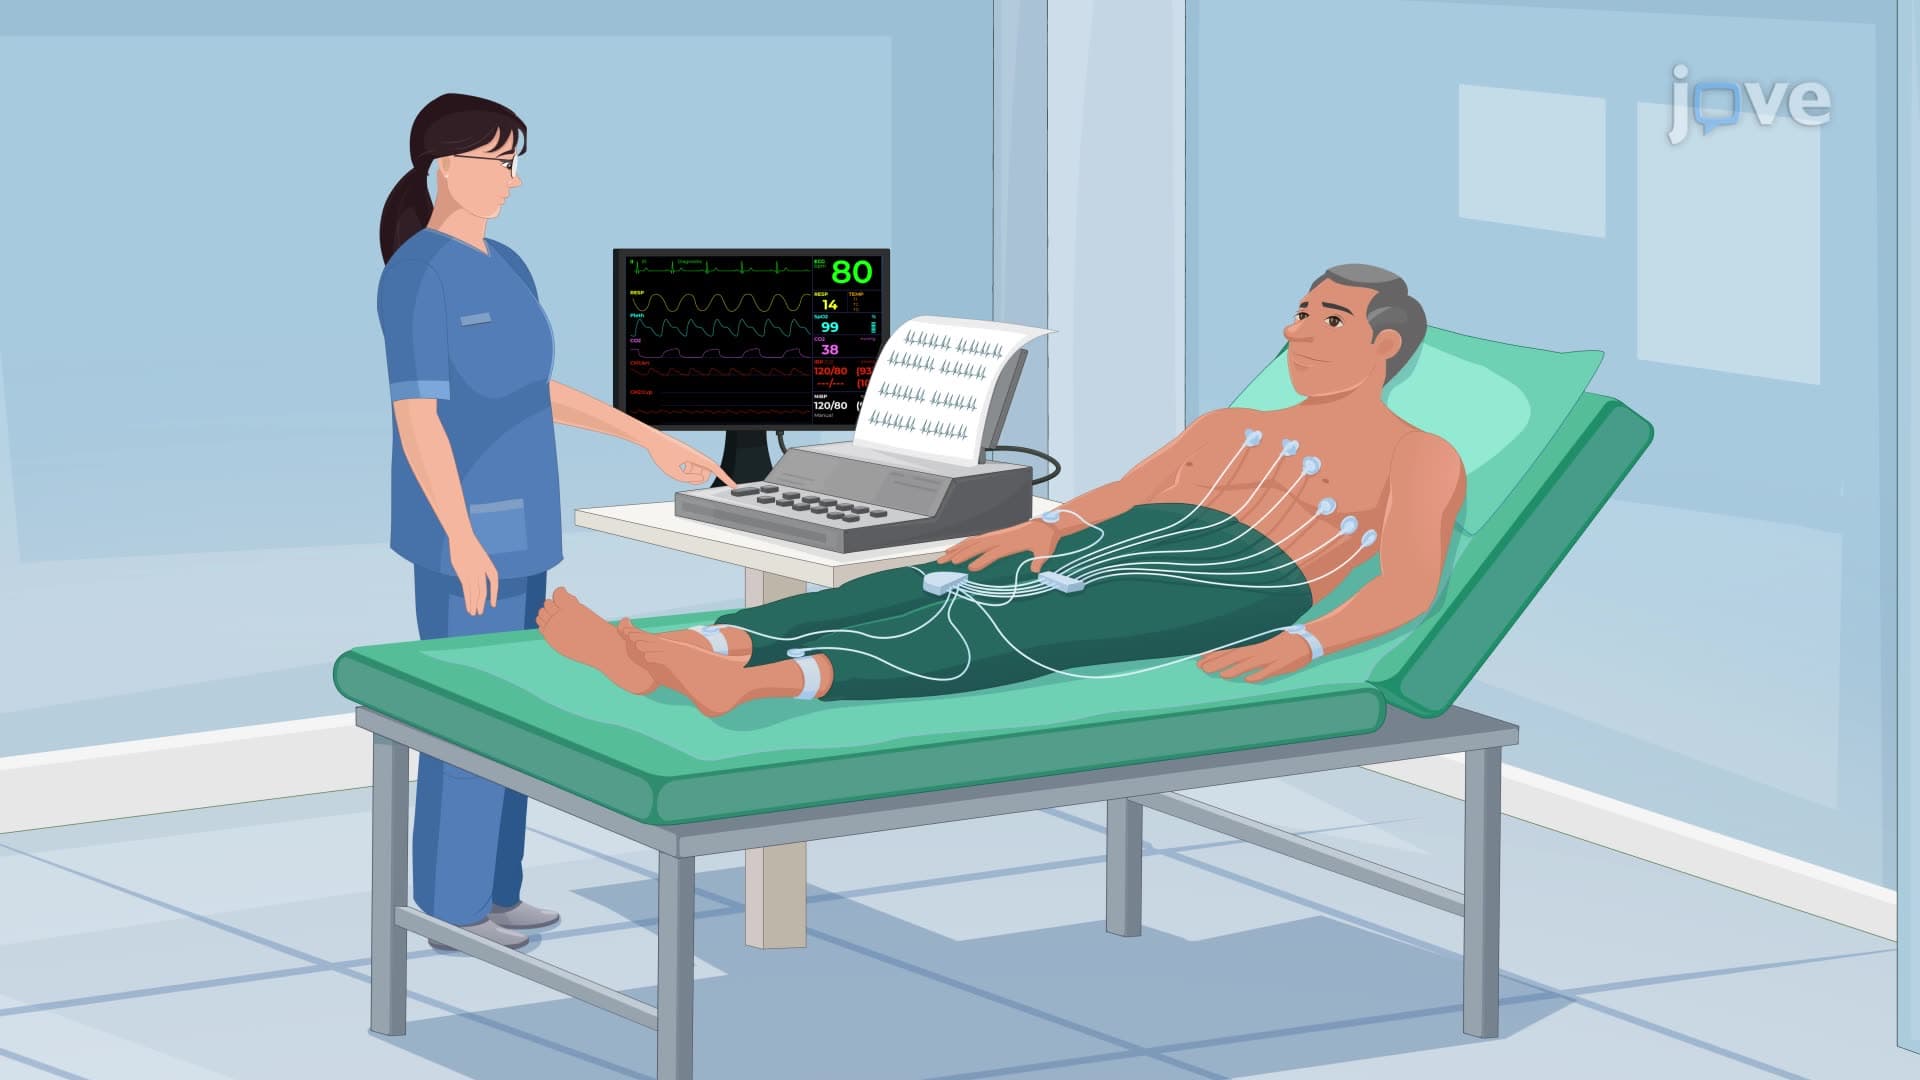
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and...
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:24
ECG Interpretation of Rhythms
Components of the Electrocardiogram
The primary components of a normal ECG waveform in Normal sinus rhythm(NSR) include the P wave, PR interval, QRS complex, ST segment, T wave, and occasionally a U wave.
ECG waveforms are divided by vertical and horizontal lines at standard intervals.
The horizontal axis measures time and rate, and the vertical axis measures amplitude or voltage....
 01:17
Ischemic Heart Disease: Overview
Atherosclerosis, the primary malefactor, orchestrates this dangerous condition. It manifests as the accumulation of fatty deposits, akin to insidious plaques, within arterial walls. As time elapses, these plaques metamorphose, hardening and...