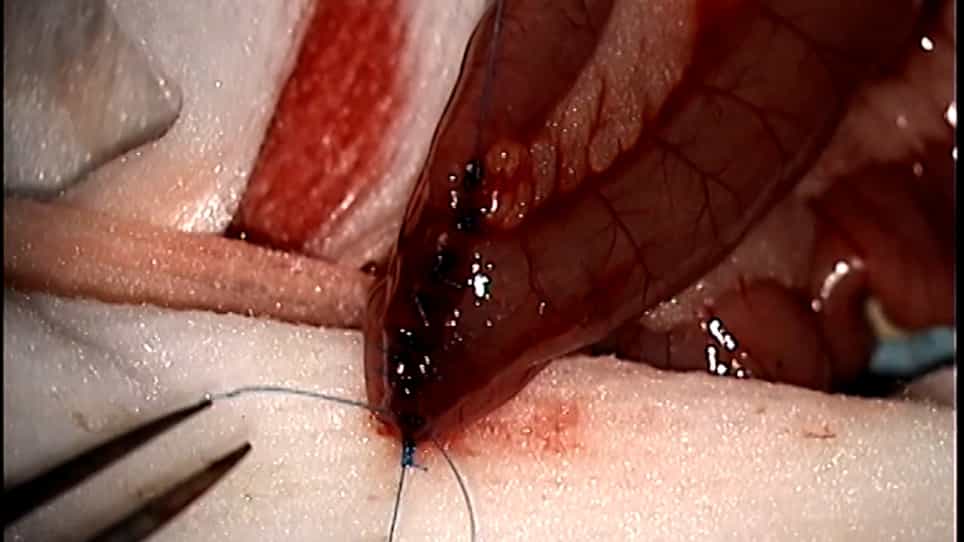
Related Experiment Video
Updated: Aug 24, 2025


One-anastomosis Gastric Bypass OAGB in Rats
Published on: November 10, 2018
Distal gastric bypass revision for weight recurrence or nonresponse to primary procedure: initial experience and
Bhavani Pokala1,2, Spyridon Giannopoulos1, Dimitrios I Athanasiadis1
1Department of Surgery, Indiana University School of Medicine, 545 Emerson Hall, EH 130, Indianapolis, IN, 46202, USA.

Background:
Considerable weight recurrence (WR) after Roux-en-Y gastric bypass (RYGB) may occur in nearly 20% of patients. While several nonoperative, endoscopic, and surgical interventions exist for this population, the optimal approach is unknown. This study reports our initial experience with distal bypass revision (DGB) and provides a comparison with patients after primary RYGB.
Methods:
Single-institution, retrospective review was conducted for patients who underwent DGB from 2018 to 2020. A Roux and common channel of 150 cm each were constructed (total alimentary limb 300 cm). A group of primary RYGB patients with similar demographics were selected as controls. Demographics, comorbidity resolution, surgical technique, complications, excess weight loss (EWL), total weight loss (TWL), BMI, and weight change data were compared. Patient postoperative weight loss (WL) was also compared after their primary and DGB operations.
Results:
Sixteen DGB patients, all female, were compared with 29 controls. DGB was performed on average 12.3 years after primary RYGB. In the DGB group, mean BMI was 53.7 before primary RYGB, 31.9 at nadir, and 44.1 prior to DGB. Post-DGB, mean BMI was 40.5, 37.4, 34.8, and 34.4, at 3-, 6-, 12-, and 24-months, respectively. Five patients (31.3%) experienced complications and were readmitted within 30 days, with two of them (12.5%) requiring reintervention and one (6.3%) undergoing reoperation. Mean EWL and TWL up to 2 years after DGB were lower than that after the patient's original RYGB (52.3 ± 18.6 vs. 67.2 ± 33.2; p = 0.126 and 19.6 ± 13.3 vs. 29.6 ± 11.8; p = 0.027, respectively).
Conclusions:
DGB resulted in excellent WL up to 2 years after surgery but was associated with considerable postoperative complication rates. The magnitude of TWL was lower compared with the primary operation. Only a few patients experienced nutritional complications. Results of this study can help counsel patients pursuing DGB for WR or nonresponse to primary RYGB. The comparative effectiveness of this approach to other available options remains to be determined.