Related Experiment Video
Updated: Aug 18, 2026

Full-Endoscopic Interlaminar Approach for Decompression of Lateral Recess Stenosis
Published on: February 24, 2023
Posterior Endoscopic Cervical Decompression in Metastatic Cervical Spine Tumors: An Alternative to Palliative Surgery
Vit Kotheeranurak1, Khanathip Jitpakdee, Yodsawee Pornmeechai
1From the Department of Orthopaedics, Faculty of Medicine, Chulalongkorn University, King Chulalongkorn Memorial Hospital, Bangkok, Thailand (Dr. Kotheeranurak); Center of Excellence in Biomechanics and Innovative Spine Surgery, Chulalongkorn University, Bangkok, Thailand (Dr. Kotheeranurak); the Department of Orthopedics, Queen Savang Vadhana Memorial Hospital, Chonburi, Thailand (Dr. Jitpakdee, Dr. Pornmeechai, and Dr. Khanasuk); Ratchapipat Hospital, Medical Service Department, Bangkok Metropolitan Administration, Bangkok, Thailand (Dr. Laohapornsvan); the Department of Neurosurgery, Seoul St. Mary's Hospital, Spine Center, College of Medicine, The Catholic University of Korea, Seoul, South Korea (Dr. Kim); and the Department of Orthopaedics, School of Medicine, University of Phayao, Phayao, Thailand (Dr. Liawrungrueang).

Abstract:
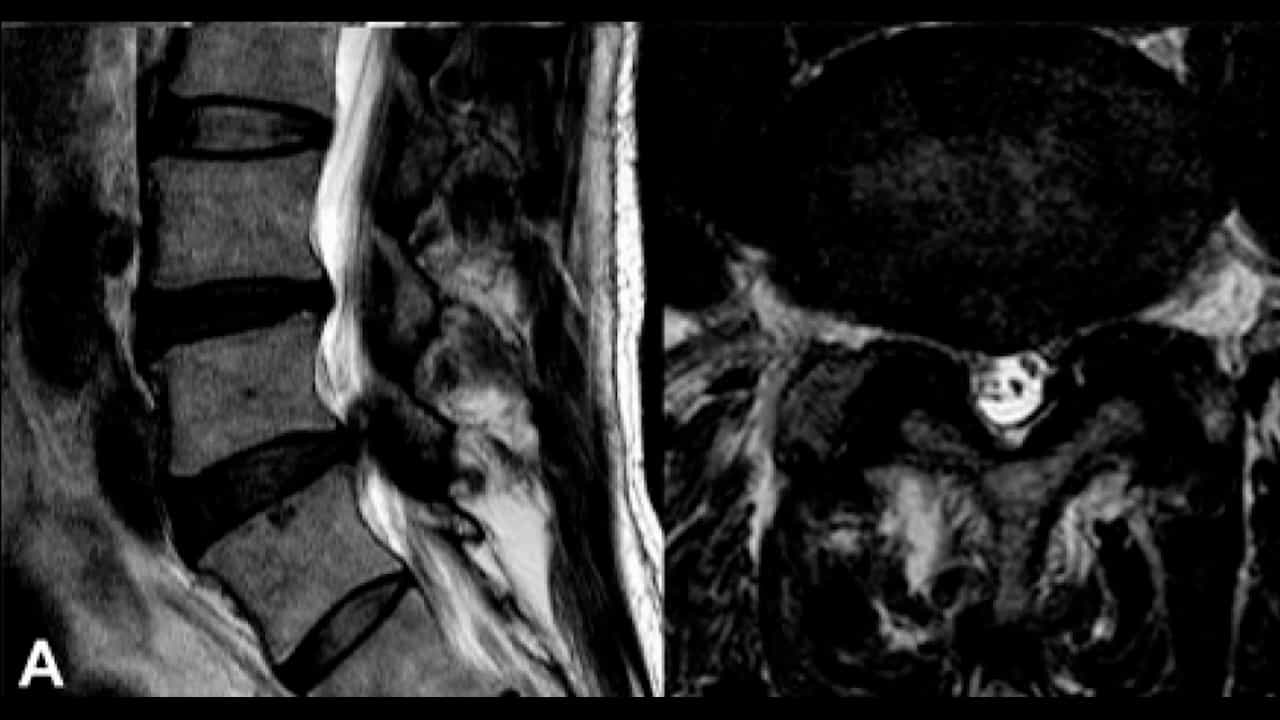
Metastatic spinal cord compression of the cervical spine is a well-known consequence of cancer that generally manifests as an oncological emergency. This study presents and describes an alternative to the minimally invasive posterior full-endoscopic approach for direct decompression and tumor debulking from the metastasis of hepatocellular carcinoma (HCC) in the cervical spine. A 54-year-old man presented with progressive cervical radiculopathy that had persisted for 3 months. The underlying disease was HCC. Radiographic examination revealed evidence of metastatic spinal cord compression with an epidural mass at the C4-C5 levels, which compressed the C4-C5 spinal cord without bony destruction. The modified Tomita score was 6 to 8 points based on palliative surgery. A posterior full-endoscopic approach to remove the tumor from the metastasis of HCC in the cervical spine was done. A postoperative radiographic study revealed adequate tumor mass resection and spinal decompression. The patient was extremely satisfied with this alternative treatment and achieved complete neurologic recovery at 1 month and no recurrent symptoms at the 6-month follow-up. The technique of posterior full-endoscopic decompression of cervical metastasis causing unilateral radiculopathy, presented in this study, is feasible. This surgical intervention seems to be optional minimally invasive and acts as an alternative to palliative surgery.