Related Experiment Video
Updated: Aug 21, 2025


Minimally Invasive Murine Laryngoscopy for Close-Up Imaging of Laryngeal Motion During Breathing and Swallowing
Published on: December 1, 2023
Spectrum of swallowing abnormalities in children with Type I laryngeal cleft
Kershena Liao1, Seckin O Ulualp2
1Department of Otolaryngology -Head and Neck Surgery, University of Texas Southwestern Medical Center, Dallas, TX, USA.

Objectives:
To describe the spectrum of swallowing abnormalities in children with Type I laryngeal cleft (LC-1) and evaluate the effect of LC-1 repair on swallowing abnormalities.
Methods:
A retrospective review was performed of all consecutive children who were diagnosed with LC-1. Swallowing function was evaluated pre- and post-operatively using video fluoroscopic swallow study (VFSS). VFSS reports were used to define swallowing abnormalities and to determine penetration aspiration scale (PAS) and functional oral intake scale (FOIS). Prevalence of swallowing abnormalities, PAS, and FOIS scores were compared before and after repair of LC-1.
Results:
Fifty-seven children with LC-1 had VFSS. The majority of children (86%) had a combination of oral phase, swallow triggering, pharyngeal phase, or esophageal phase impairment. The pharyngeal phase impairment was the most prevalent abnormality (p < 0.001). Esophageal phase impairment was the least prevalent VFSS abnormality (p < 0.001). Prevalence of impaired pharyngeal phase, laryngeal penetration on thin and thick liquids, and silent aspiration was less after repair of LC-1. Fourteen patients (41%) had developmentally appropriate diet with no restrictions after surgery. Nine patients (27%) required positioning and therapy strategies while having developmentally appropriate diet. PAS score after surgery was less than PAS score prior to surgery (p < 0.001). FOIS score after surgery was not different than FOIS score before surgery.
Conclusions:
Multiple phases of swallowing function were impaired in the majority of children with LC-1. Prevalence of swallowing abnormalities varied in the subgroups of gender, gestational age, race, and presence of comorbidity. Swallowing function improved after repair of LC-1.
Related Concept Videos
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids,...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:24
Upper GI Series: Barium Swallow
Purpose and Procedure
Patients undergoing this procedure ingest a liquid containing barium sulfate with a chalky...
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities:
 01:20
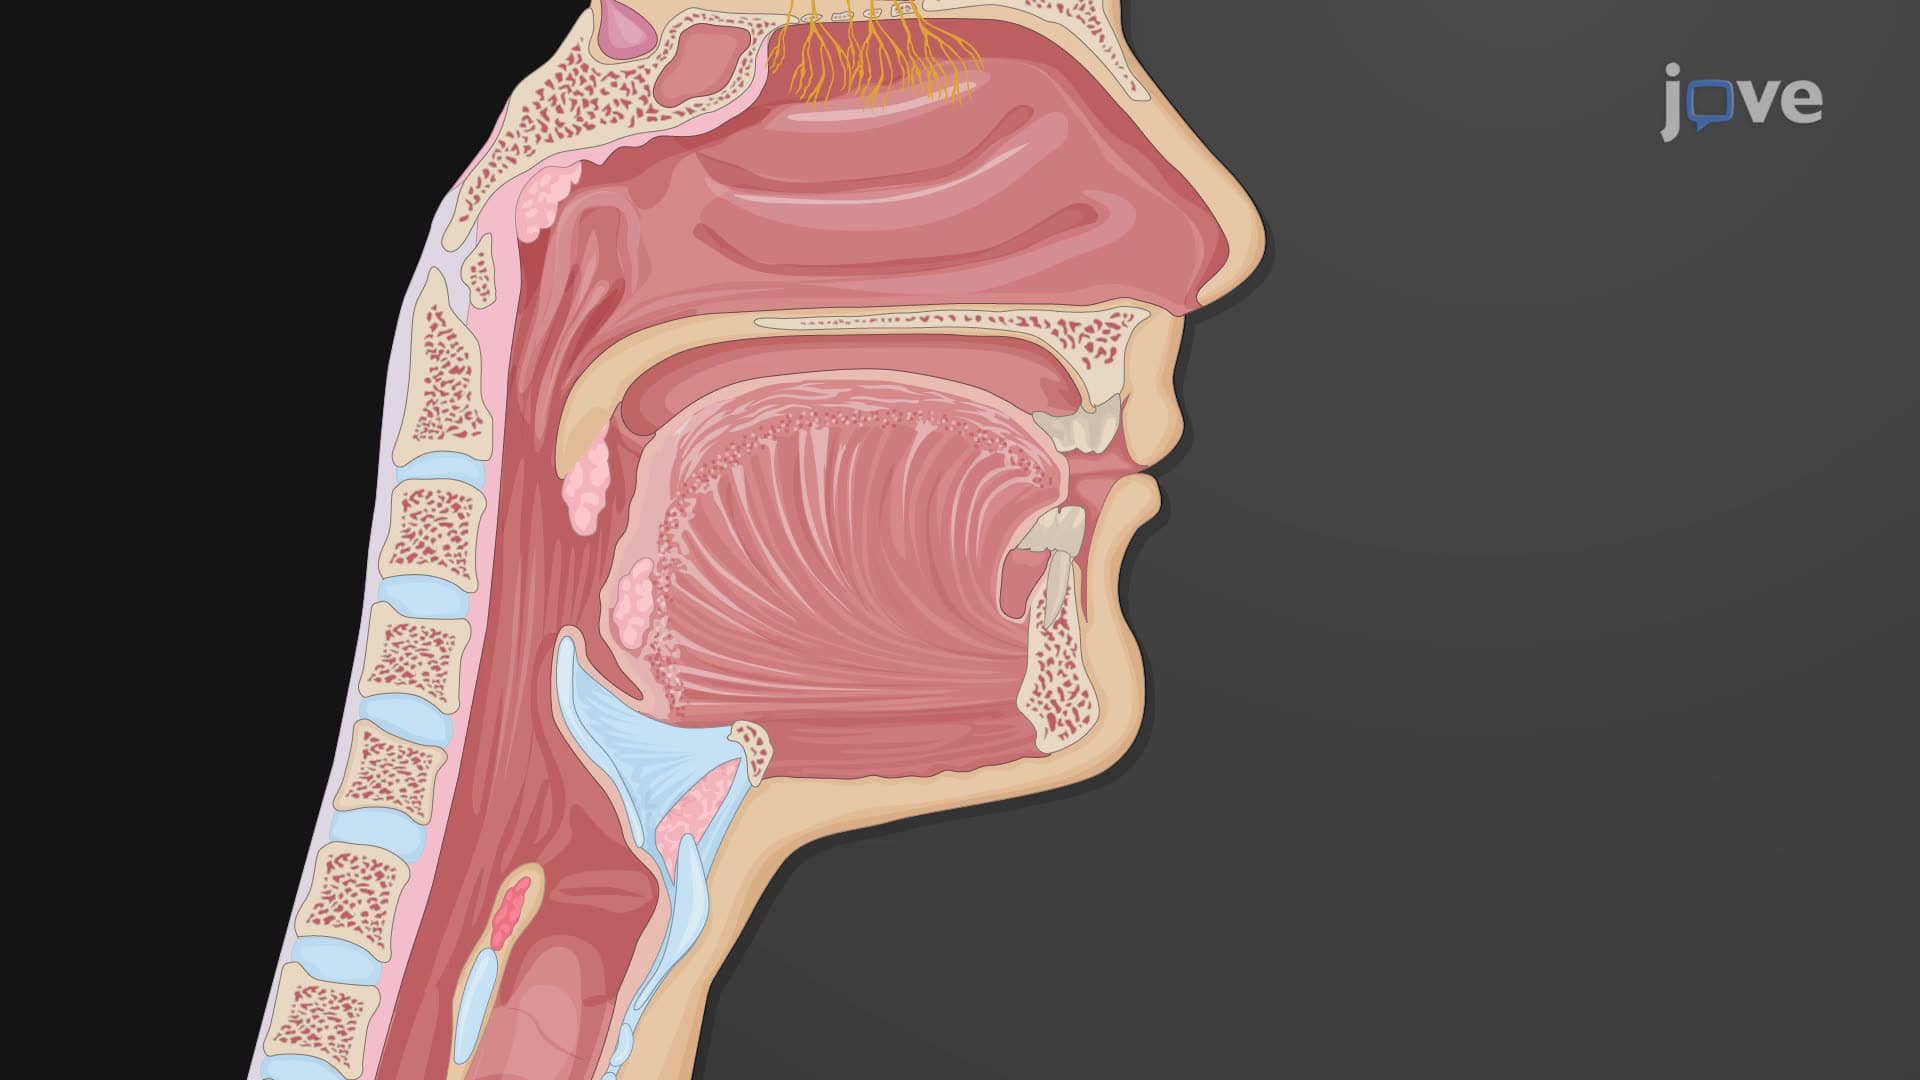
Pharynx
Nasopharynx
The nasopharynx, bordered by the conchae of the nasal cavity, serves exclusively as an air conduit. In its superior region, the pharyngeal tonsils or adenoids are located. These tonsils are clusters of lymphoid reticular tissue akin to a lymph node. The precise...