Related Experiment Video
Updated: Aug 10, 2025
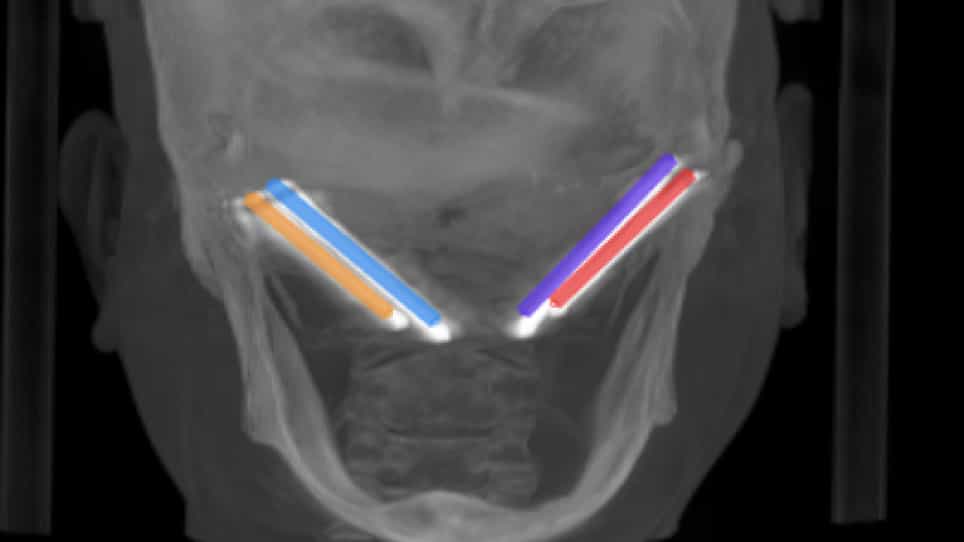

Real-Time Dynamic Navigation System for the Precise Quad-Zygomatic Implant Placement in a Patient with a Severely Atrophic Maxilla
Published on: October 18, 2021
Influence of surgical position and registration methods on clinical accuracy of navigation systems in brain tumor
Motomasa Furuse1, Naokado Ikeda2, Shinji Kawabata2
1Department of Neurosurgery, Osaka Medical and Pharmaceutical University, Takatsuki, Osaka, Japan. motomasa.furuse@ompu.ac.jp.

Abstract:
The aim of this study was to evaluate the influence of skin distortion due to surgical positioning on the clinical accuracy of the navigation system. The distance errors were measured in four fiducial markers (anterior, posterior, right, and left of the head) after the registration of the navigation system. The distance errors were compared between the surface-merge registration (SMR) method using preoperative imaging and the automatic intraoperative registration (AIR) method using intraoperative imaging. The comparison of the distance errors were performed in various surgical positions. The AIR method had the significant accuracy in the lateral markers than the SMR method (lateral position, 3.8 mm vs. 8.95 mm; p < 0.0001; prone position, 4.5 mm vs. 13.9 mm; p = 0.0001; 5.2 mm vs. 11.5 mm; p = 0.0070). The smallest distance errors were obtained close to the surgical field in the AIR method (3.25-3.85 mm) and in the forehead in the SMR method (3.3-8.1 mm). The AIR method was accurate and recommended for all the surgical positions if intraoperative imaging was available. The SMR method was only recommended for the supine position, because skin distortion was frequently observed in the lateral region.