Related Experiment Video
Updated: Aug 9, 2025

11:19
Robotic Myotomy and Partial Fundoplication for Achalasia
Published on: August 11, 2023
1.6K
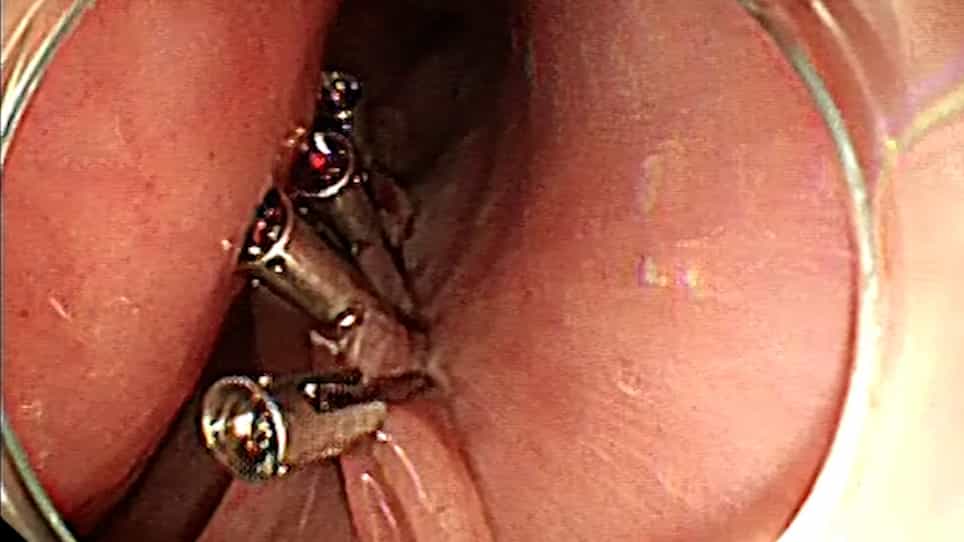
Gastric Peroral Endoscopic Pyloromyotomy for Infants With Congenital Hypertrophic Pyloric Stenosis: Ready for Prime
1Division of Gastroenterology, Hepatology and Nutrition, Children's Hospital of Philadelphia, Philadelphia, Pennsylvania, USA.
The American Journal of Gastroenterology
|February 17, 2023

Abstract
No abstract available in PubMed .

Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
373
Surgical management and nursing care are crucial in treating Peptic Ulcer Disease (PUD). Here is an organized and enhanced overview of the surgical interventions and the associated nursing care for PUD:
Surgical Interventions for Peptic Ulcer Disease
Surgical Interventions for Peptic Ulcer Disease
373
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
239
Enteral nutrition encompasses various methods of delivering nutrition directly to the gastrointestinal (GI) tract, bypassing traditional oral intake. It is particularly beneficial for patients who cannot eat by mouth but have a functioning digestive system. Key methods include nasointestinal feeding, gastrostomy, and jejunostomy, each suited to different clinical scenarios based on the patient's needs and condition.
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
239
 01:26
Esophageal Strictures-II: Clinical Features and Management
135
Patients with esophageal strictures often experience a range of symptoms. Initially, they may have difficulty swallowing solid foods, which can progress to include liquids. Additional symptoms may involve chest pain or discomfort, regurgitating food and fluids, heartburn, unintentional weight loss, coughing or choking during meals, and hoarseness.
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
135
 01:30
Esophageal Strictures-I: Introduction
221
Esophageal strictures involve abnormal narrowing or tightening of the esophagus. They vary in length and severity, ranging from mild constriction to complete obstruction, and are classified as benign (noncancerous) or malignant (cancerous).
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
221
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
171
Peptic ulcer disease (PUD) presents with diverse symptoms depending on the location and severity of the ulcer. Clinical manifestations of peptic ulcer include dull pain and a burning sensation in the mid-epigastric region.
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
171
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
117
Esophageal perforations manifest in various clinical forms, influenced by factors such as the perforation's cause and location (cervical, intrathoracic, or intra-abdominal), the extent of contamination, and potential injury to adjacent mediastinal structures. The timing between the perforation occurrence and treatment initiation also affects the clinical presentation.
Clinical Manifestations:
Clinical Manifestations:
117