Related Experiment Video
Updated: Aug 2, 2025
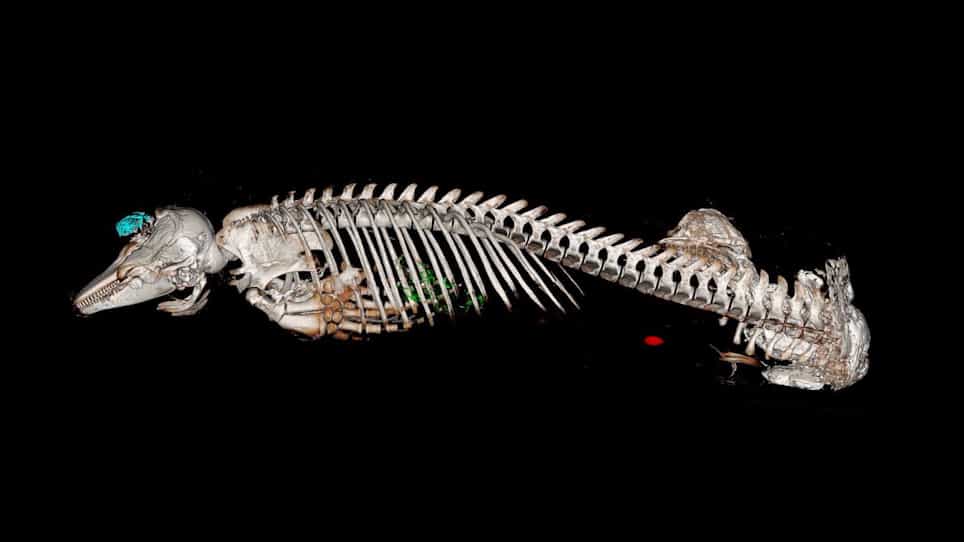

Image Rendering Techniques in Postmortem Computed Tomography: Evaluation of Biological Health and Profile in Stranded Cetaceans
Published on: September 27, 2020
Characterization of fatal blunt injuries using postmortem computed tomography
Jeremy H Levin1, Anthony Pecoraro, Victoria Ochs
1From the Division of Acute Care Surgery, Department of Surgery (J.H.L., A.M., P.M.H.), Department of Surgery (A.P.), Indiana University School of Medicine, Indiana University School of Medicine (V.O.), and Division of Emergency Radiology, Department of Radiology and Imaging Sciences (S.D.S.), Indiana University School of Medicine, Indianapolis, Indiana.

Background:
Rapid triage of blunt agonal trauma patients is necessary to maximize survival, but autopsy is uncommon, slow, and rarely informs resuscitation guidelines. Postmortem computed tomography (PMCT) can serve as an adjunct to autopsy in guiding blunt agonal trauma resuscitation.
Methods:
Retrospective cohort review of trauma decedents who died at or within 1 hour of arrival following blunt trauma and underwent noncontrasted PMCT. Primary outcome was the prevalence of mortal injury defined as potential exsanguination (e.g., cavitary injury, long bone and pelvic fractures), traumatic brain injury, and cervical spine injury. Secondary outcomes were potentially mortal injuries (e.g., pneumothorax) and misplacement airway devices. Patients were grouped by whether arrest occurred prehospital/in-hospital. Univariate analysis was used to identify differences in injury patterns including multiple-trauma injury patterns.
Results:
Over a 9-year period, 80 decedents were included. Average age was 48.9 ± 21.7 years, 68% male, and an average ISS of 42.3 ± 16.3. The most common mechanism was motor vehicle accidents (67.5%) followed by pedestrian struck (15%). Of all decedents, 62 (77.5%) had traumatic arrest prehospital while 18 (22.5%) arrived with pulse. Between groups there were no significant differences in demographics including ISS. The most common mortal injuries were traumatic brain injury (40%), long bone fractures (25%), moderate/large hemoperitoneum (22.5%), and cervical spine injury (25%). Secondary outcomes included moderate/large pneumothorax (18.8%) and esophageal intubation rate of 5%. There were no significant differences in mortal or potentially mortal injuries, and no differences in multiple-trauma injury patterns.
Conclusion:
Fatal blunt injury patterns do not vary between prehospital and in-hospital arrest decedents. High rates of pneumothorax and endotracheal tube misplacement should prompt mandatory chest decompression and confirmation of tube placement in all blunt arrest patients.
Level Of Evidence:
Prognostic and Epidemiological; Level IV.


Related Concept Videos
 01:10
Computed Tomography
The technique was invented in the 1970s and is based on the principle that as X-rays pass through the body, they are absorbed or reflected at different levels. In the technique, a patient lies on a motorized platform while a computerized axial tomography (CAT) scanner rotates...
 01:27
Imaging Studies III: Computed Tomography
 01:28
Imaging Studies for Cardiovascular System V: CT