Related Experiment Video
Updated: Aug 13, 2026
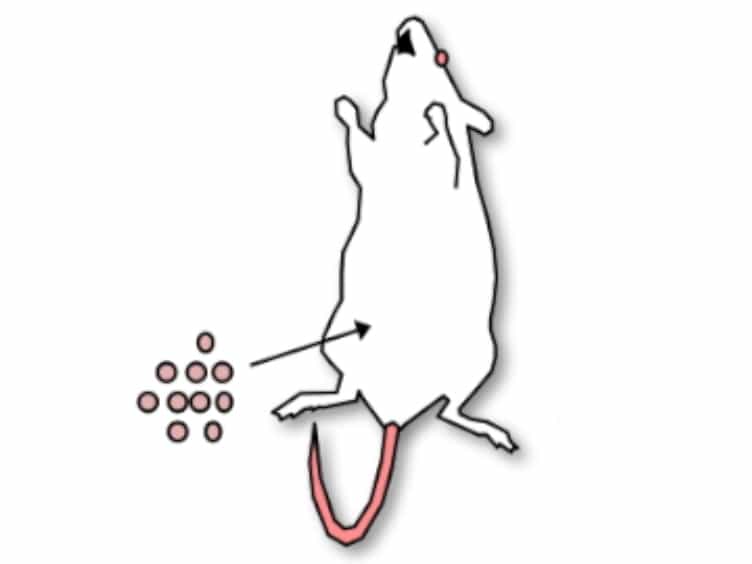

Surgical Procedures and Methodology for a Preclinical Murine Model of De Novo Mammary Cancer Metastasis
Published on: July 29, 2017
Cancer of the breast. Staging methods, primary treatment options and end results

Abstract:
A totally satisfying concept of treatment is not easy to formulate from the complex and often conflicting results of local therapeutic interventions for breast cancer. It seems evident that clinically occult cancer is often beyond the pale of both resection and irradiation at primary treatment, particularly when cancer is found in regional lymph nodes. Despite all combinations of local treatment, the ultimate risk of failure correlates more closely with the stage of the disease at the time of treatment than with the particular form of treatment. Thus the extent of disease must be considered the major, perhaps the ultimate determinant of prognosis. Because, under controlled conditions, several therapeutic alternatives have appeared to provide virtually identical end results in terms of survival and ultimate dissemination of the disease, the adequacy of control within the field of treatment may, in fact, be the most meaningful end result of local treatment. The experience that has accumulated with treatment of breast cancer supports the thesis that removal of the breast accomplishes all that can be achieved in terms of curing the disease, and wider treatment with surgery or irradiation serves only to improve the prospects for local control. Halsted demonstrated this principle with his radical mastectomy and it still seems to be the case. This fact provides further impetus for detecting and treating cancer while it is still localized to the breast. With these generalizations in mind some empirical observations can be added. An anatomic fact is that multiple microscopic foci of cancer that are not evident clinically are often present in the mammary parenchyma. Undisturbed, at least some, and perhaps eventually all, of these foci of cancer progress to become clinical cancers. Thorough removal of the entire breast (the entire mammary parenchyma) eliminates this particular hazard and, one may presume, terminates the disease if it is still limited to the breast. Removal of the underlying pectoralis major muscle provides additional margin around the tissues primarily involved, but sacrific of the muscle is apparently needless unless it is directly invaded by cancer. Microscopic metastases are also often present in regional lymph nodes without being clinically detectable and, left untreated, have the capacity to enlarge and become clinically apparent. Routine wide removal of regional lymph nodes improves the control of cancer at these sites when metastases are present, but whether it improves the chances for cure is doubtful. The fact is that approximately 25 per cent of patients with axillary metastases enjoy prolonged survival free of recurrence, some remaining well even after thirty years (Adair et al., 1974). Whether they would survive as well without removal of the metastases is uncertain. Desease-free survival is highest if metastases are removed while still microscopic, but this phenomenon may simply reflect treatment at an earlier phase in the evolution of the disease...
More Related Videos

Related Concept Videos
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
 01:21
Cancer Survival Analysis