Related Experiment Video
Updated: Jun 21, 2026


Multiplex PCR Assay for Typing of Staphylococcal Cassette Chromosome Mec Types I to V in Methicillin-resistant Staphylococcus aureus
Published on: September 5, 2013
Impact of Multiplex Polymerase Chain Reaction Test in Patients With Meningitis or Encephalitis
Daisuke Kitagawa1,2, Taito Kitano3, Yuto Uchihara4
1Department of Laboratory Medicine, Nara Prefecture General Medical Center, Nara, Japan.

Background:
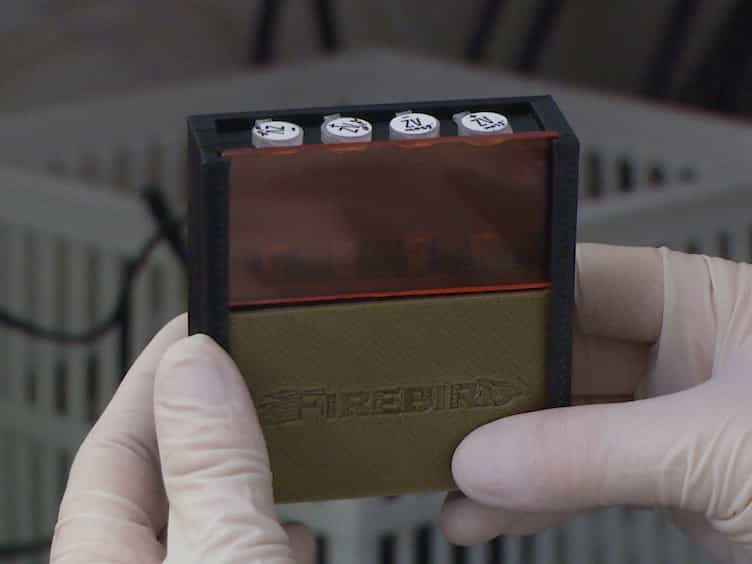
The objective of this study was to evaluate the impact of the FilmArray meningitis/encephalitis panel (FAME) on length of stay (LOS) and duration of antimicrobial treatment in children and adults in a Japanese community hospital.
Methods:
This retrospective cohort study was conducted in Japan between January 2016 and December 2022. We included hospitalized patients with cerebrospinal fluid (CSF) samples and those aged <2 months or who had 5 or more white blood cells/μL in the CSF. To compare the days of therapy (DOT) and LOS between the pre-FAME and FAME periods, multivariate Poisson regression analyses were conducted without an offset term.
Results:
The number of cases undergoing pathogen-specific polymerase chain reaction increased from 3.7% in the pre-FAME period to 57.5% in the FAME period (P < .001). The pathogen identification rate also increased during the FAME period, from 0.4% to 18.7% (P < .001). While the antibacterial DOT was not statistically different between the 2 periods (adjusted rate ratio [aRR], 1.06 [95% confidence interval {CI}, 1.00-1.13]; P = .063]), the antiviral DOT was significantly shorter in the FAME period (aRR, 0.80 [95% CI, .71-.89]; P < .001).
Conclusions:
This study revealed a significant reduction in antiviral use during the FAME period, whereas LOS and antibacterial use did not decrease. Given the possibility of factors (eg, the COVID-19 pandemic) affecting the epidemiology of meningitis and encephalitis, the indications and impact of the FAME test should be evaluated with continuous monitoring of the epidemiology of meningitis and encephalitis and its clinical impact.
Insights
The FilmArray meningitis/encephalitis (FAME) panel significantly reduced antiviral treatment duration in Japanese hospitals. However, length of stay and antibacterial use remained unchanged, necessitating further evaluation of FAME
Area of Science:
- Clinical microbiology
- Infectious diseases
- Hospital epidemiology
Background:
- The FilmArray meningitis/encephalitis (FAME) panel is a multiplex nucleic acid test used for diagnosing central nervous system infections.
- Evaluating the clinical and economic impact of diagnostic panels like FAME is crucial for optimizing patient care and resource allocation in hospitals.
Purpose of the Study:
- To assess the impact of implementing the FAME panel on length of stay (LOS) and duration of antimicrobial treatment in pediatric and adult patients.
- To analyze changes in diagnostic practices and pathogen identification rates following FAME panel adoption.
Main Methods:
- A retrospective cohort study was conducted in a Japanese community hospital from January 2016 to December 2022.
- Patients with cerebrospinal fluid (CSF) samples were included, with specific criteria for infants (<2 months) and those with elevated white blood cell counts (≥5/μL).
- Multivariate Poisson regression analyses were used to compare days of therapy (DOT) and LOS between the pre-FAME and FAME implementation periods.
Main Results:
- Pathogen-specific polymerase chain reaction (PCR) use increased significantly from 3.7% to 57.5% (P < .001) after FAME implementation.
- The overall pathogen identification rate rose from 0.4% to 18.7% (P < .001).
- While antibacterial DOT showed no significant difference (aRR, 1.06; P = .063), antiviral DOT was significantly reduced in the FAME period (aRR, 0.80; P < .001).
Conclusions:
- The FAME panel led to a significant decrease in antiviral treatment duration but did not impact LOS or antibacterial use.
- External factors, such as the COVID-19 pandemic, may have influenced meningitis and encephalitis epidemiology, confounding the observed results.
- Continuous monitoring of FAME's clinical impact and the epidemiology of meningitis/encephalitis is recommended to refine its appropriate use.

Related Concept Videos
 01:24
Bacterial Meningitis
 01:18
Viral Meningitis
 01:22
Bacterial Meningitis I: Introduction
 01:26
Bacterial Meningitis II: Pathophysiology
 01:19
Encephalitis l: Introduction
 01:26
Encephalitis ll: Pathophysiology