Related Experiment Video
Updated: Jul 3, 2025
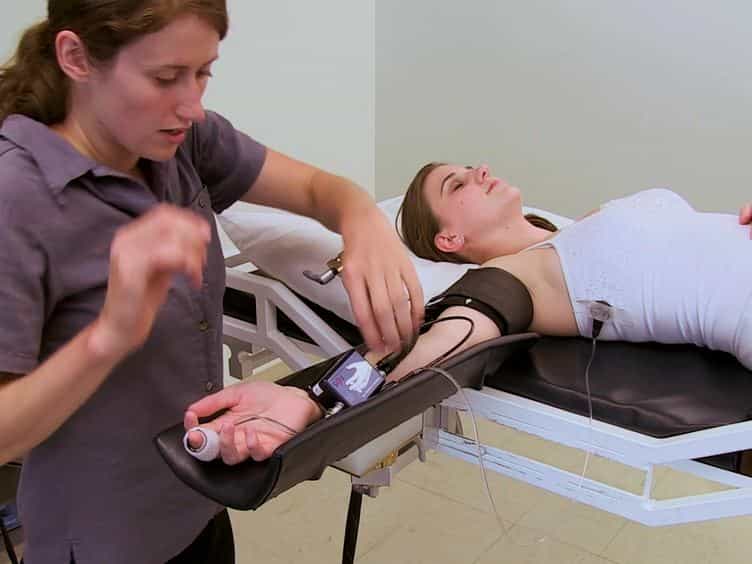

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Diagnosis and treatment of recurrent syncope in a middle-aged women

A 50-year-old female patient, presented with repeated syncope for more than 2 years. Prior assessments were conducted at different hospitals, but no definite abnormalities were found. The patient's fear and anxiety about possible future attacks were escalating. Through a Head-up tilt test, the cause was finally identified as vasovagal syncope. Following a 5-min administration of nitroglycerin, the patient reported palpitations, nausea, and deep, rapid breathing. The electrocardiogram initially showed a first-degree atrioventricular block, progressing swiftly to a second-degree type I atrioventricular block-high atrioventricular block. Immediate intervention was undertaken, but blood pressure was not instantly ascertainable, coinciding with an abrupt loss of consciousness. Subsequent electrocardiographic findings included paroxysmal third-degree atrioventricular block, sinus arrest, and complete cardiac arrest, prompting the initiation of external cardiac compressions. The longest recorded ventricular arrest approximated 15 s, with sinus rhythm resuming post 10 s of cardiac compressions and the patient regaining consciousness. The patient underwent vagal ablation and no longer experienced syncope.
A 50-year-old female patient, presented with repeated syncope for more than 2 years. Prior assessments were conducted at different hospitals, but no definite abnormalities were found. The patient's fear and anxiety about possible future attacks were escalating. Through a Head-up tilt test, the cause was finally identified as vasovagal syncope. Following a 5-min administration of nitroglycerin, the patient reported palpitations, nausea, and deep, rapid breathing. The electrocardiogram initially showed a first-degree atrioventricular block, progressing swiftly to a second-degree type I atrioventricular block-high atrioventricular block. Immediate intervention was undertaken, but blood pressure was not instantly ascertainable, coinciding with an abrupt loss of consciousness. Subsequent electrocardiographic findings included paroxysmal third-degree atrioventricular block, sinus arrest, and complete cardiac arrest, prompting the initiation of external cardiac compressions. The longest recorded ventricular arrest approximated 15 s, with sinus rhythm resuming post 10 s of cardiac compressions and the patient regaining consciousness. The patient underwent vagal ablation and no longer experienced syncope.


Related Concept Videos
 01:14
Decreased pulse rate
There are specific risk factors that can elevate the likelihood of developing bradycardia. Advanced age is a significant factor, with...
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion,...
 01:17
Increased pulse rate
Many factors can elevate the risk of developing tachycardia. These include advanced age, a family history of arrhythmias, and an...
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac...
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...