Related Experiment Video
Updated: Jun 29, 2025


Electrophysiological Assessment of Murine Atria with High-Resolution Optical Mapping
Published on: February 22, 2018
Focal atrial tachycardias originating from the aorta-mitral continuity: Anatomical and electrophysiological
Jian-du Yang1, Yuan Gao1, Xiao-Gang Guo1
1State Key Laboratory of Cardiovascular Disease, Arrhythmia Center, Fuwai Hospital, National Center for Cardiovascular Diseases, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing, China.

Background:
The aorta-mitral annulus conjunction (AMC) is an uncommon site of origin of focal atrial tachycardias (ATs). Hence, the electrophysiological and ablation target characteristics are poorly described.
Objective:
The purpose of this study was to describe the characteristics of AMC ATs in detail.
Methods:
The study enrolled 650 patients with ATs, 21 (3.2%) of whom had ATs originating from the AMC. A comprehensive evaluation, including electrocardiography, electrophysiology study, computed tomography scan, and intracardiac echocardiography, was performed.
Results:
The majority (19, 90.5%) of ATs occurred spontaneously. The mean age of this group was 48.9 ± 21.6 years, with 12 being female (57.1%). Seventeen patients had a typical biphasic P wave with a prominent positive component. The earliest activation site in the right atrium was near the His bundle, with average activation -10.3 ± 6.0 ms preceding the P wave. The successful ablation targets were distributed as follows: 1 case at 9 o'clock, 6 cases at 10 o'clock, 7 cases at 11 o'clock, 6 cases at 12 o'clock, and 1 case in the left coronary cusp. The local AMC potential differed from the commonly perceived annular potential and was characterized by a prominent A wave and a smaller V wave (atrial-to-ventricular ratio > 1). The angle of encroachment on the left atrial anterior wall, compressed by the left coronary cusp, was significantly smaller in the AMC ATs group than in the control group consisted of 40 patients who underwent coronary artery CT scans because of the chest pain but without atrial arrhythmias were randomly selected, which may have contributed to the arrhythmia substrate (141.7° ± 11.5° vs 155.2° ± 13.9°; P = .026).
Conclusion:
A new strategy for mapping AMC ATs has been introduced. The ablation target should have an atrial-to-ventricular ratio of >1.


Related Concept Videos
 01:28
Mechanism of Cardiac Arrhythmias
 01:19
Conduction System of the Heart
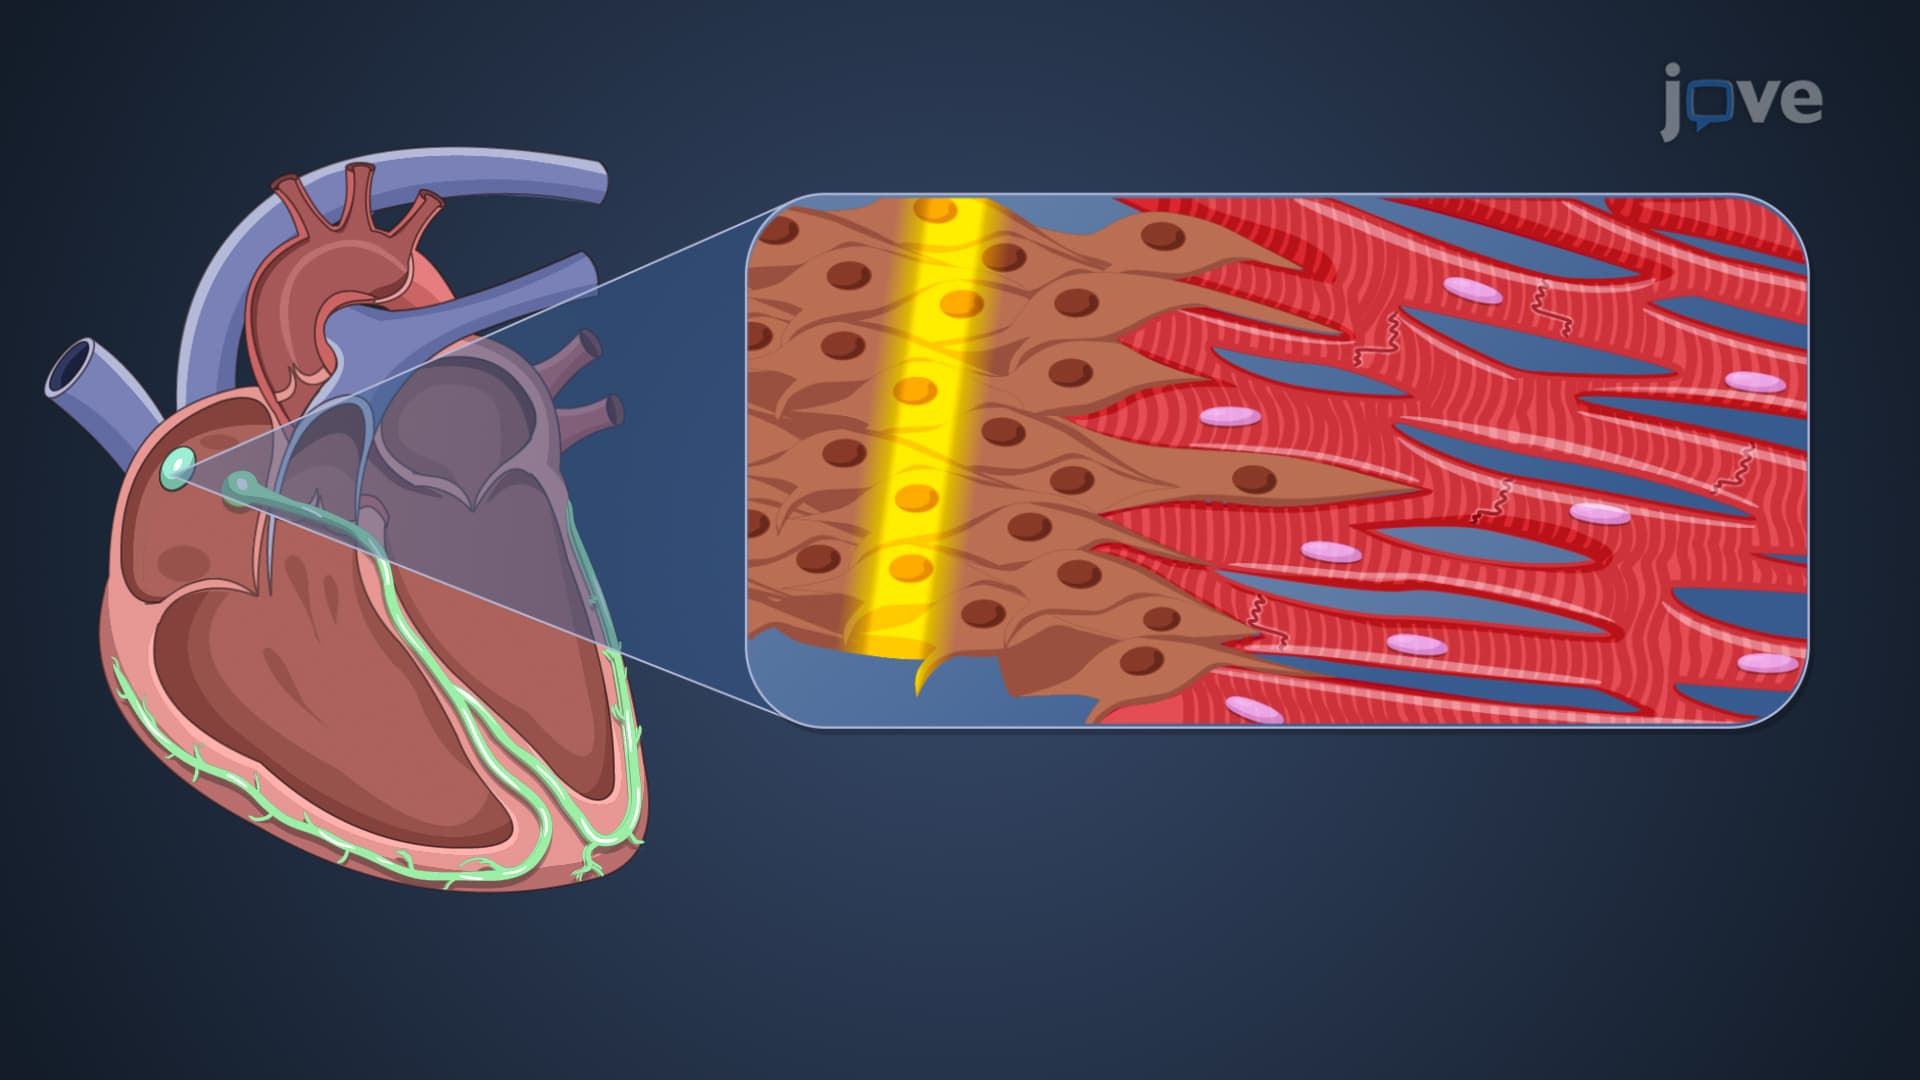
The pacemaker cells are located in two primary nodes: the sinoatrial (SA) node and the atrioventricular (AV) node. The SA node pacemaker cells can autonomously depolarize, triggering an action potential that leads to the...
 01:28
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow...
 01:19
Electrophysiology of Normal Cardiac Rhythm
 01:16
ECG Interpretation of Arrhythmias I: Sinus Arrhythmias
Types of Arrhythmias
Sinus Node Arrhythmias
Sinus Bradycardia: Originating from the sinoatrial (SA) node, sinus bradycardia involves slower impulses, resulting in a heart rate of less than 60 beats per minute (bpm). Causes include sleep, vagal stimulation, beta-blockers, hypothyroidism,...
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and...