Related Experiment Video
Updated: Jun 28, 2025

The Role of Indocyanine Green Fluorescence in Complex Laparoscopic Cholecystectomy Navigation
Published on: January 31, 2025
The difficult cholecystectomy: What you need to know
Anupamaa Seshadri1, Andrew B Peitzman
1From the Beth Israel Deaconess Medical Center (A.S.), Boston, Massachusetts; and Department of Surgery, University of Pittsburgh School of Medicine (A.B.P.), Pittsburgh, Pennsylvania.

Abstract:
This review discusses the grading of cholecystitis, the optimal timing of cholecystectomy, adopting a culture of safe cholecystectomy, understanding the common error traps that can lead to intraoperative complications, and how to avoid them. 1-28 The Tokyo Guidelines, American Association for the Surgery of Trauma, Nassar, and Parkland scoring systems are discussed. The patient factors, physiologic status, and operative findings that predict a difficult cholecystectomy or conversion from laparoscopic to open cholecystectomy are reviewed. With laparoscopic expertise and patient conditions that are not prohibitive, early laparoscopic cholecystectomy is recommended. This is ideally within 72 hours of admission but supported up to the seventh hospital day. The majority of bile duct injuries are due to misidentification of normal anatomy. Strasberg's four error traps and the zones of danger to avoid during a cholecystectomy are described. The review emphasizes the importance of a true critical view of safety for identification of the anatomy. In up to 15% of operations for acute cholecystitis, a critical view of safety cannot be achieved safely. Recognizing these conditions and changing your operative strategy are mandatory to avoid harm. The principles to follow for a safe cholecystectomy are discussed in detail. The cardinal message of this review is, "under challenging conditions, bile duct injuries can be minimized via either a subtotal cholecystectomy or top-down cholecystectomy if dissection in the hepatocystic triangle is avoided". 21 The most severe biliary/vascular injuries usually occur after conversion from laparoscopic cholecystectomy. Indications and techniques for bailout procedures including the fenestrating and reconstituting subtotal cholecystectomy are presented. Seven percent to 10% of cholecystectomies for acute cholecystitis currently result in subtotal cholecystectomy. Level of evidence: III.
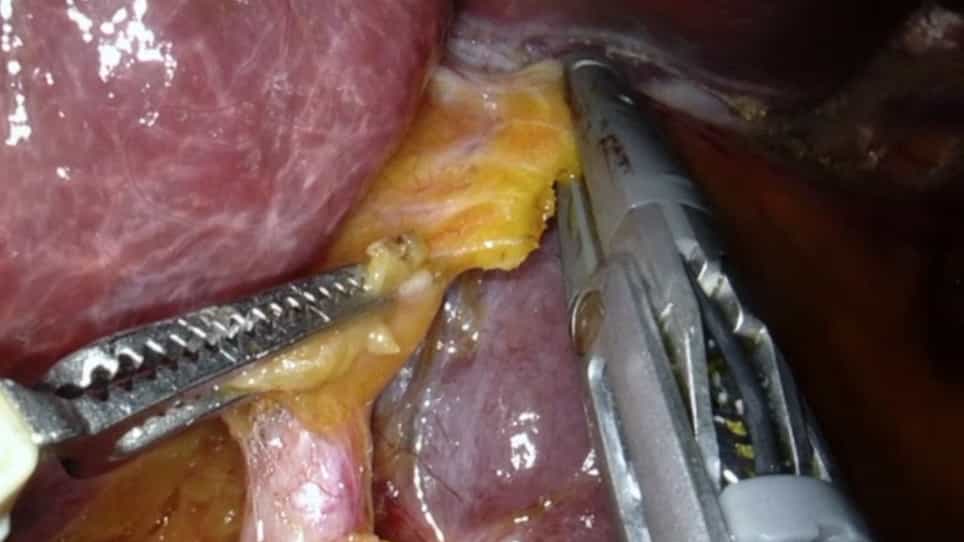
Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment: