Related Experiment Video
Updated: Jun 27, 2025


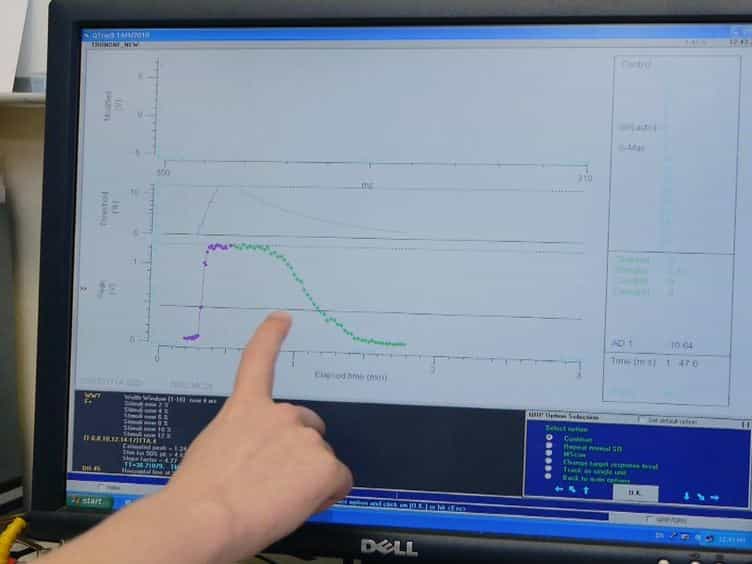
Nerve Stimulator-guided Injection of Autologous Stem Cells Near the Equine Left Recurrent Laryngeal Nerve
Published on: September 26, 2018
Diabetic Neuropathy and Minimum Effective Anesthetic Concentration of Mepivacaine for Axillary Brachial Plexus Block:
Na-Eun Kim1, Woo-Joo Lee2, Jong-Kwon Jung1
1The Department of Anesthesiology and Pain Medicine, School of Medicine, Inha University, 100 Inha-ro, Michuhol-gu, Incheon 22212, Republic of Korea.

Nerves in patients with diabetic neuropathy (DN) show increased susceptibility to local anesthetics, potentially requiring a decreased dose. We investigated whether the minimum effective anesthetic concentration (MEAC) of mepivacaine for successful axillary block is lower in patients with DN than in those without. This prospective observational study included patients with DN (n = 22) and without diabetes (n = 22) at a tertiary care center. Patients received an ultrasound-guided axillary block with 30 mL of mepivacaine for anesthesia. The mepivacaine concentration used in each patient was calculated using Dixon's up-and-down method. A block was considered successful if all four sensory nerves had a score of 1 or 2 within 30 min with no pain during surgery. The primary outcome was the MEAC of mepivacaine, and the secondary outcomes included the minimal nerve stimulation intensity for the musculocutaneous nerve and the occurrence of adverse events. The MEAC50 was 0.55% (95% CI 0.33-0.77%) in patients without diabetes and 0.58% (95% CI 0.39-0.77%) in patients with DN (p = 0.837). The MEAC90 was 0.98% (95% CI 0.54-1.42%) in patients without diabetes and 0.96% (95% CI 0.57-1.35%) in patients with DN (p = 0.949). The stimulation threshold for the musculocutaneous nerve was significantly different between groups (0.49 mA vs. 0.19 mA for patients with vs. without diabetes; p = 0.002). In conclusion, the MEAC of mepivacaine for a successful axillary block is not lower in patients with DN.
Nerves in patients with diabetic neuropathy (DN) show increased susceptibility to local anesthetics, potentially requiring a decreased dose. We investigated whether the minimum effective anesthetic concentration (MEAC) of mepivacaine for successful axillary block is lower in patients with DN than in those without. This prospective observational study included patients with DN (n = 22) and without diabetes (n = 22) at a tertiary care center. Patients received an ultrasound-guided axillary block with 30 mL of mepivacaine for anesthesia. The mepivacaine concentration used in each patient was calculated using Dixon's up-and-down method. A block was considered successful if all four sensory nerves had a score of 1 or 2 within 30 min with no pain during surgery. The primary outcome was the MEAC of mepivacaine, and the secondary outcomes included the minimal nerve stimulation intensity for the musculocutaneous nerve and the occurrence of adverse events. The MEAC50 was 0.55% (95% CI 0.33-0.77%) in patients without diabetes and 0.58% (95% CI 0.39-0.77%) in patients with DN (p = 0.837). The MEAC90 was 0.98% (95% CI 0.54-1.42%) in patients without diabetes and 0.96% (95% CI 0.57-1.35%) in patients with DN (p = 0.949). The stimulation threshold for the musculocutaneous nerve was significantly different between groups (0.49 mA vs. 0.19 mA for patients with vs. without diabetes; p = 0.002). In conclusion, the MEAC of mepivacaine for a successful axillary block is not lower in patients with DN.

Related Concept Videos
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:24
Local Anesthetics: Differential Sensitivity of Nerve Fibers
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:30
Local Anesthetics: Clinical Application as Surface, Infiltration, and Conduction Block Anesthesia