Related Experiment Video
Updated: Jun 23, 2025

Receptor Autoradiography Protocol for the Localized Visualization of Angiotensin II Receptors
Published on: June 7, 2016
Adrenoceptors and Hypertension
Spoorthy Kulkarni1, Ian B Wilkinson2
1Department of Experimental Medicine and Immunotherapeutics, Vascular Research Clinic, ACCI Level 3, Addenbrooke's Hospital, University of Cambridge, Cambridge, UK.

Insights
Hypertension, a common condition, involves blood vessel changes and end-organ damage. Early stages show hemodynamic shifts and kidney issues, with adrenoceptor stimulation and the renin-angiotensin-aldosterone system playing key roles.
Area of Science:
- Cardiovascular Medicine
- Nephrology
- Pharmacology
Background:
- Hypertension is a prevalent condition causing significant mortality and morbidity due to vascular and end-organ damage.
- Early hypertension stages, particularly in young men, involve hemodynamic alterations like increased cardiac output and peripheral resistance.
- Kidney damage from increased sodium reabsorption is a proposed initial trigger for essential hypertension.
Purpose of the Study:
- To review the pathophysiological mechanisms of hypertension, focusing on adrenoceptor stimulation and the renin-angiotensin-aldosterone system.
- To discuss the historical and current therapeutic roles of adrenoceptor antagonists and other antihypertensive agents.
- To highlight hypertension management in specific complex medical conditions.
Main Methods:
- Review of pathophysiological mechanisms including catecholamine effects on adrenoceptors and the renin-angiotensin-aldosterone system.
- Analysis of the therapeutic evolution of antihypertensive drugs, from early adrenoceptor blockers to current first-line agents.
- Examination of hypertension in specific conditions like pregnancy, phaeochromocytoma, and pulmonary arterial hypertension.
Main Results:
- Adrenoceptor stimulation (α1, β1) and renin-angiotensin-aldosterone system activation contribute to endothelial dysfunction and persistent hypertension.
- While initially used, α1 blockers, α2 agonists, and β blockers are no longer first-line due to outcome trial results.
- Angiotensin-converting enzyme inhibitors, angiotensin receptor blockers, calcium channel blockers, and thiazide-like diuretics are now considered first-line therapies.
Conclusions:
- Adrenoceptor agents remain relevant as second- or third-line therapy for hypertension.
- Understanding adrenoceptor roles is crucial for managing hypertension in various clinical contexts.
- This overview provides insights for clinicians and researchers on adrenoceptors in hypertension pathophysiology and treatment.
Abstract:
Hypertension is a very prevalent condition associated with high mortality and morbidity, secondary to changes resulting in blood vessels and resultant end-organ damage. Haemodynamic changes, including an initial rise in cardiac output followed by an increase in total peripheral resistance, denote the early changes associated with borderline or stage 1 hypertension, especially in young men. Increased sodium reabsorption leading to kidney damage is another mechanism proposed as one of the initial triggers for essential hypertension. The underlying pathophysiological mechanisms include catecholamine-induced α1- and ß1-adrenoceptor stimulation, and renin-angiotensin-aldosterone system activation leading to endothelial dysfunction which is believed to lead to persistent blood pressure elevation.α1 blockers, α2 agonists, and ß blockers were among the first oral anti-hypertensives. They are no longer first-line therapy after outcome trials did not demonstrate any benefits over and above other agents, despite similar blood pressure reductions. Angiotensin-converting enzyme inhibitors (or angiotensin receptor blockers), calcium channel blockers, and thiazide-like diuretics are now considered the first line of therapy, although adrenoceptor agents still have a role as second- or third-line therapy. The chapter also highlights hypertension in specific medical conditions such as pregnancy, phaeochromocytoma, hyperthyroidism, portal hypertension, pulmonary arterial hypertension, and ocular hypertension, to provide an overview for clinicians and researchers interested in the role of adrenoceptors in the pathophysiology and management of hypertension.

Related Concept Videos
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors,...
 01:17
Hormonal Regulation of Blood Pressure
Epinephrine and Norepinephrine
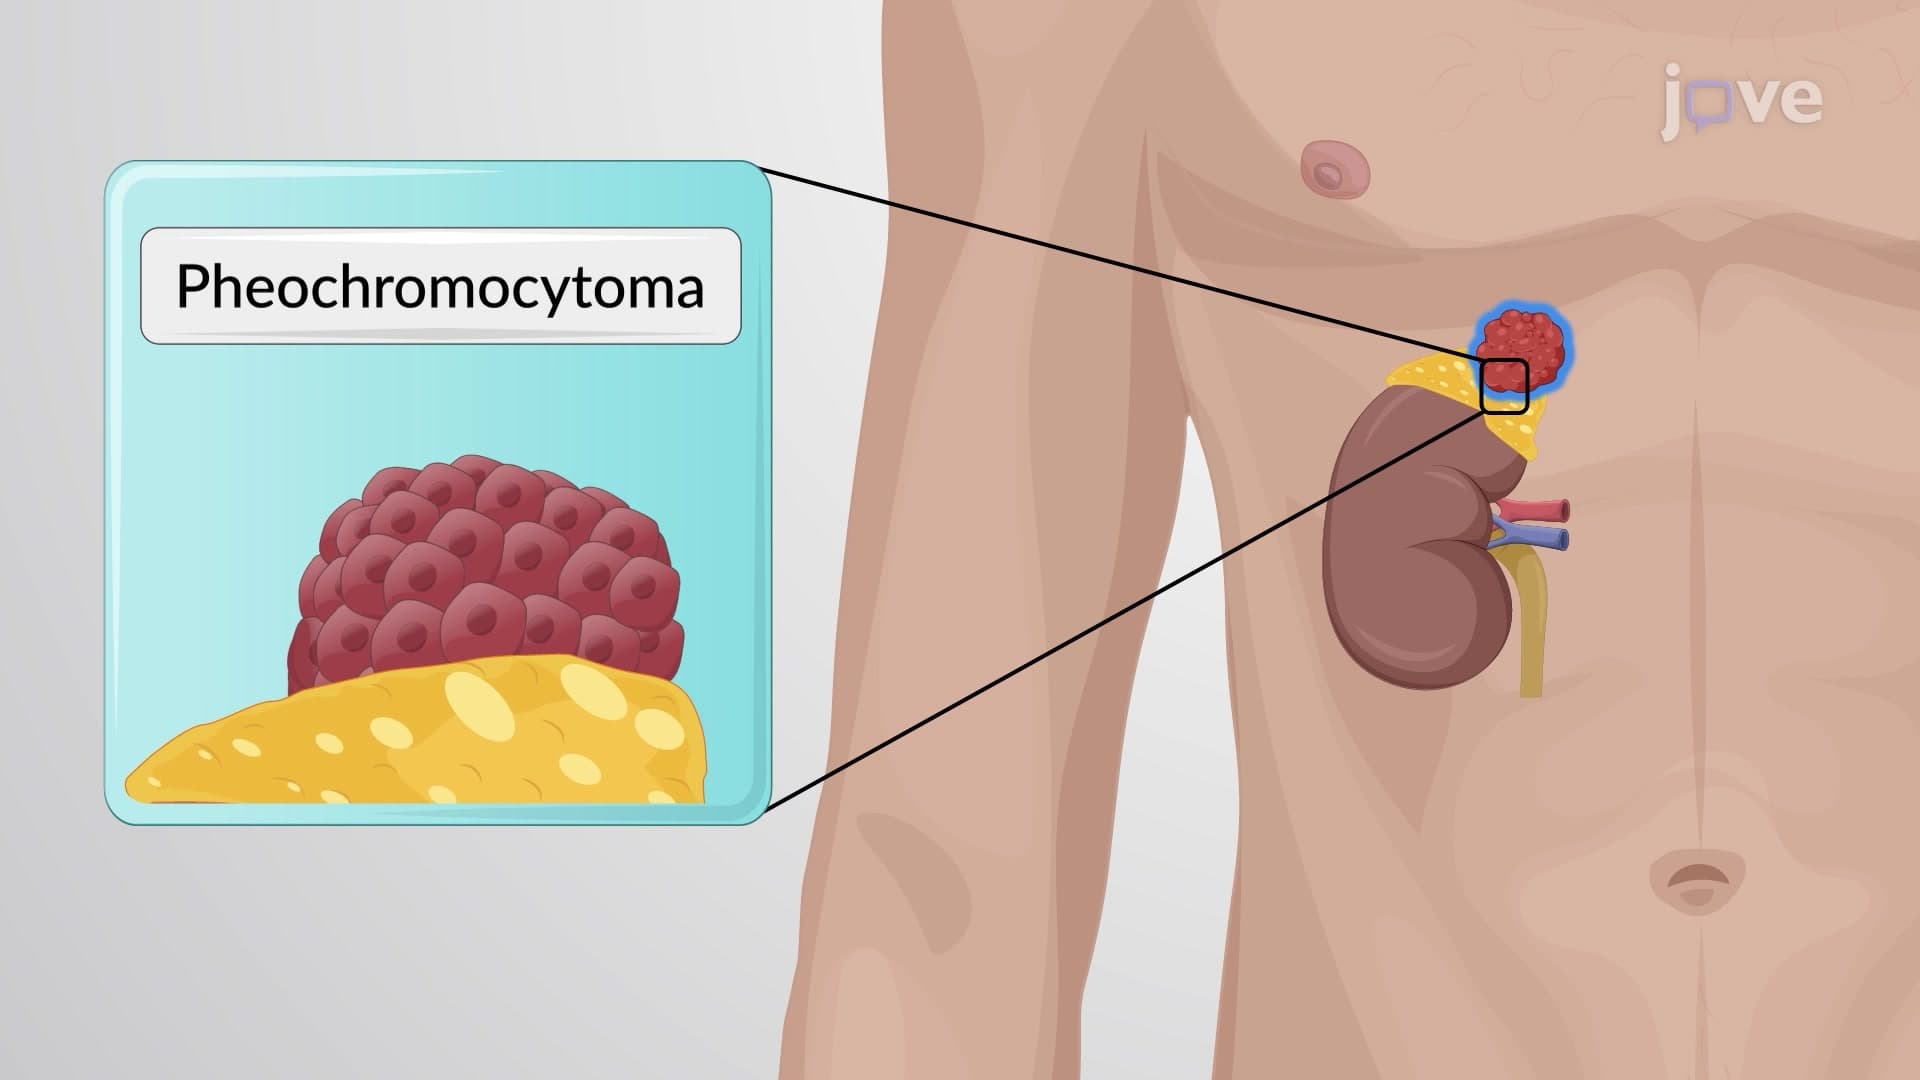
The adrenal medulla releases epinephrine and norepinephrine, catecholamines that enhance and extend the sympathetic or "fight or flight" physiological response. These hormones escalate heart rate and the force of contraction...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
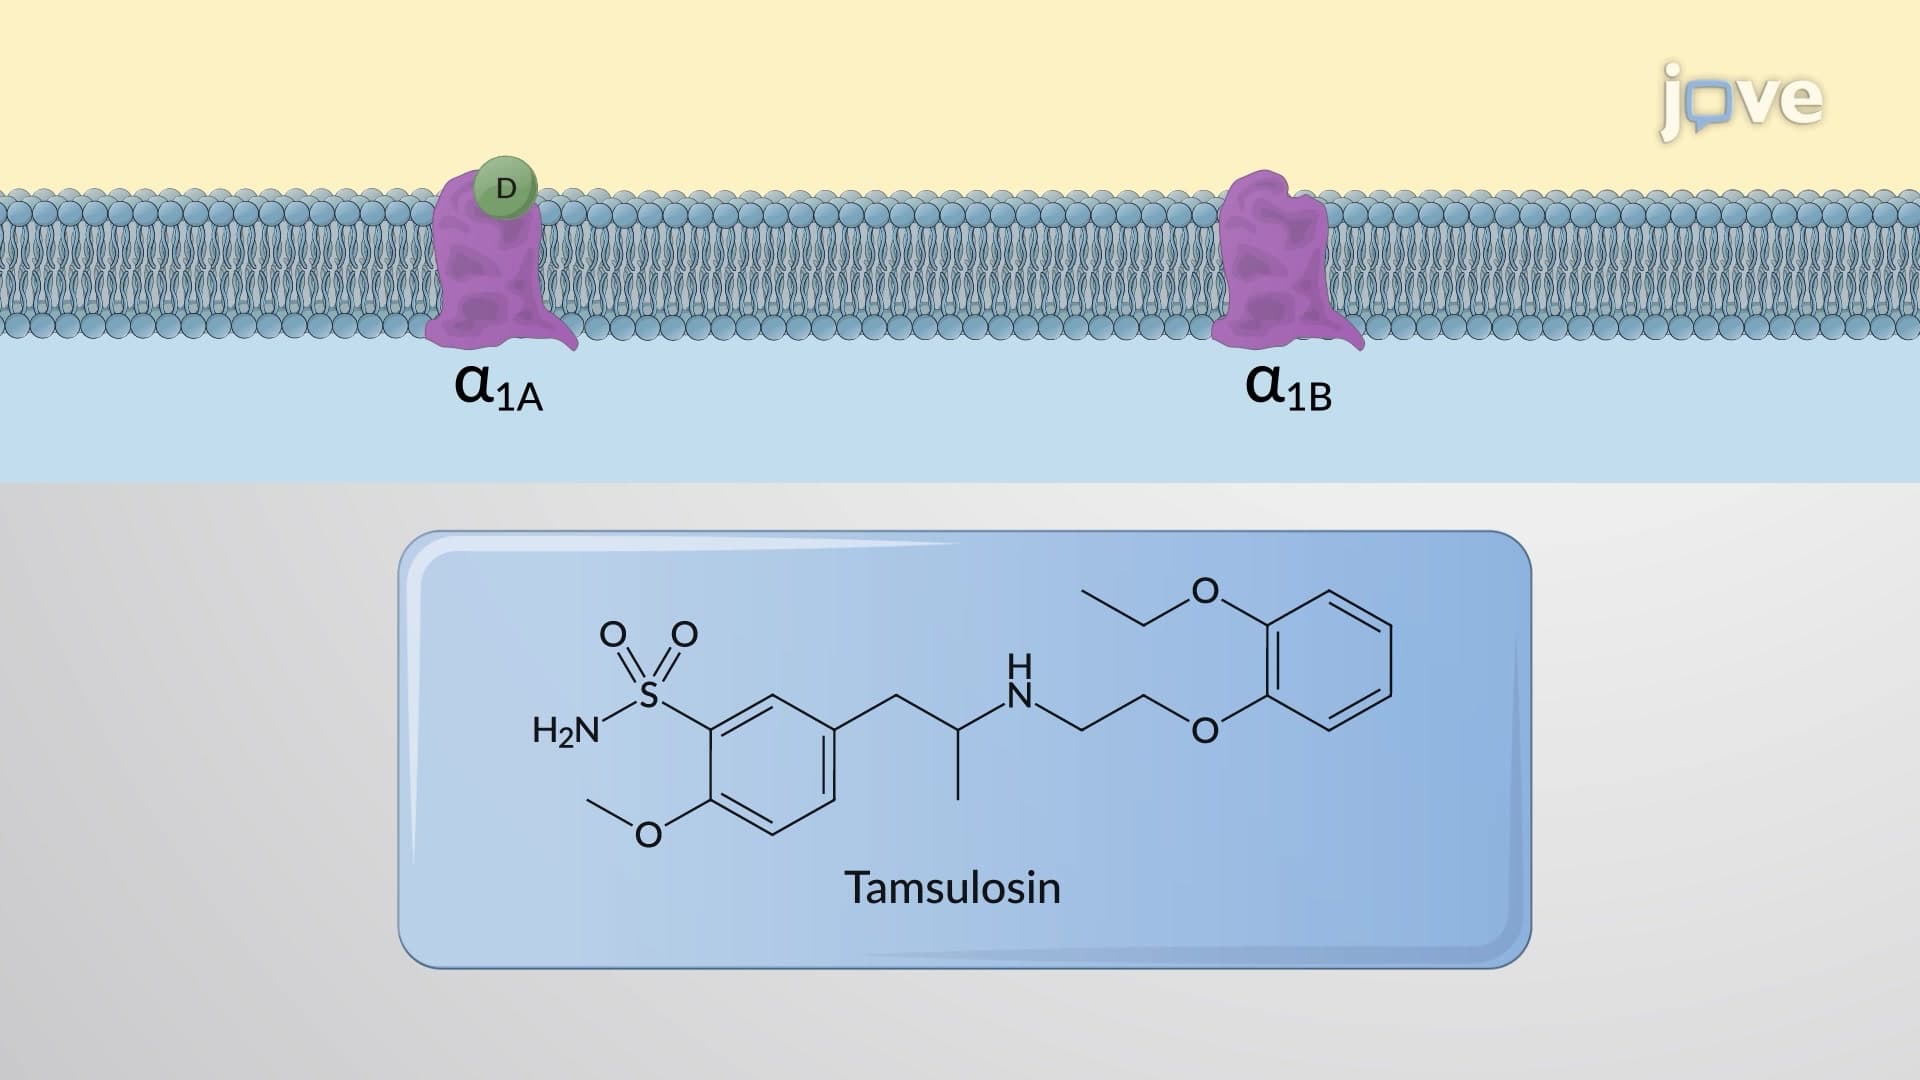
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:26
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
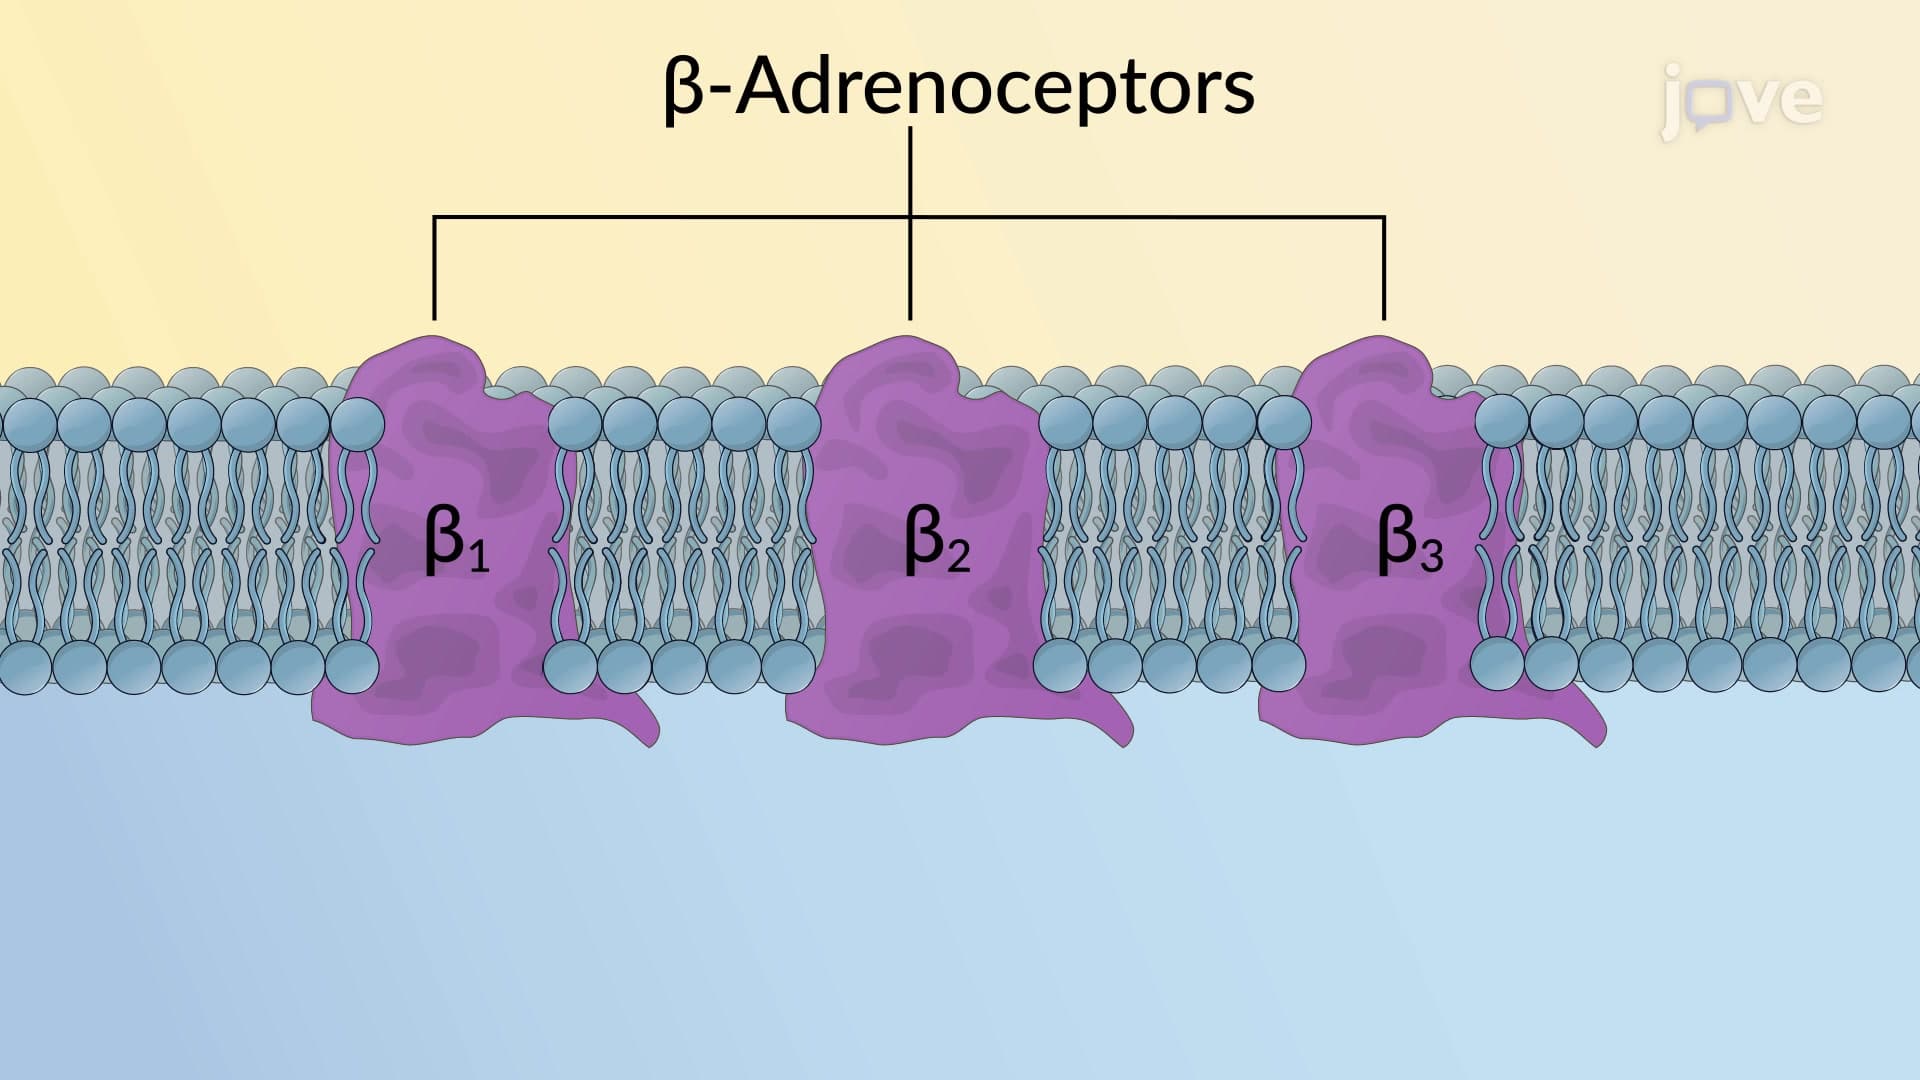
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...