Related Experiment Video
Updated: Jun 14, 2025
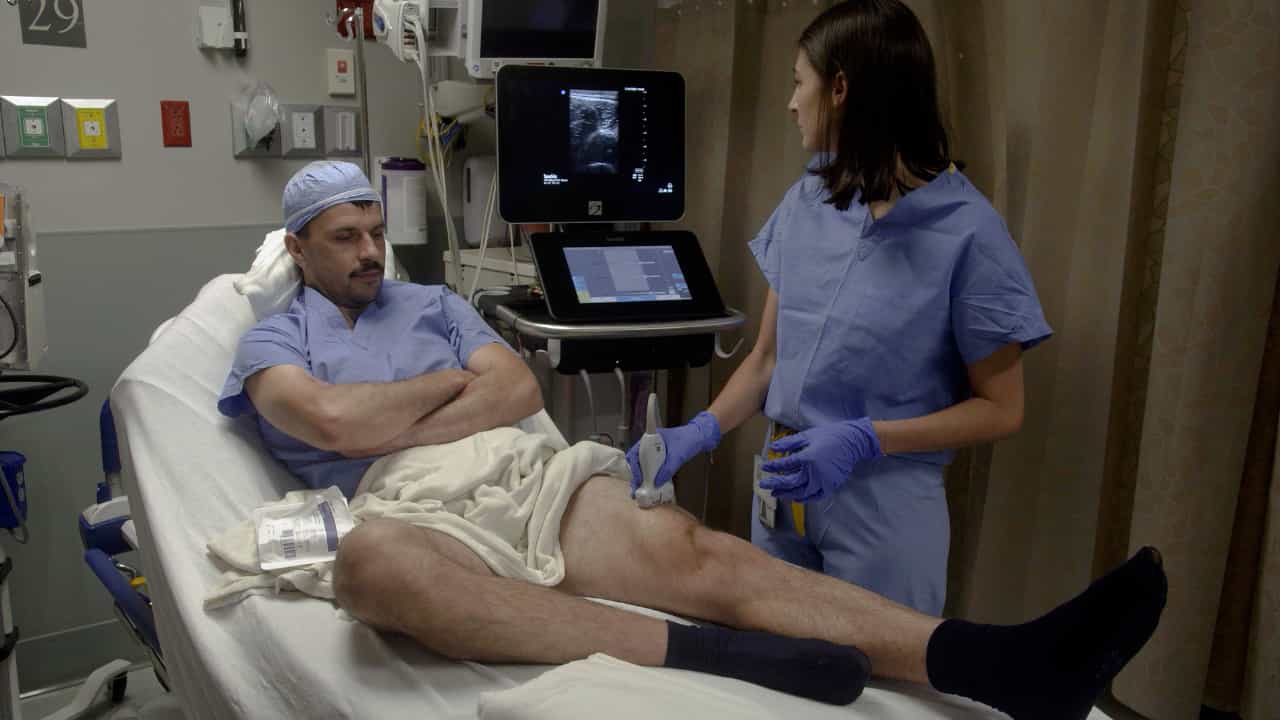

Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Comparison of a risk calculator with frailty indices in patients undergoing lung cancer resection
Dominic J Vitello1,2, Charles D Logan1,2,3, Norah N Zaza1,2
1Northwestern Quality Improvement, Research, & Education in Surgery, Department of Surgery, Feinberg School of Medicine, Northwestern University, Chicago, Illinois, USA.

Introduction:
Perioperative risk stratification is an essential component of preoperative planning for cancer surgery. While frailty has gained attention for its utility in risk stratification, no studies have directly compared it to existing risk calculators. Therefore, the objective of this study was to compare the risk stratification of the American College of Surgeons Surgical Risk Calculator (ACS-SRC), the Revised Risk Analysis Index (RAI-rev), and the Modified Frailty Index (5-mFI). The primary outcomes were 30-day postoperative morbidity, 30-day postoperative mortality, unplanned readmission, unplanned reoperation, and discharge disposition other-than-home.
Methods:
Patients undergoing anatomic lung resection for primary, non-small cell lung cancer were identified within the American College of Surgeons National Quality Improvement Program (ACS NSQIP) database. The ACS-SRC, RAI-rev, and 5-mFI tools were used to predict adverse postoperative events. Tools were compared for discrimination in the primary outcomes.
Results:
9663 patients undergoing anatomic lung resection for cancer between 2012 and 2014 were included. The cohort was 53.1% female. Median age at diagnosis was 67 (interquartile range = 59-74) years. Cardiothoracic surgeons performed 89% and general surgeons performed 11.0% of the operations. Perioperative morbidity and mortality rates were 10.9% (n = 1048) and 1.6% (n = 158). Rates of 30-day postoperative unplanned readmission and reoperation were 7.5% (n = 725) and 4.8% (n = 468). The ACS-SRC had the highest discrimination for all measured outcomes, as measured by the area under the receiver operating curve (AUC) and corresponding confidence interval (95% confidence interval [CI]). This included perioperative mortality (AUC = 0.74, 95% CI = 0.71-0.78), compared to RAI-rev (AUC = 0.66, 95% CI = 0.62-0.69) and 5-mFI (AUC = 0.61, 95% CI = 0.57-0.65; p < 0.001). The RAI-rev and 5-mFI had similar discrimination for all measured outcomes.
Conclusion:
ACS-SRC was the perioperative risk stratification tool with the highest predictive discrimination for adverse, 30-day, postoperative events for patients with cancer treated with anatomic lung resection.


Related Concept Videos
 01:20
Comparing the Survival Analysis of Two or More Groups
 01:21
Cancer Survival Analysis
 01:12
Relative Risk
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:25
Statistical Methods for Analyzing Epidemiological Data
 01:24
Kaplan-Meier Approach