Related Experiment Video
Updated: Jun 3, 2025
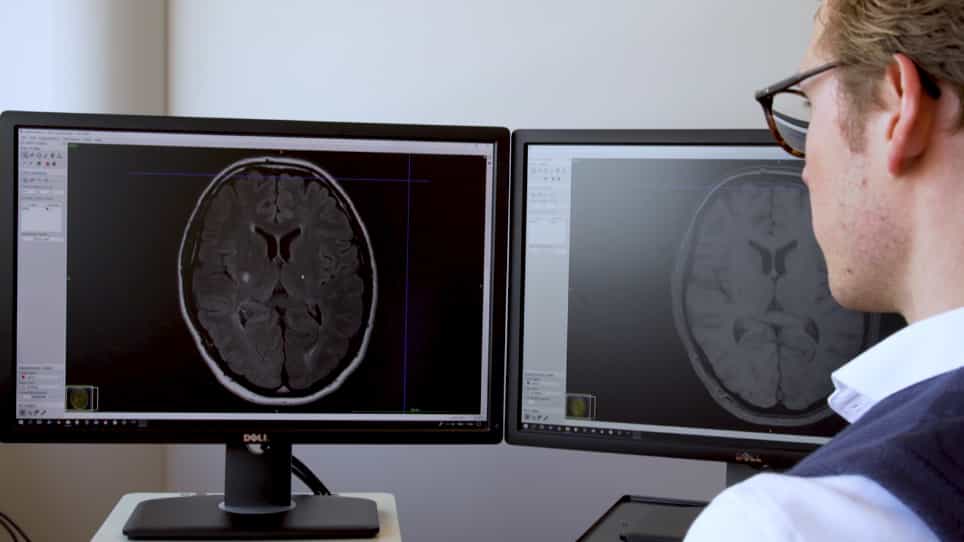

Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
Lesion Topography and Clinical Features Associated With Respiratory Failure in Patients With Medullary Infarction
Na Zhao1, Ran Liu1, Yajing Zhang1
1Department of Neurology, Tianjin Key Laboratory of Cerebrovascular and Neurodegenerative Diseases, Clinical College of Neurology, Neurosurgery and Neurorehabilitation, Tianjin Huanhu Hospital, Tianjin Medical University, Tianjin, China.

Background:
Respirator failure (RF) is a severe malignant complication in both lateral medullary infarction (LMI) and medial medullary infarction (MMI) patients. However, the differences in clinical and radiological manifestations associated with RF between patients with LMI and MMI have not been fully elucidated.
Methods:
A total of 435 consecutive patients with MI within 7 days of onset in our institute were retrospectively enrolled from January 2017 to January 2024. Lesions were categorized both rostral-caudally and horizontally, and clinical characteristics were collected to evaluate the correlation between them and RF that occurred within 10 days of stroke onset.
Results:
Among the 435 patients, 33 patients developed RF, with 19 exhibiting LMI and 12 exhibiting MMI. Multisegment involvement was more common among LMI patients experiencing RF compared to those without (52.6% vs. 23.9%, p = 0.012). However, this difference was not observed among MMI patients. Large (n = 12, 63.2%, p = 0.014) and typical (n = 6, 31.6%, p = 0.016) lesions were more common among LMI patients with RF. In MMI patients with RF, nine (75.0%) patients had long lesions extending from the ventral to the dorsal medulla, with six of these cases involving bilateral lesions, as V-shape or heart-shape on MRI. Univariate analysis of clinical symptoms revealed that bulbar symptoms, urinary retention, and pulmonary infection were significantly more common in both the LMI and MMI groups with RF.
Conclusions:
Specific lesion patterns, such as large and typical infarctions in LMI patients or long lesions, particularly those with bilateral infarctions, as V-shape or heart-shape on MRI in MMI patients, appear to correlate with a higher incidence of RF, while clinical symptoms associated with RF are similar in LMI and MMI.
Insights
Respirator failure (RF) risk is linked to specific stroke patterns in medullary infarction (MI). Lateral medullary infarction (LMI) with large lesions and medial medullary infarction (MMI) with long, bilateral lesions increase RF incidence.
Area of Science:
- Neurology
- Stroke Medicine
- Cardiovascular Research
Background:
- Respirator failure (RF) is a critical complication in both lateral medullary infarction (LMI) and medial medullary infarction (MMI).
- Understanding the distinct clinical and radiological features of RF in LMI versus MMI patients is crucial for improved patient outcomes.
Purpose of the Study:
- To investigate the differences in clinical and radiological manifestations of respirator failure (RF) between patients with lateral medullary infarction (LMI) and medial medullary infarction (MMI).
- To identify specific lesion patterns associated with RF in medullary infarction (MI).
Main Methods:
- Retrospective analysis of 435 consecutive medullary infarction (MI) patients within 7 days of onset.
- Categorization of lesions (rostral-caudal, horizontal) and collection of clinical data to assess correlation with RF within 10 days of stroke onset.
Main Results:
- Of 435 patients, 33 developed RF (19 LMI, 12 MMI).
- LMI patients with RF showed more multisegment (52.6% vs. 23.9%) and large/typical lesions (63.2%, 31.6%).
- MMI patients with RF often had long, bilateral lesions (75.0%), appearing V-shaped or heart-shaped on MRI. Bulbar symptoms, urinary retention, and pulmonary infection were common in both groups with RF.
Conclusions:
- Specific lesion patterns in LMI (large, typical) and MMI (long, bilateral, V- or heart-shaped on MRI) correlate with higher RF incidence.
- Clinical symptoms of RF, including bulbar symptoms and pulmonary infection, are similar across LMI and MMI patients.

Related Concept Videos
 01:23
Acute Respiratory Failure-IV
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...
 01:30
Acute Respiratory Failure-III