Relationship between lung consolidation size measured by ultrasound and outcome in ICU patients with respiratory failure
Related Experiment Video
Updated: May 25, 2025
Point-of-Care Lung Ultrasound in Adults: Image Acquisition
Published on: March 3, 2023
Na Wang1, Yi Chi1, Qianling Wang1
1Department of Critical Care Medicine, Peking Union Medical College Hospital, Chinese Academy of Medical Sciences, NO.1 shuaifuyuan, Dongcheng District, Beijing, China.

Background:
Lung ultrasound has been extensively used to assess the etiology of respiratory failure. Additionally, lung ultrasound-based scoring systems have been proposed to semi-quantify the loss of lung aeration in the ICU. The one most frequently used distinguishes four steps of progressive loss of aeration (scores from 0 to 3) and 3 scores mean tissue-like pattern. However, the burden of consolidation is not considered as tissue-like pattern is defined as 3 scores independently of its dimension. In this study, we present an ultrasound method for quantitative measurement of consolidation size and investigate the relationship between consolidation size and outcome in ICU patients with respiratory failure.
Methods:
A total of 124 patients in ICU were prospectively enrolled and 13 patients were excluded due to failure to obtain LUS measurements. Among the remaining 111 patients, 17 patients were non-intubated, and 94 patients under sedation and analgesia were intubated. All patients underwent lung ultrasound examination for the measurement of lung consolidation size between 24 and 48 h after ICU admission. Lung consolidation size was assessed by consolidation area index (CA), which was determined by tracing the maximum cross-sectional area of the region of consolidation. The Cox-regression model was constructed for 28- and 90-day mortality.
Results:
Consolidation size was successfully evaluated in all patients. The CA was 24.2cm2[15.9-36.6] (median [25th -75th percentiles]). CA was negatively correlated with PaO2/FiO2 ratio (r=-0.26, P < 0.0001). Upon univariate and multivariate analysis, only CA [Odds ratio (OR) 1.04, 95% CI 1.01-1.08, P = 0.004] and APACHEII (OR 1.14, 95% CI 1.05-1.25, P = 0.002) were the risk factors for ICU mortality. Patients with substantial CA (> 29.4cm2) had a higher risk of death in 28-day [Hazard ratio (HR) 4.35, 95%CI 1.70-11.11; Log-rank P = 0.017] and 90-day mortality (HR 4.10, 95%CI 1.62-10.39; Log-rank P < 0.01).
Conclusions:
The proposed CA parameter, determined by lung ultrasound, was readily accessible at the bedside. It is noteworthy that a larger CA was correlated with impaired oxygenation and increased mortality rates among ICU patients. Further investigation is required to establish the merits of incorporating CA into lung ultrasound assessments in the ICU.
Trial Registration:
ClinicalTrial.gov, Identifier NCT05647967, Date: Dec 13, 2022, retrospectively registered.
More Related Videos
 06:15
Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
 08:05
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Related Concept Videos
 01:15
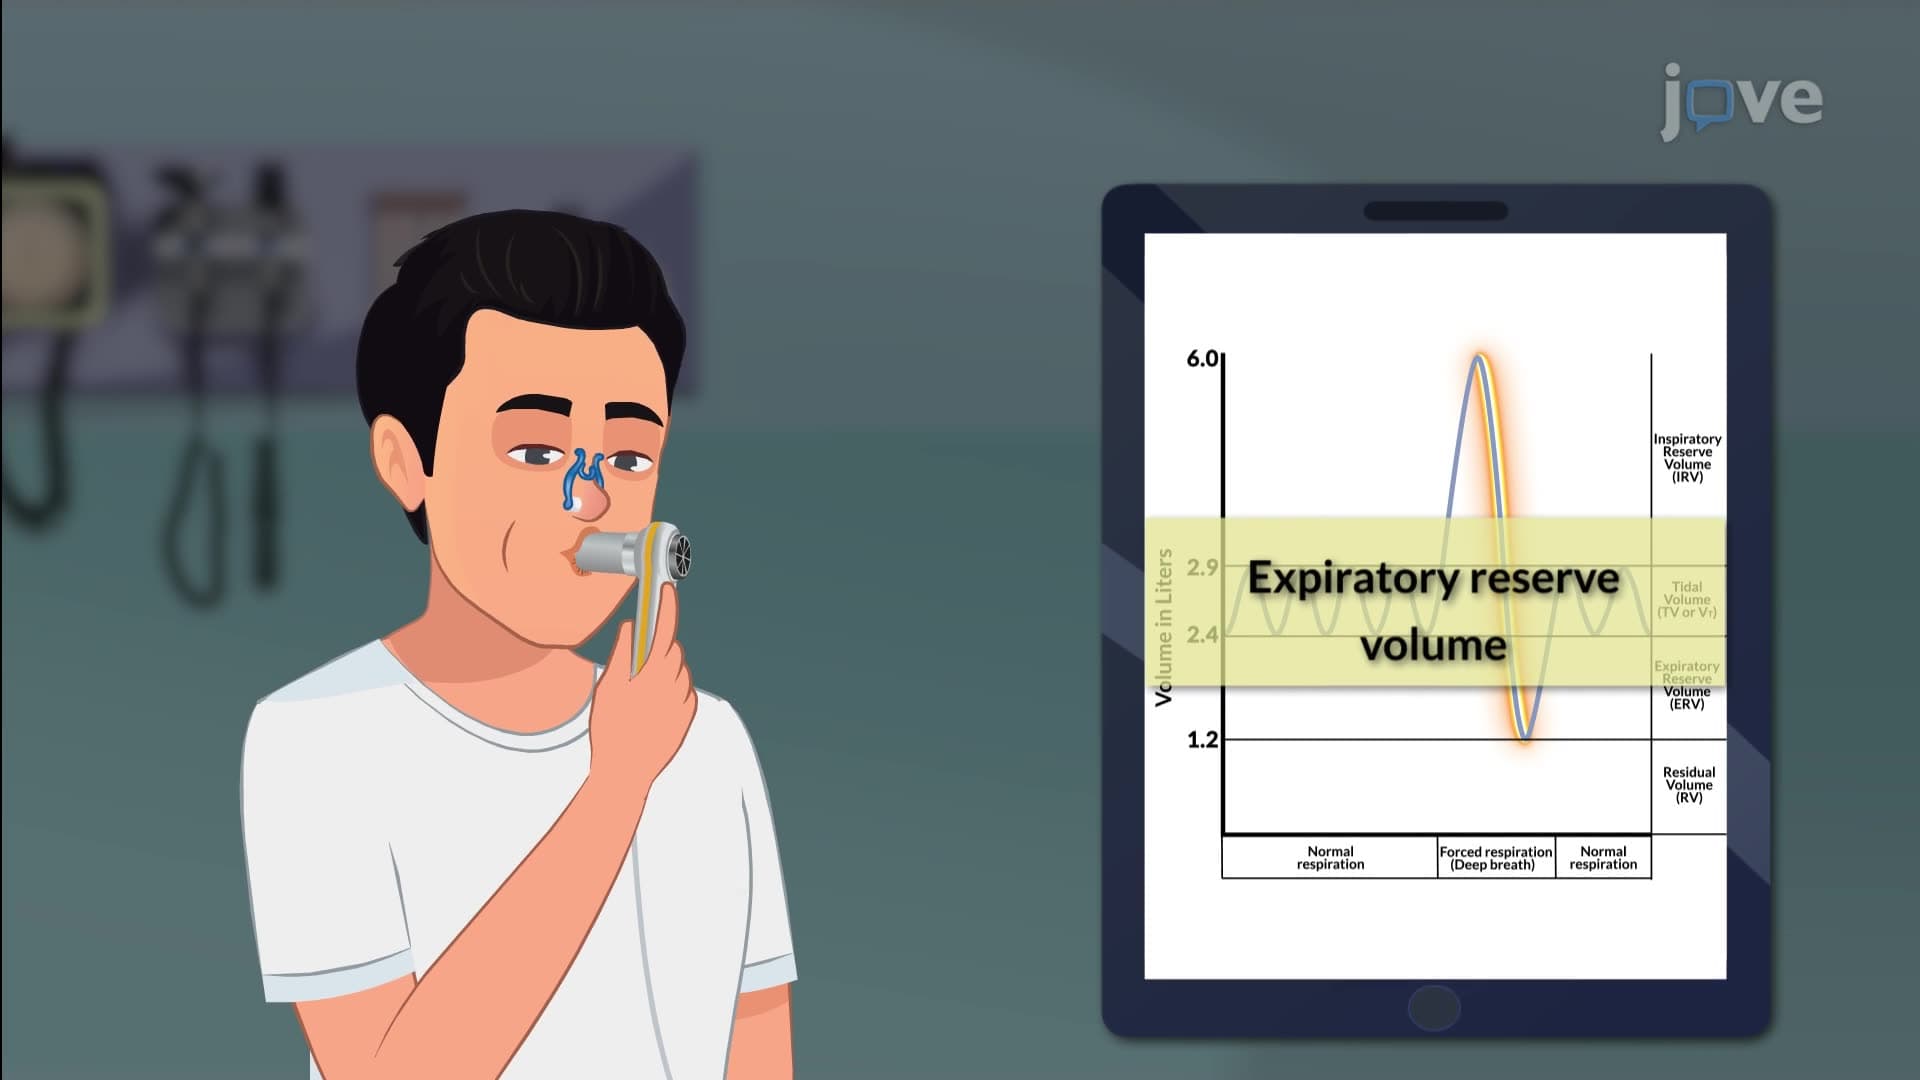
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:30
Radiological Investigation II: MRI and Ventilation Perfusion Scan
Magnetic Resonance Imaging (MRI) and Ventilation Perfusion Scans are two radiological investigations that offer detailed diagnostic images of the body, particularly lung structures.
MRI
MRI uses magnetic fields and radiofrequency signals to distinguish between normal and abnormal tissues. This technology provides a more detailed diagnostic image than CT scans, enabling it to characterize pulmonary nodules, stage bronchogenic carcinoma, and evaluate inflammatory activity in...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:24
Respiratory Capacities
One key metric is the Inspiratory Capacity (IC), which represents the maximum amount of air that can be inhaled with full effort. IC is calculated by summing the tidal volume and inspiratory reserve volume, typically ranging from 2.4 to 3.6 liters.
The Functional Residual Capacity (FRC) represents the air in the...