Related Experiment Video
Updated: May 23, 2025
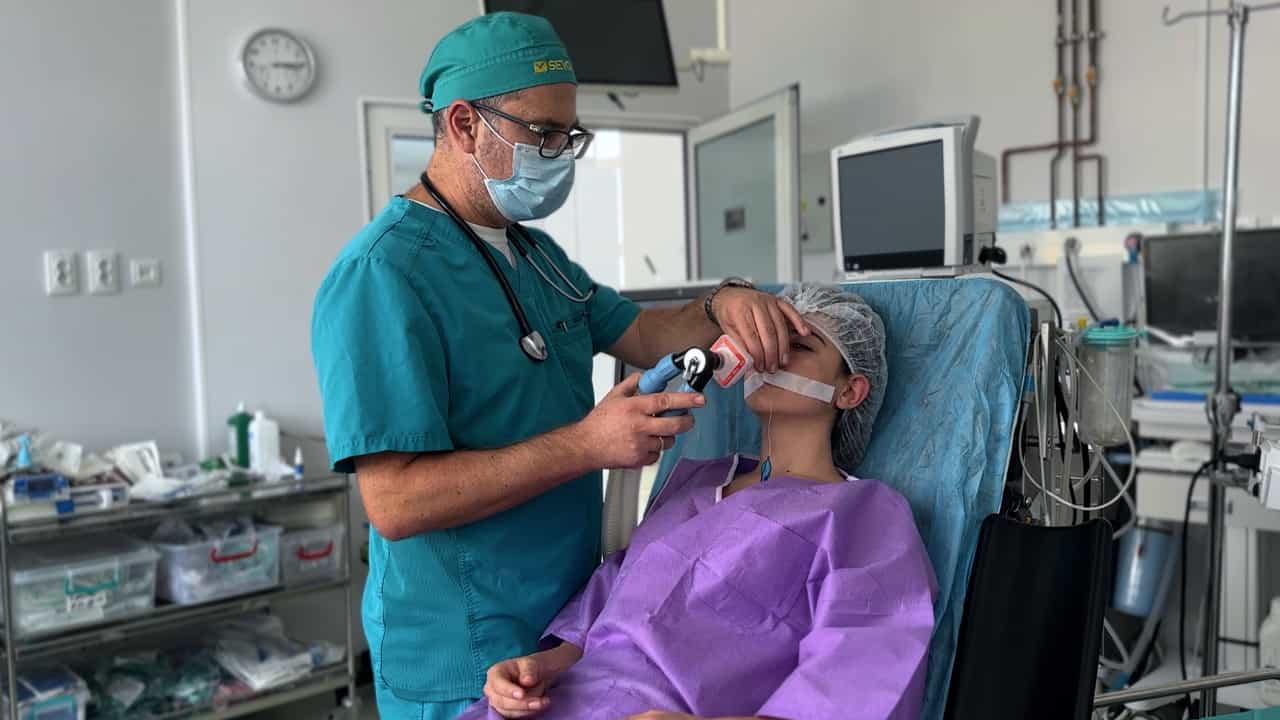
Author Spotlight: Advancing Awake Nasotracheal Intubation with Flexible Video Rhino-Laryngoscopes
Published on: August 2, 2024
Videolaryngoscope designs for tracheal intubation in adults: a systematic review with network meta-analysis of
Clístenes C de Carvalho1, Idrys H L Guedes1, Maria V M Dantas1
1Academic Unit of Medicine, Federal University of Campina Grande, Campina Grande, Brazil.

Introduction:
Videolaryngoscopy improves tracheal intubation outcomes compared with direct laryngoscopy in various scenarios. However, the range of videolaryngoscope designs makes it challenging to identify the most effective device. We conducted a systematic review and network meta-analysis to compare different laryngoscope designs when used for tracheal intubation of adults under general anaesthesia.
Methods:
We searched six databases for randomised controlled trials of patients aged ≥16 years, requiring tracheal intubation under general anaesthesia and evaluating comparisons between the following interventions: channelled videolaryngoscopes; Macintosh blades; hyperangulated blades; video stylets; and direct laryngoscopes. The primary outcome was the incidence of failed first tracheal intubation attempts. Secondary outcomes included failed tracheal intubation; tracheal intubation difficulty; glottic view; time to tracheal intubation; and incidence of complications.
Results:
We included 294 studies evaluating 44,284 patients. Channelled blades (OR (95%CrI) 0.37 (0.27-0.50), moderate certainty), Macintosh blades (OR (95%CrI) 0.45 (0.31-0.64), moderate certainty) and hyperangulated videolaryngoscopes (OR (95%CrI) 0.51 (0.39-0.68), moderate certainty) reduced the incidence of failed first tracheal intubation significantly compared with direct laryngoscopes, with channelled-blade devices ranking highest for this outcome. No significant difference was observed between video stylets and direct laryngoscopes for this outcome (OR (95%CrI) 0.67 (0.16-3.00), low certainty). All three videolaryngoscope designs also reduced failure rates across second and third tracheal intubation attempts; decreased the likelihood of difficult tracheal intubation; improved glottic view; and lowered the incidence of oesophageal intubation and airway tissue damage. Channelled- and hyperangulated-blade videolaryngoscopes significantly improved glottic view compared with Macintosh-blade designs.
Discussion:
We are moderately certain that the three designs of videolaryngoscopes enhance tracheal intubation effectiveness, safety and postoperative recovery compared with direct laryngoscopes. Channelled videolaryngoscopes and hyperangulated blades might provide superior glottic views compared with Macintosh-blade videolaryngoscopes. No definitive conclusions can be drawn regarding the comparative tracheal intubation performance across different video-assisted devices and designs.
Related Concept Videos
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask...