Related Experiment Video
Updated: May 15, 2025


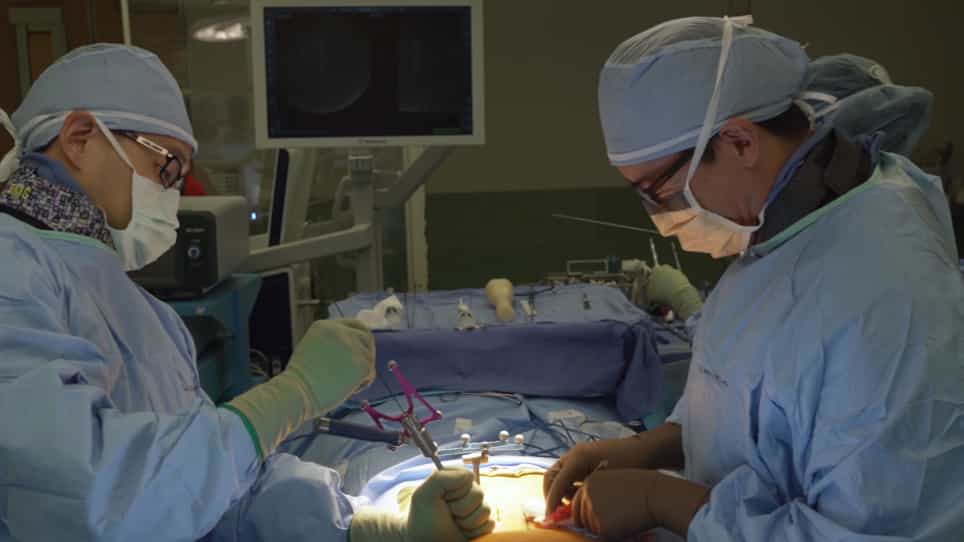
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Preoperative teriparatide intervention is cost-effective for osteoporotic patients undergoing lumbar fusion: a
Muhammad Waheed1, Dhiraj Patel2, Paul Anderson3
1Department of Orthopaedic Surgery, Detroit Medical Center, Detroit, MI, USA.

Background Context:
Lumbar spinal fusion is a common procedure increasingly being performed in older patients many of whom have poor bone quality. Poor bone quality is associated with increased risk of bone related complications and need for revision surgery. Preoperative bone health optimization has been proposed to address this poor bone health using antiosteoporosis medications. However, there remains ongoing controversy regarding the use of bisphosphonates and teriparatide for osteoporotic patients and few studies have explored the cost-effectiveness of teriparatide in lumbar spinal fusion.
Purpose:
The aim of the study is to determine the cost-effectiveness, quantified in terms of absolute risk reduction (ARR) and number needed to treat (NNT), of teriparatide to prevent symptomatic pseudarthrosis following lumbar spinal fusion.
Study Design/Setting:
Economic analysis, Level of Evidence 3.
Patient Sample:
The present break-even analysis considers simulated patients with and without osteoporosis undergoing primary posterior lumbar spinal fusion. The analysis is independent of the total number of annual surgeries and can be applied to any sized cohort of patients with osteoporosis undergoing primary posterior lumbar spinal fusion.
Outcome Measures:
We calculated the final break-even cost rate of pseudoarthrosis, the absolute risk reduction, and the number need to treat to prevent one symptomatic pseudoarthrosis event while breaking even on cost utilization.
Methods:
The MEDLINE database was queried for prior literature regarding the cost of teriparatide and revision lumbar fusion surgery for symptomatic pseudarthrosis in the United States as well as the rate of symptomatic bony nonunion in osteoporotic patients undergoing spinal fusion. Two break-even cost analyses were performed utilizing the surgical cost alone and the total overall cost to calculate the ARR in pseudarthrosis required to deem teriparatide as cost-effective. The ARR was then used to calculate the number of patients that would require teriparatide, NNT, to prevent one pseudarthrosis event while breaking-even on overall cost expenditure.
Results:
When observing surgical cost alone, daily-use teriparatide was determined to be positively cost effective at initial rates of pseudarthrosis >53.4% in osteoporotic patients. Utilization of the total overall cost in our break-even model showed daily-use teriparatide to be cost effective when the initial nonunion rate exceeded 30.6%. Teriparatide was not cost-effective at lower initial rates of pseudarthrosis for osteoporotic patients. In both scenarios of investigating total overall cost and surgical cost alone, the ARR decreases as the cost of symptomatic pseudarthrosis treatment rises. At higher costs of revision surgery and higher initial pseudarthrosis rates, teriparatide becomes cost-effective at a more efficient rate.
Conclusions:
Daily-use teriparatide is a cost-effective treatment for preventing symptomatic pseudarthrosis in osteoporotic patients undergoing lumbar spinal fusion, with a NNT of 5 in this population.