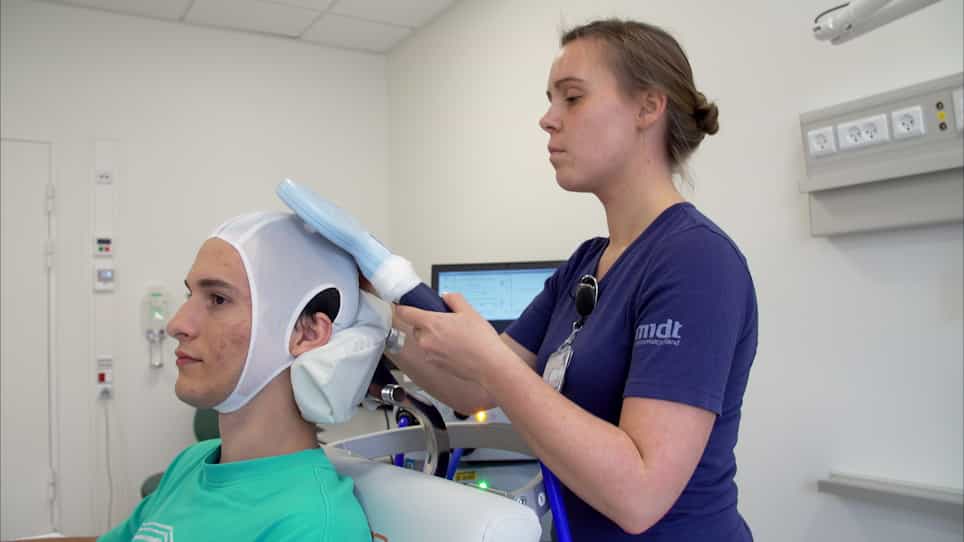
Quantitative tremor monitoring before, during and after MR-guided focused ultrasound thalamotomy for essential tremor with MR compatible accelerometers
Related Experiment Video
Updated: May 22, 2025
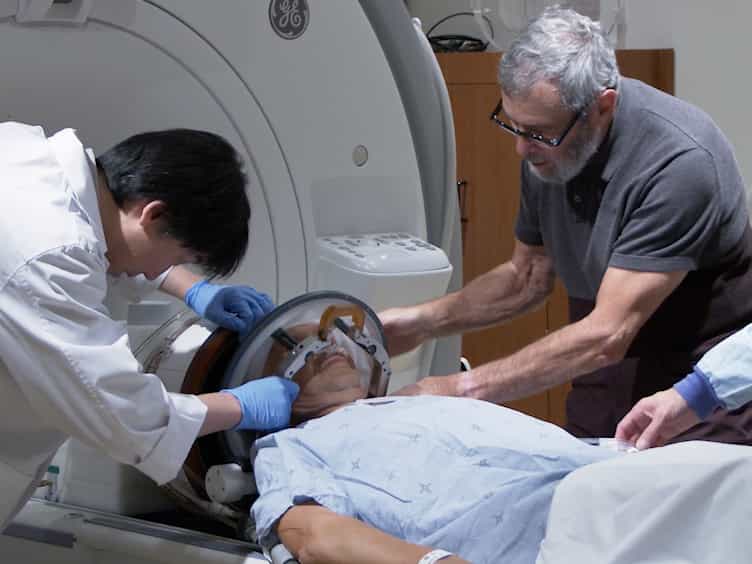
MRI-guided Focused Ultrasound Thalamotomy for Patients with Medically-refractory Essential Tremor
Published on: December 13, 2017
Thomas Bancel1, Mohammed Bashaiweth1, Thomas J Manuel1
1Physics for Medicine Paris, INSERM U1273, CNRS UMR 8063, ESPCI Paris, Paris Science Lettres University (PSL), Paris, France.

Background:
MR-guided focused ultrasound (MRgFUS) has been developed to treat essential tremor effectively and noninvasively. Currently, clinical examination is used to identify therapeutic efficacy during treatment, but MRgFUS surgery could benefit from real-time, rater-independent quantitative monitoring of tremor, such as accelerometry data.
Methods:
Fourteen patients with medically refractory essential tremor underwent MRgFUS thalamotomy. Patients were instructed to hold postures during treatment. Tremor was monitored during each ultrasonic thermal sonication with MR-compatible accelerometers. Real-time feedback based on tremor amplitude in the 2-20 Hz band was calculated to evaluate the efficacy of each thermal ablation.
Results:
On average 6 ± 2 ablative sonications only were required to induce improvement in tremor on the clinical rating scale for tremor (CRST) of 89 ± 11% at D + 7, 79 ± 12% at M + 1, 74 ± 19% at M + 3 and 72 ± 23% at M + 12. The overall predictive efficacy measured with accelerometry during the treatment was 70 ± 30%. The tremor amplitude reduction measured with accelerometry was correlated with CRST scores tremor reduction at multiple timepoints (ρ = 0.79 at D + 7, ρ = 0.75 at M + 1, ρ = 0.86 at M + 3, and ρ = 0.63 at M + 12) and accelerometric data gathered during treatment predicted CRST tremor improvement at M + 3 (0.88 area under ROC curve).
Conclusion:
This exploratory study is a proof of concept suggesting that accelerometry measurements can provide real-time feedback on tremor reduction and can complement visual evaluation. In the future, the use of the outcome prediction introduced in this paper may shorten procedure time and limit adverse events by reducing the number of ablative administered sonications.