
Income-related disparities in sudden cardiac arrest among young adults: a nationwide cohort study
Joo Hee Jeong1, Kyung-Do Han2, Seung-Young Roh3
1Division of Cardiology, Department of Internal Medicine, Korea University Anam Hospital, Seoul, Korea (the Republic of).

Background:
Socioeconomic disparities are associated with sudden cardiac arrest (SCA) in older populations, but evidence in young adults is limited. We investigated the association between income status, geographical region and SCA risk among young adults in South Korea.
Methods:
Using the Korean National Health Insurance Service database, we identified 6 307 644 adults aged 20-39 years who underwent health screening between 2009 and 2012. Income status was defined by insurance premium quartiles and medical aid status. The primary outcome was incident SCA through December 2020. Multivariable Cox regression models were used to estimate adjusted HRs with 95% CIs.
Results:
Over a mean follow-up of 9.4 years, 5340 individuals (0.08%) experienced SCA. Crude incidence rates were similar across income quartiles (0.09 per 1000 person-years) but highest among medical aid beneficiaries (0.28 per 1000 person-years; 95% CI 0.21 to 0.39). After multivariable adjustment, higher income was associated with lower SCA risk (adjusted HR for highest vs lowest quartile 0.67; 95% CI 0.61 to 0.73), while medical aid beneficiaries had substantially higher risk (adjusted HR 3.44; 95% CI 2.49 to 4.74). Geographical variation in SCA incidence was modest, and no significant interaction between income status and region was observed. Mediation analysis showed that modifiable risk factors explained only a small proportion of the income-SCA association.
Conclusions:
Lower income status, particularly receipt of medical aid, was independently associated with higher SCA risk among young adults. Socioeconomic disparities in SCA risk were not fully explained by lifestyle or metabolic factors.

Related Concept Videos
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:33
Adult Stem Cells
 01:19
Blood Studies for Cardiovascular System II: CRP, Hcy, and Cardiac Natriuretic Peptide Markers
These markers indicate stress or strain on the heart muscle:
Natriuretic Peptides (BNP)
Cardiac myocytes produce these hormones in response to ventricular stretching...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
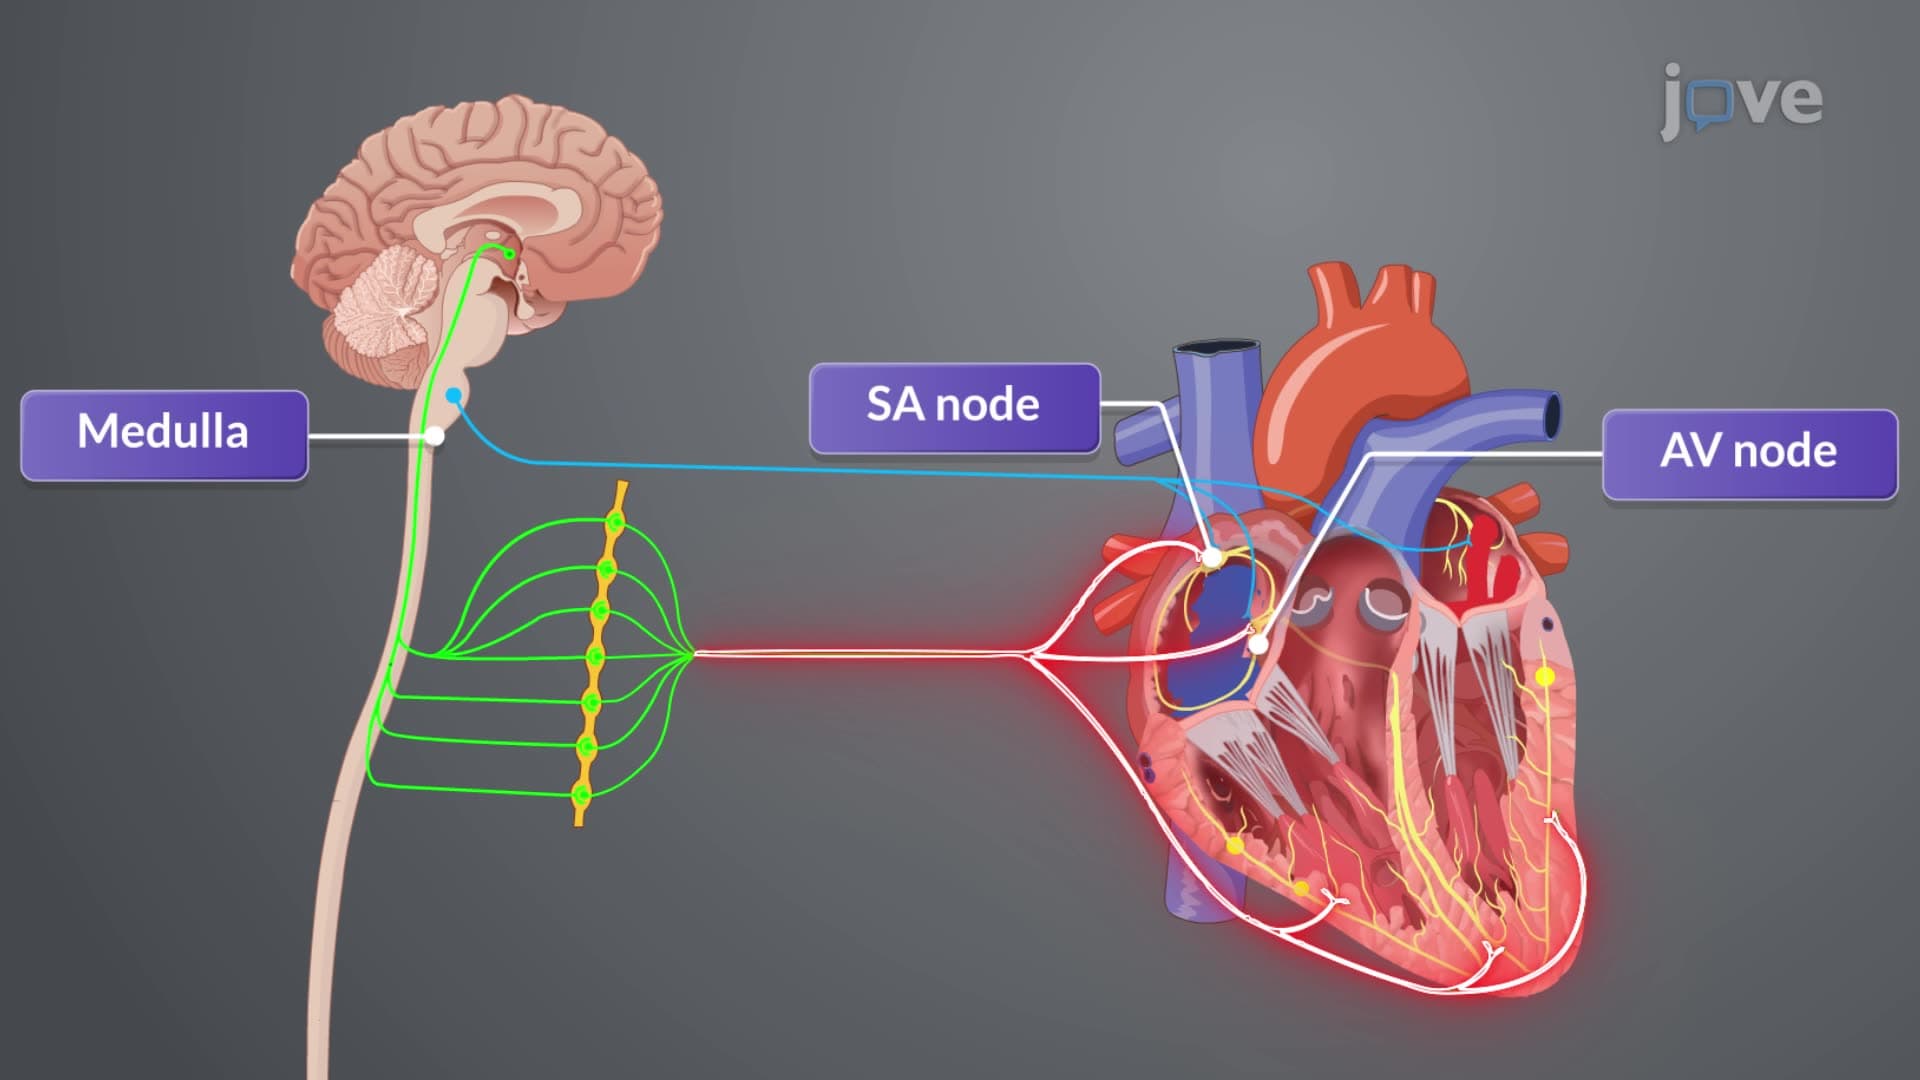
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:13
The Cardiac Cycle
The Process
Electrical signals—sent from the sinoatrial (SA) node in the right atrial wall to the atrioventricular (AV) node between the right atrium and right ventricle—cause both atria to simultaneously contract. When the signal reaches the AV node, it pauses for approximately a tenth of a second, allowing the atria to contract and...