Related Experiment Video
Updated: Feb 4, 2026


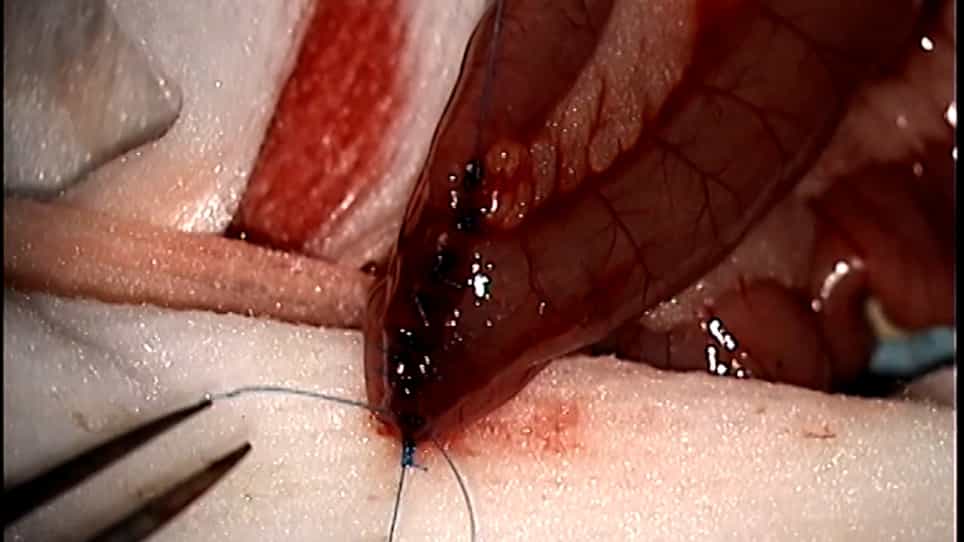
Roux-en-Y Gastric Bypass Operation in Rats
Published on: June 11, 2012
Late Jejunojejunal Perforation After Laparoscopic Roux-en-Y Gastric Bypass: A Systematic Narrative Review
Oday Al-Asadi1, Karim Ataya2, Almoutuz Aljaafreh3
1General Surgery, Homerton University Hospital, London, GBR.

Abstract:
Late perforation of the jejunojejunal (JJ) anastomosis after laparoscopic Roux-en-Y gastric bypass (LRYGB) is an exceedingly uncommon but potentially life-threatening complication. The widely non-specific presentation and the vast range of possible causes can delay diagnosis and increase morbidity. In this study, we aim to integrate the results of published literature on late JJ perforation after LRYGB in terms of patients' clinical characteristics, presentation, duration between the RYGB operation and the onset of JJ perforation, possible causes, as well as the outcome of the patients. We performed a comprehensive literature search of PubMed, CINAHL Plus, Embase, and EBSCOhost from inception to October 2025 using terms related to "Roux-en-Y gastric bypass," "jejunojejunal," "JJ," and "perforation." Case reports and case series describing late JJ perforation after LRYGB in adults were eligible. Two reviewers independently screened titles, abstracts, and full texts. Data were extracted on patient characteristics, time from index operation to perforation, predisposing factors, diagnostic tools, operative findings, and outcomes. Evidence was reviewed systematically and then narratively synthesised. A meta-analysis was not possible due to the case-based nature of the available literature. Eight studies reporting 12 patients with late JJ perforation following LRYGB were identified. Most patients were middle-aged females and presented months to years after surgery with severe, acute abdominal pain, with no specific localising signs. Radiological findings were variable and occasionally non-diagnostic. Proposed mechanisms included marginal ulcers, ischaemia, infection, stress, phytobezoar, and tumour implantation. All patients required operative management, most commonly laparoscopic suture repair or revision of the JJ anastomosis, with generally favourable outcomes with early treatment. Although late JJ perforation after LRYGB is exceptionally rare, it should be considered in any patient presenting with an acute abdomen with a past history of bariatric operation, irrespective of the interval since surgery. Early radiological assessment with cross-sectional studies, a low threshold for diagnostic laparoscopy, and urgent surgical intervention are crucial. Standardised reporting of future cases and collaborative registries are required to define incidence, risk factors, and best management strategies.

Related Concept Videos
 01:10
Review and Preview
Percentiles are a type of fractile that partition data into...
 01:13
Review and Preview
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:16
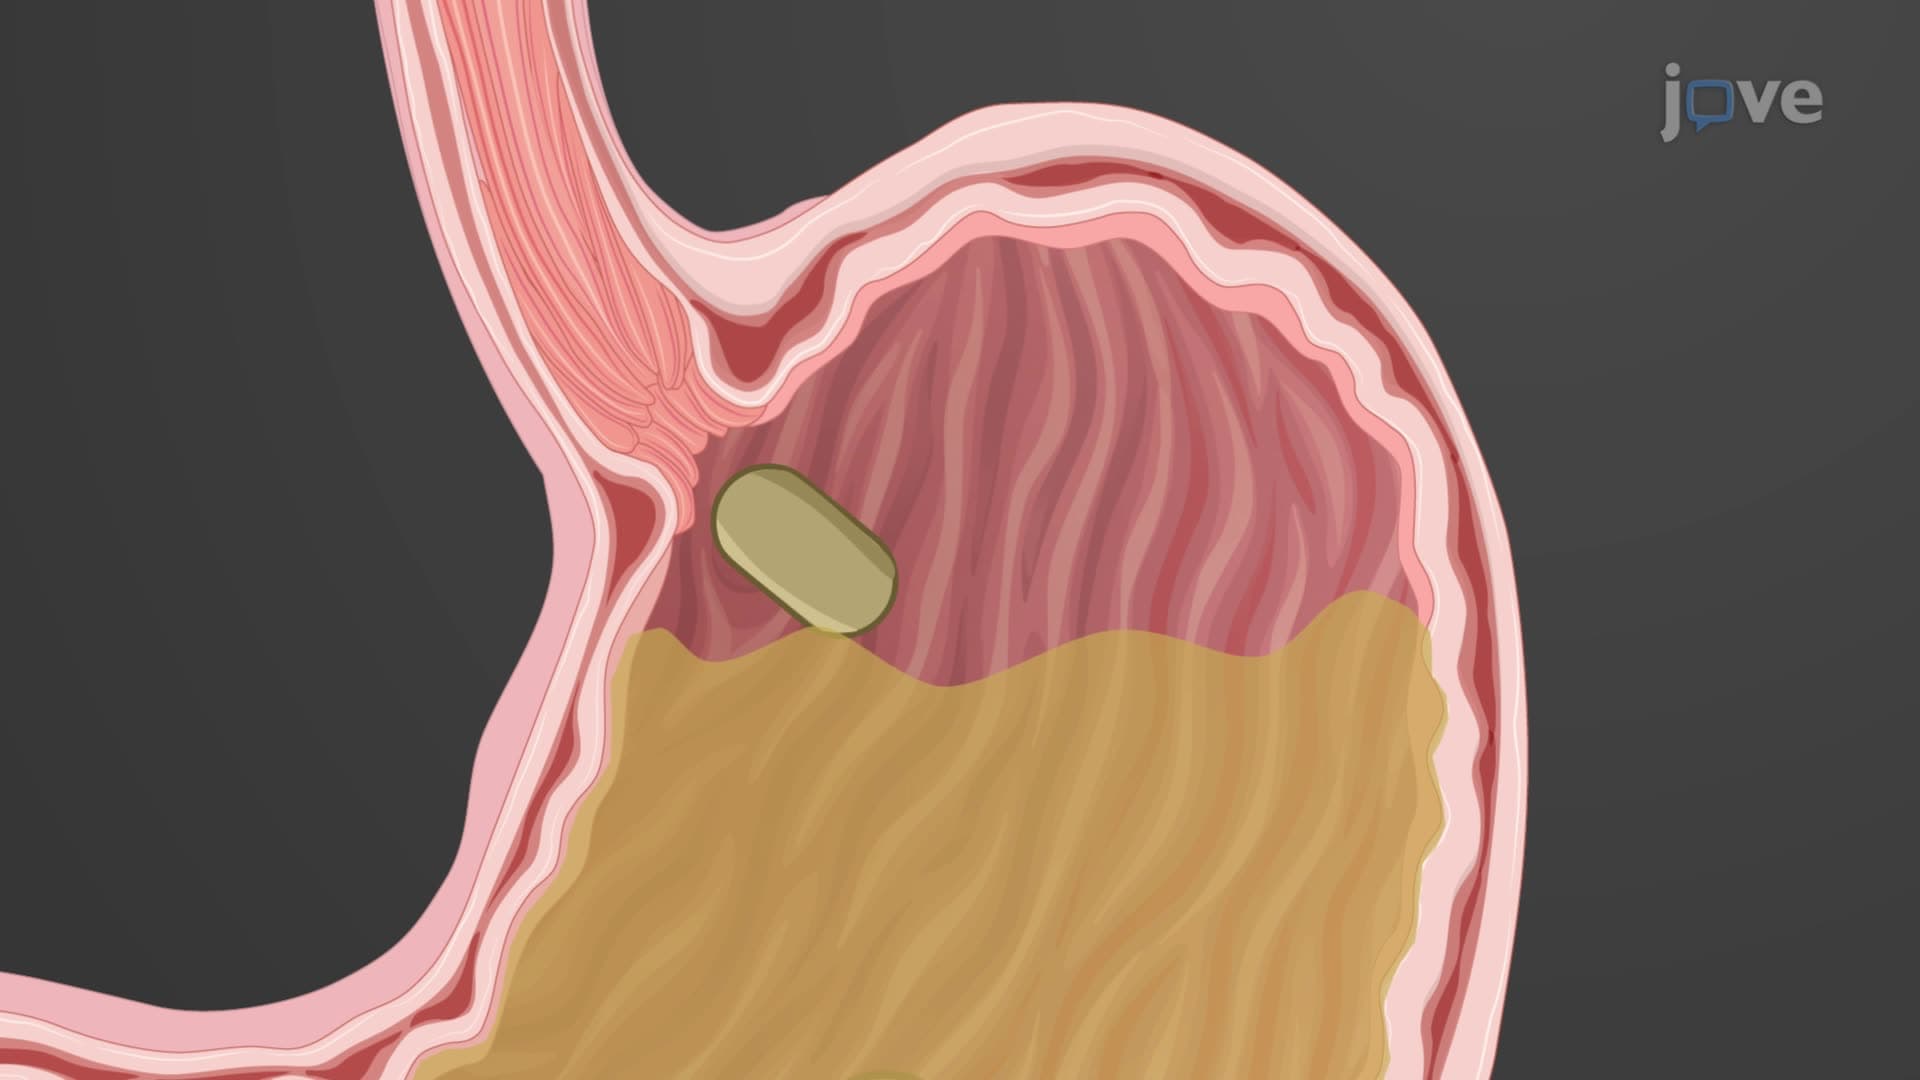
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:20
Random and Systematic Errors
 01:16
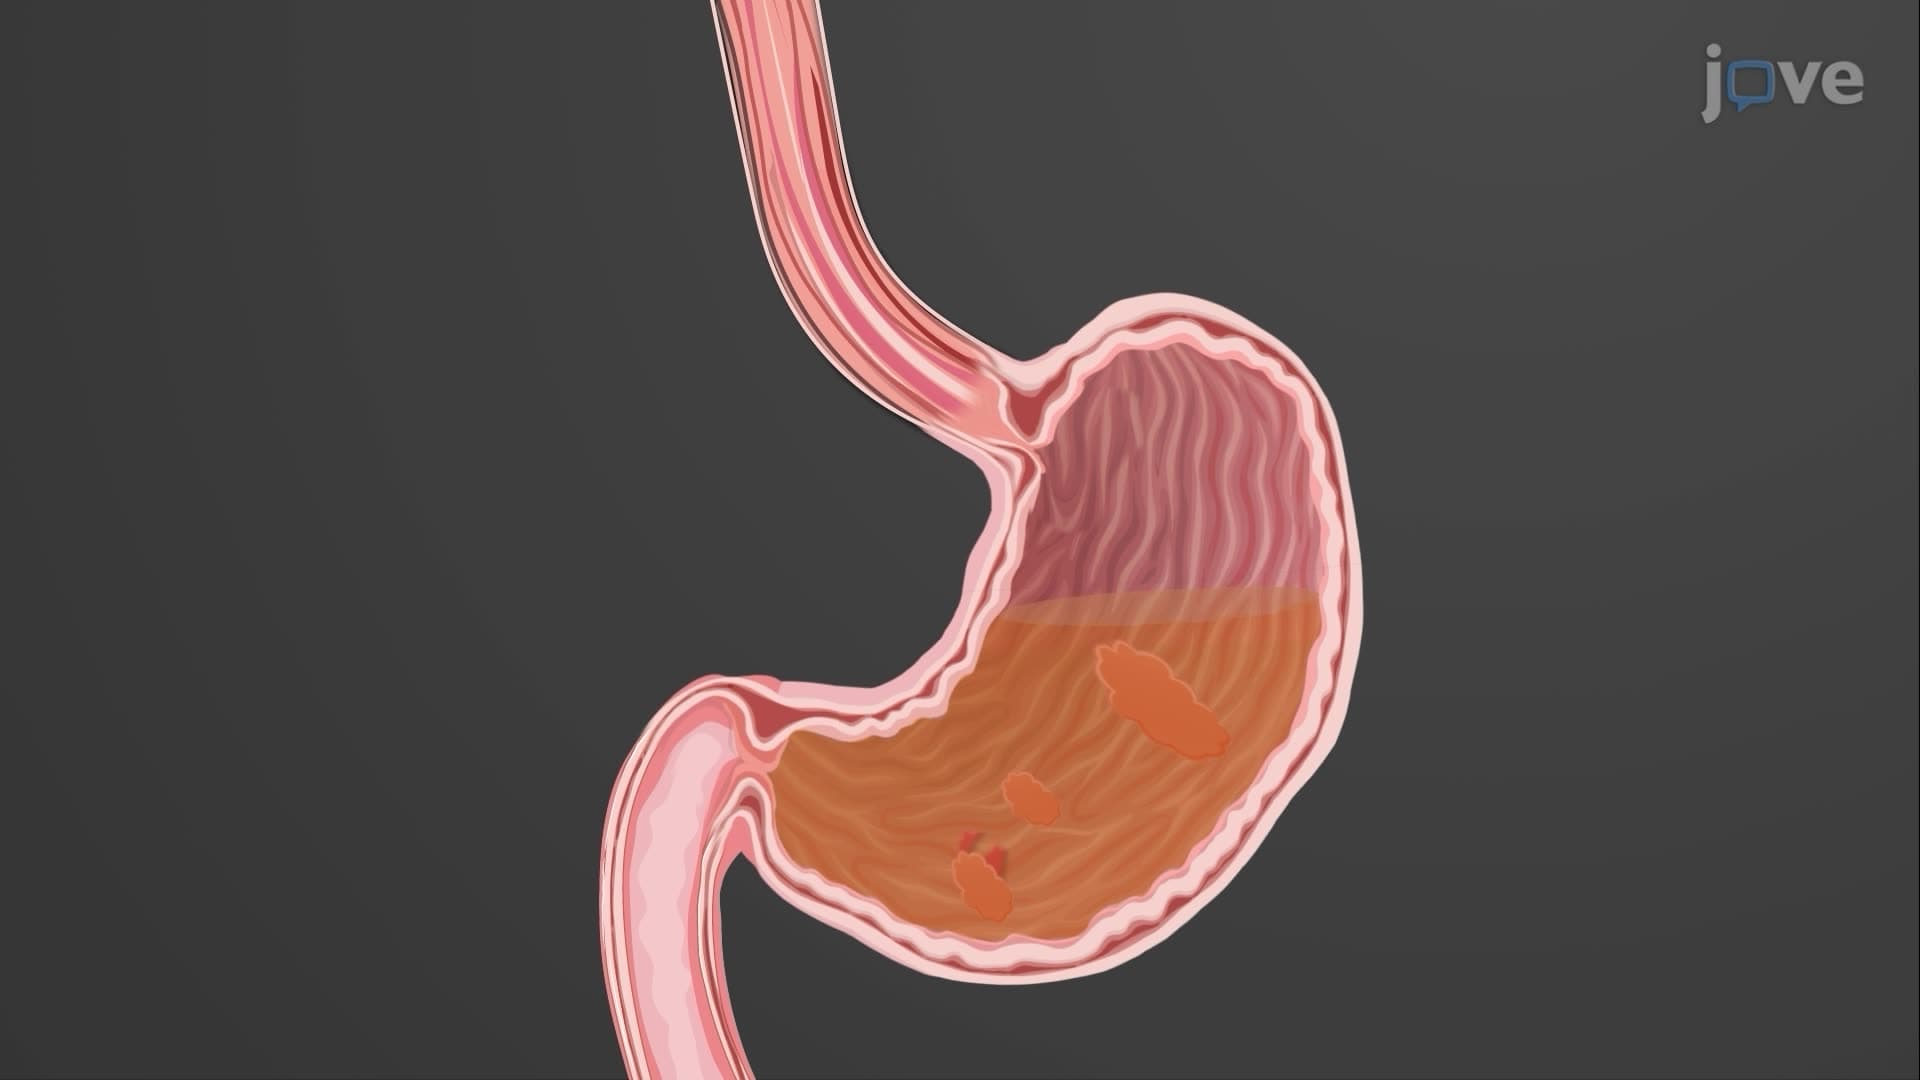
Gastric Emptying