Related Experiment Video
Updated: Mar 17, 2026

A Rehabilitation Program of Exoskeleton-assisted Body Weight-Supported Treadmill Training with Non-immersive Virtual Reality for Stroke Patients
Published on: May 16, 2025
Exoskeletal-Assisted Training in Veterans With Chronic Stroke: A Pilot Study
Michael Elliott1, Ingrid Lee1, Korishma Patram1,2
1Spinal Cord Damage Research Center, James J. Peters VA Medical Center, Bronx, NY.

Objective:
To determine the safety and feasibility of using a robotically powered exoskeleton in outpatient stroke survivors (>6mo). Treatment effect and functional outcome data were explored.
Design:
Safety and feasibility pilot study.
Setting:
Veterans Affairs Medical Center.
Participants:
Convenience sample of 10 stroke survivors (N=10) who were independent ambulators but had mild-moderate limitations.
Interventions:
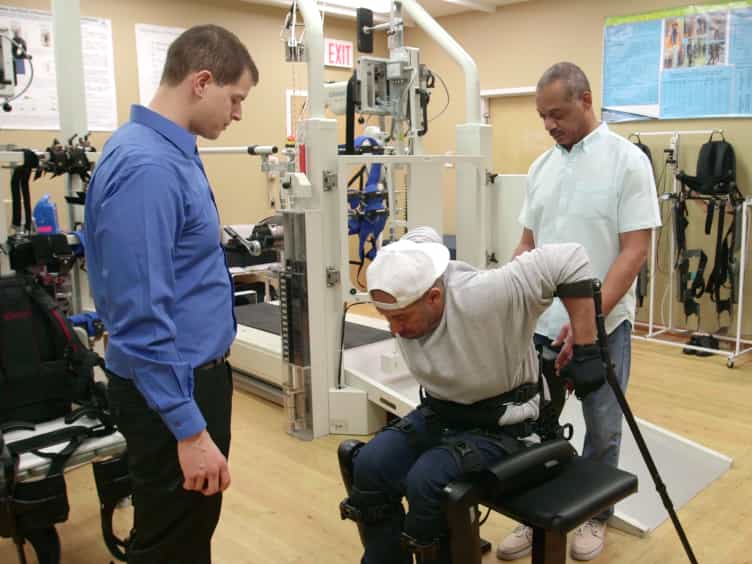
Standard of care (SOC) rehabilitation and SOC plus a robotic exoskeleton (SOC+Exo). Both groups received 1 hour of outpatient gait, transfer, and mobility training, 3 times per week for 12 weeks. The SOC+Exo group performed all SOC training activities while wearing the Keeogo Dermoskeleton (KExo).
Main Outcome Measures:
Safety was determined by adverse events (AEs), and feasibility by retention rate, adherence, participants' subjective satisfaction across 8 KExo use aspects, and trainers' subjective effort on 5 KExo donning/doffing tasks. Exploratory outcomes included the 5 Times Sit-to-Stand Test (5 × STS), distance and timed walking tests, stair climbing test, and step length during gait.
Results:
Twenty-two participants were screened; 16 were eligible and enrolled in the protocol. Four were randomized to SOC rehabilitation and 12 to the SOC+Exo intervention. Early study termination occurred in 1 SOC (noncompliance) and 5 SOC+Exo participants (because of time commitment or noncompliance). Two study-related AEs occurred. Both AEs were resolved, and the participants continued in the protocol. Ten (3 SOC; 7 SOC+Exo) of the initial 16 participants completed the study, demonstrating a 63% retention rate. The 10 retained participants demonstrated a 100% adherence rate. Most participants were satisfied with KExo assistance. Trainers reported providing only supervision when using the device. Nonparametric analysis suggests improvement (pre-post) in the SOC+Exo group without the device for 5 × STS (mean ± SD, -20.3±14.2s; P=.018), gait speed (mean ± SD, 0.24±0.34m/s; P=.046), and paretic leg step length (mean ± SD, 8.4±15.5cm; P=.018).
Conclusions:
Use of a robotically powered exoskeleton to augment SOC outpatient stroke rehabilitation was safe and feasible, and the protocol was well tolerated by participants and trainers. The effects of SOC+Exo training on the exploratory outcomes appear promising and warrant further investigation for efficacy in a more rigorous randomized controlled trial.