Related Experiment Video
Updated: Apr 15, 2026
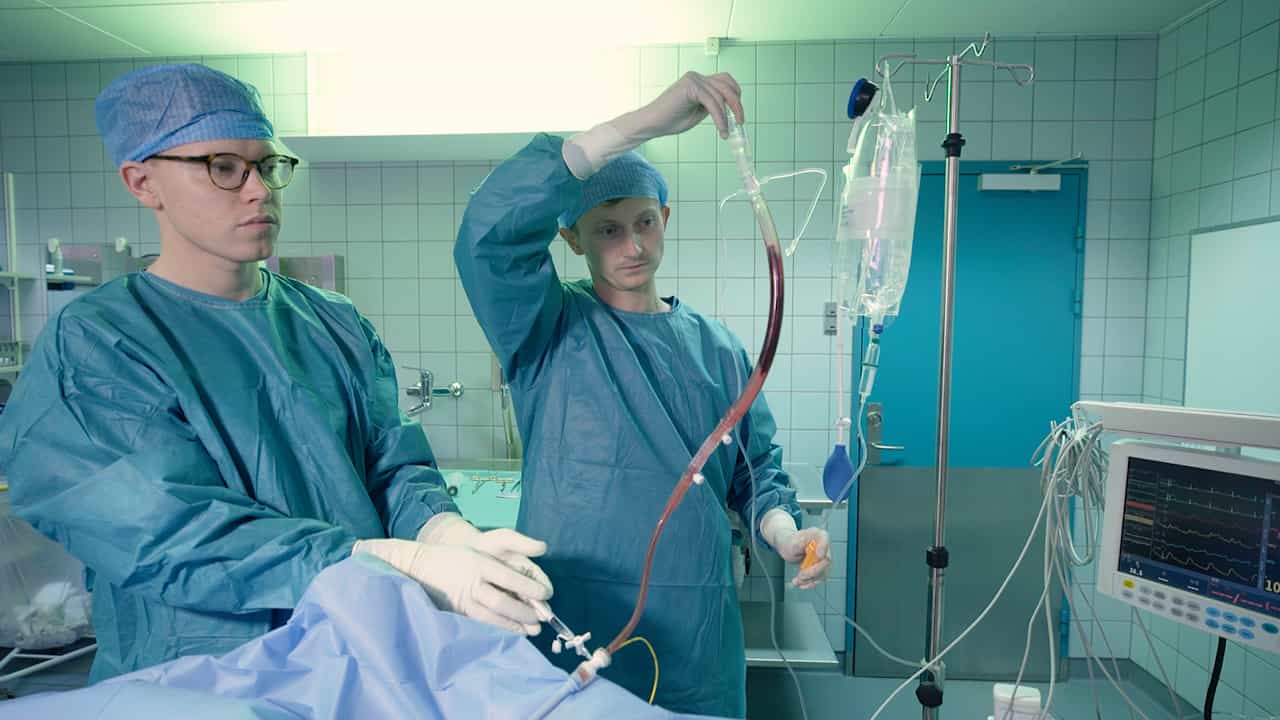
A Porcine Model of Acute Autologous Pulmonary Embolism
Published on: September 6, 2024
Prognostic Value and Sex-Related Differences in Chest Pain in Patients with Acute Pulmonary Embolism: A Prospective
David Frumkin1,2,3, Marie C Merten4, Ann-Sophie Eggers2,3,5
1Deutsches Herzzentrum der Charité, Department of Cardiology, Angiology and Intensive Care Medicine, Campus Charité Mitte, Charitéplatz 1, 10117 Berlin, Germany.

Abstract:
Background: While previous studies indicate an association between chest pain and favorable clinical outcomes in patients with pulmonary embolism (PE), the extent and underlying mechanisms of this effect remain inadequately defined. Methods: We investigated the prognostic value of chest pain with regard to in-hospital adverse outcomes and the association of chest pain with age and sex in consecutive patients with confirmed PE enrolled in a single-center registry between 2008 and 2019. Results: Of 858 patients (52% female) included in this study, 435 (51%) had chest pain at presentation. Chest pain was more prevalent in younger individuals aged 18-34 years (74%) compared to patients >34 years (46%). The prevalence of coronary artery disease (CAD) was similar in patients with and without chest pain (17.0% vs. 16.1%). Chest pain patients less frequently presented with elevated troponin levels (p < 0.001) or signs of right heart strain (RHS; p = 0.007) but more frequently exhibited imaging signs of pulmonary infarction (p = 0.001). Chest pain was associated with lower risk of adverse outcome (OR 0.35 [95% CI: 0.19-0.65]) and in-hospital mortality (OR 0.31 [95% CI: 0.13-0.74]). Multivariable models confirmed a prognostic effect independent of sex, comorbidities and results of risk stratification algorithms. Conclusions: In acute PE, chest pain is a favorable prognostic marker irrespective of sex. Chest pain patients are less likely to suffer from myocardial ischemia or show signs of RHS but more frequently show imaging signs of pulmonary infarction, suggesting pleuritic irritation rather than myocardial ischemia as the likely cause of pain.
More Related Videos


Related Concept Videos
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:29
Pulmonary Embolism I: Introduction
 01:27
Pulmonary Embolism III: Nursing Management
 01:29
Angina III: Clinical Manifestations and Assessment
 01:19
Pericarditis II: Clinical Features and Diagnostic Tests
 01:30
Acute Coronary Syndrome III: Diagnostic Studies