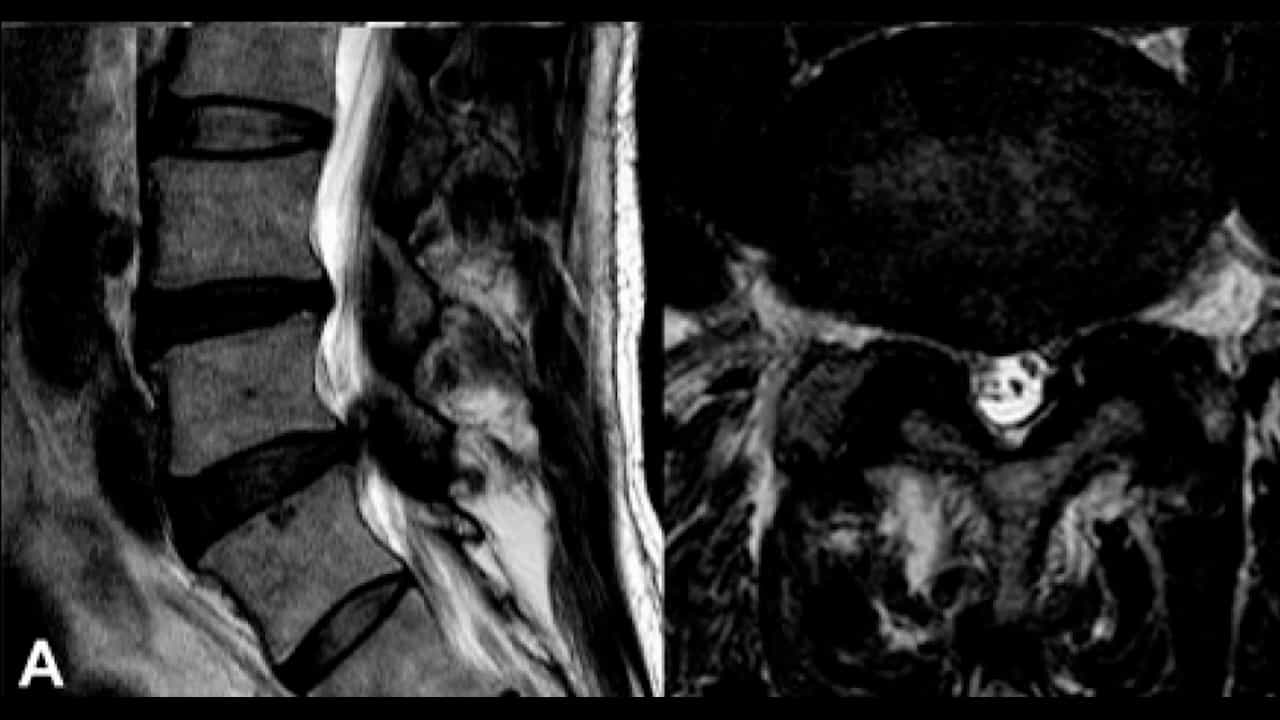
Related Experiment Video
Updated: Jul 14, 2026

Transtubular Endoscopic Posterolateral Decompression for L5-S1 Lumbar Lateral Disc Herniation
Published on: October 14, 2022
[Full-endoscopic modified versus traditional foraminotomy for lumbar foraminal stenosis: a comparison of clinical
1Department of Orthopedics, Miyun Hospital, Peking University First Hospital, Beijing 101500, China Department of Orthopedics, Beijing Friendship Hospital, Capital Medical University, Beijing 100050, China.

Abstract:
Objective: To compare the clinical outcomes of modified full-endoscopic foraminotomy versus conventional foraminotomy in the treatment of lumbar foraminal stenosis. Methods: A retrospective analysis was conducted on the clinical data of patients who underwent uniportal full-endoscopic foraminotomy for foraminal stenosis at Beijing Friendship Hospital between January 2022 and December 2023. The patients were divided into two groups based on whether sublaminar resection of the superior vertebral lamina was performed: the modified group (superior articular process resection combined with ventral sublaminar decompression of the superior vertebral lamina) and the conventional group (superior articular process resection alone). The clinical data were collected for both groups, included age, gender, body mass index (BMI), stenotic segment, and stenosis grade. The visual analog scale (VAS) for low back pain and leg pain were recorded preoperatively and at 1 week, 6 months, 1 year postoperatively. Clinical outcomes at 1 year after the operation were evaluated using the modified MacNab criteria. Perioperative complications and the rate of reoperation within one year were recorded. The foraminal area before and after surgery was compared between the two groups using sagittal CT reconstruction. Results: A total of 72 patients were included in this study, with 38 in the traditional group and 34 in the modified group. There was no statistically significant differences between the two groups in terms of age, gender, BMI, stenotic level, or grade of stenosis (all P>0.05). No significant differences were observed in the VAS scores for low back pain between the two groups preoperatively or at 1 week, 6 months, 1 year postoperatively (all P>0.05). There was no significant difference in preoperative leg pain VAS scores between the two groups (P>0.05). The modified group demonstrated significantly lower postoperative VAS scores for lower limb pain compared to the traditional group at all follow-up time points: at 1 week [(1.91±0.57) vs (2.10±0.61) points, P=0.004], at 6 months [(1.35±0.95) vs (2.05±0.61) points, P<0.001], and at 1 year [(0.85±0.70) vs (1.55±0.98) points, P=0.029]. According to the modified MacNab criteria, the excellent-to-good rate was 91.2% (31/34) in the modified group and it was 86.8% (33/38) in the traditional group (P=0.559). The incidence of perioperative complications was comparable between the modified group (2.9%, 1/34) and the traditional group (5.3%, 2/38) (P=0.623). The foraminal area was significantly enlarged in both groups postoperatively. The modified group exhibited a significantly larger postoperative foraminal area [(181.4±9.6) mm²] compared to the traditional group [(165.5±10.1) mm²) (P<0.001). Conclusion: Full-endoscopic modified transforaminal decompression provides more extensive decompression and better improvement in leg pain symptoms compared to traditional transforaminal endoscopic decompression in patients with lumbar foraminal stenosis.