Related Experiment Video
Updated: May 7, 2026

Use of a Percutaneous Ventricular Assist Device/Left Atrium to Femoral Artery Bypass System for Cardiogenic Shock
Published on: August 16, 2021
Robot-assisted partial nephrectomy during simultaneous extracorporeal membrane oxygenation and impella®in a candidate
Francesco Cianflone1, Giuseppe Ottone Cirulli1, Alessio Villano1
1Department of Urology, Fondazione IRCCS Policlinico San Matteo, Pavia, 27100, Italy.

Background:
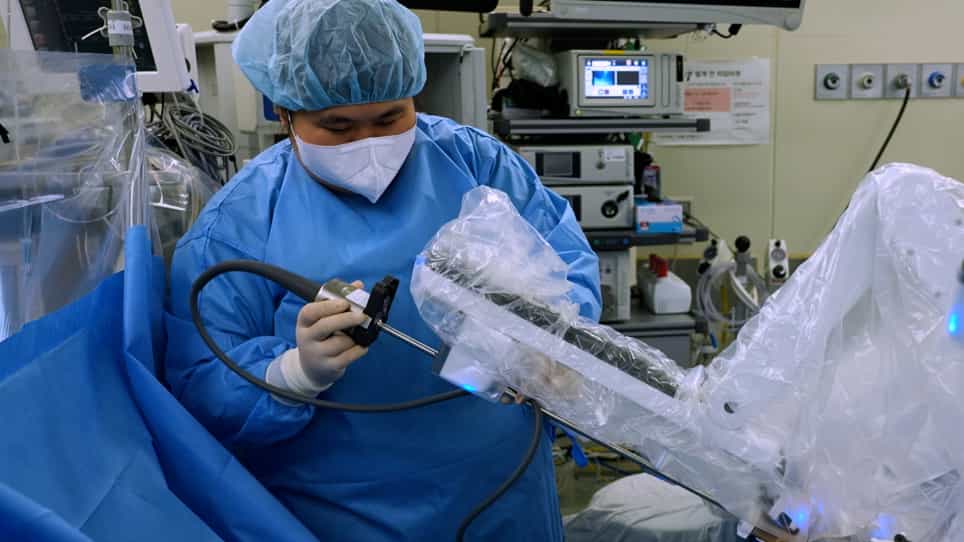
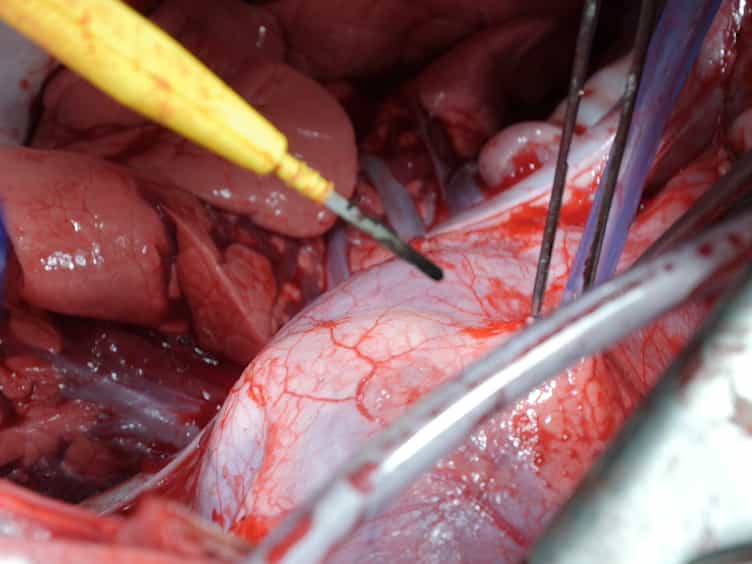
Robot-assisted partial nephrectomy (RAPN) is standard for cT1 renal masses, but its feasibility in patients on temporary mechanical circulatory support is poorly documented. We report RAPN performed while a patient was simultaneously supported with venous-arterial extracorporeal membrane oxygenation (VA ECMO) and Impella®, as part of a staged plan for left ventricular assist device (LVAD) implantation and eventual heart transplantation.
Case Presentation:
A 51-year-old man presented with ST-elevation myocardial infarction complicated by cardiogenic shock requiring percutaneous coronary intervention with stenting, dual antiplatelet therapy, and combined VA ECMO-Impella® support. During workup for cardiac transplant, computed tomography (CT) staging revealed a 16-mm left renal mass suspicious for renal cell carcinoma. A multidisciplinary team prioritized definitive treatment to preserve transplant eligibility and elected RAPN under systemic heparinization alongside aspirin continuation (cangrelor briefly withheld). Therefore, RAPN was performed with 9 min of warm ischemia. The intraoperative course was hemodynamically stable. On postoperative day (POD) 4, late arterial bleeding from the resection bed was controlled by selective angioembolization. On POD 7, a durable LVAD was implanted as a bridge to heart transplantation. Final pathology showed pT1a, G2, R0 clear cell renal cell carcinoma. At 6 months, contrast-enhanced CT showed no recurrence and no major cardiovascular complications.
Conclusions:
RAPN during simultaneous ECMO and Impella® support is technically feasible with meticulous anticoagulation management, interventional radiology standby, and coordinated planning. This approach enables oncologic control while preserving a trajectory to transplant candidacy.