Related Experiment Video
Updated: May 8, 2026


Human Serum Anti-aquaporin-4 Immunoglobulin G Detection by Cell-based Assay
Published on: April 5, 2019
A unified spectrum model for the anti-GQ1b antibody syndromes: from pathophysiology to a new diagnostic framework
Khalil El Abdi1, Fazeela Bibi2, Muhammad Ibrahim3
1Faculty of Medicine and Pharmacy of Rabat, Mohammed V University, Rabat, Morocco.

Background:
Bickerstaff Brainstem Encephalitis (BBE) is a rare, post-infectious autoimmune disorder characterized by ophthalmoplegia, ataxia, and altered consciousness. Its significant clinical and serological overlap with Miller Fisher syndrome (MFS) and Guillain-Barré syndrome (GBS) creates diagnostic challenges, particularly in atypical or seronegative presentations. These conditions are collectively understood as components of the anti-GQ1b antibody syndrome, a spectrum of neuro-immune disorders.
Aims:
This review provides a clinically focused, integrative synthesis of the anti-GQ1b antibody spectrum, with an emphasis on BBE. We aim to clarify the underlying pathophysiology, delineate the range of clinical phenotypes, provide a structured framework for diagnosis that acknowledges the limitations of ancillary testing, and summarize current evidence for therapeutic strategies.
Synthesis Of Evidence:
Pathogenesis is primarily driven by anti-GQ1b IgG antibodies, generated following infection via molecular mimicry, which trigger complement-mediated damage to ganglioside-rich neural structures. The clinical presentation ranges from purely peripheral deficits (MFS) to severe central nervous system dysfunction (BBE), with frequent BBE-GBS overlap syndromes. Diagnosis hinges on clinical recognition, supported by serology, with neuroimaging serving a crucial role in excluding mimics. Approximately one-third of clinically defined BBE cases are seronegative, suggesting alternative mechanisms. Prompt immunotherapy with intravenous immunoglobulin (IVIg) or plasma exchange is the cornerstone of management, extrapolated from GBS trials, while evidence for corticosteroids remains limited.
Conclusion:
A structured, spectrum-based perspective remains essential for clinicians navigating the diagnostic complexities of the anti-GQ1b antibody syndromes. This updated synthesis is intended to enhance diagnostic accuracy, guide therapeutic reasoning across the full range of phenotypes, and highlight key unresolved questions to inform a future research agenda.


Related Concept Videos
 01:15
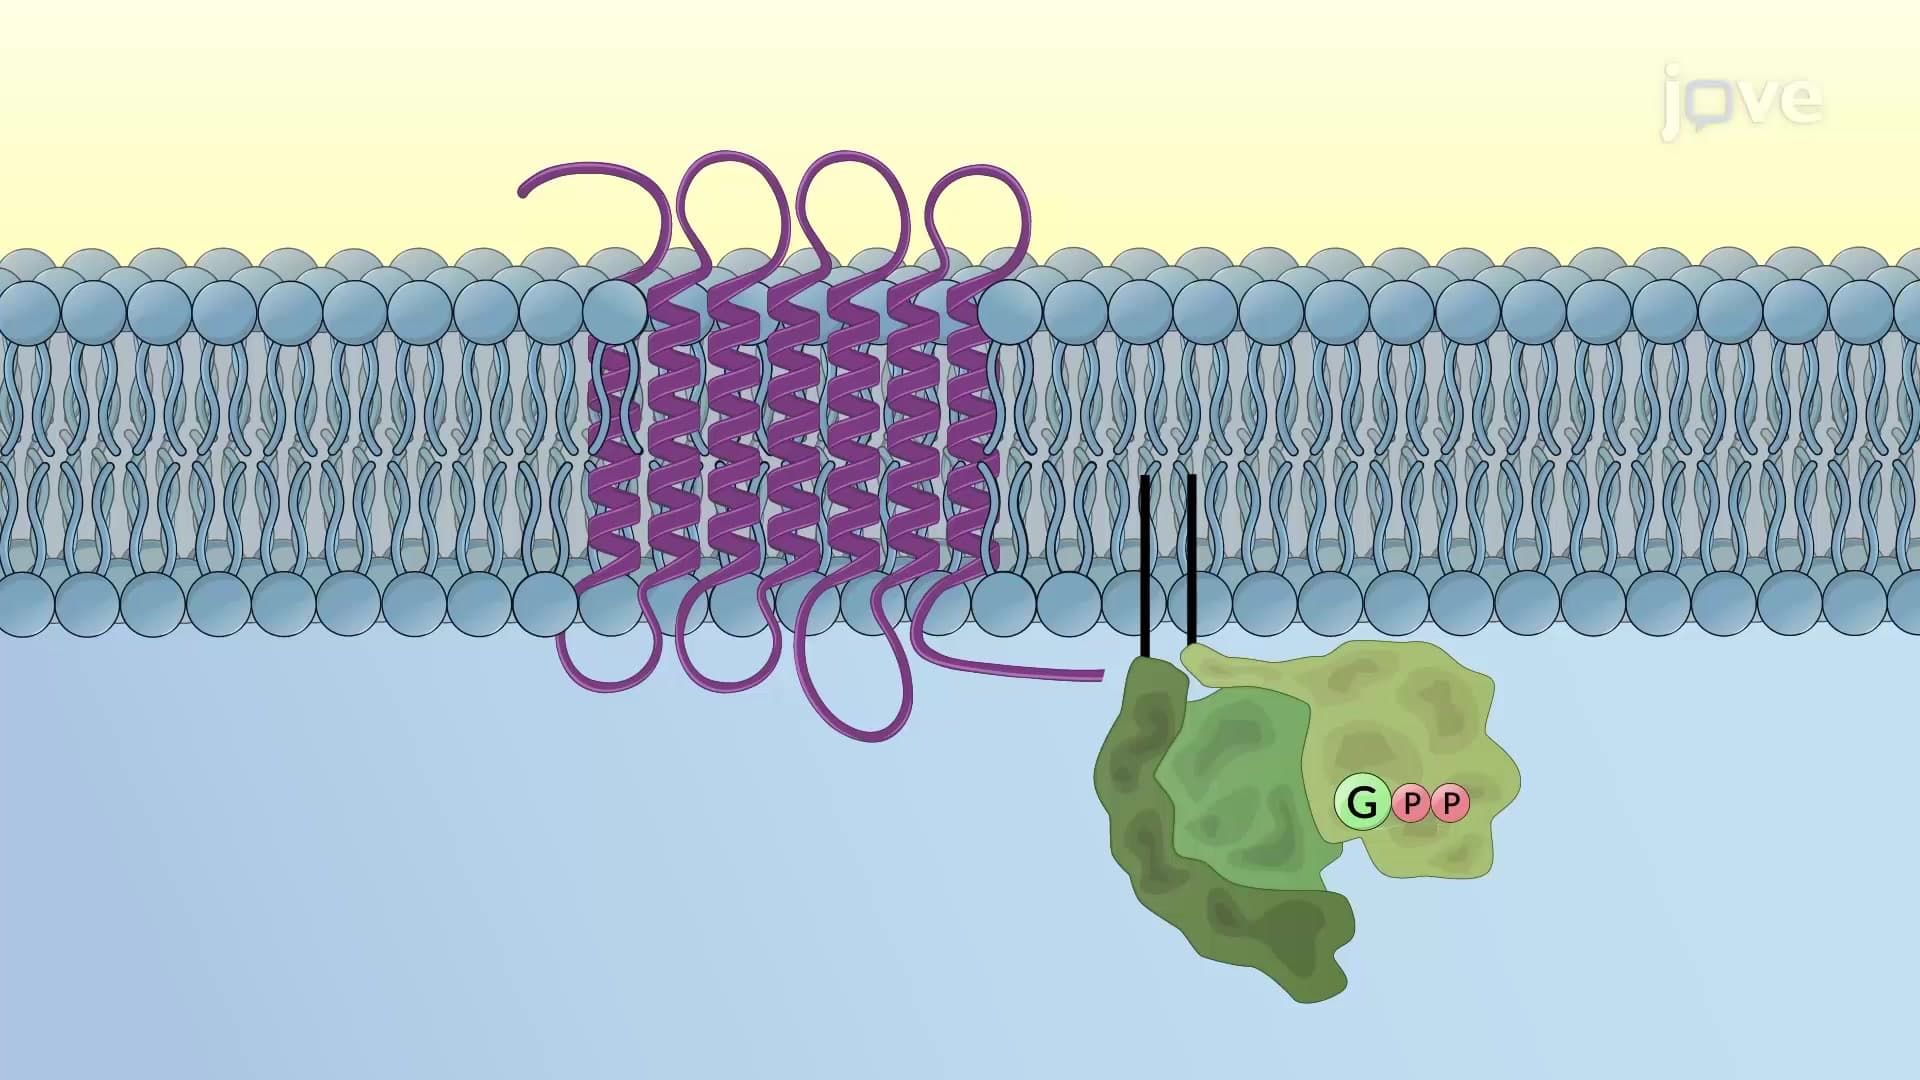
G Protein-coupled Receptors
GPCRs are also called heptahelical, 7TM, or serpentine receptors, and consist of seven (H1-H7) transmembrane alpha-helices that span the bilayer to form a cylindrical core. The transmembrane helices are connected by three extracellular loops and three...
 01:22
Myasthenia Gravis ll: Pathophysiology
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:29
Pharmacogenomics: Identification of New Drug Targets