Related Experiment Video
Updated: Oct 10, 2026
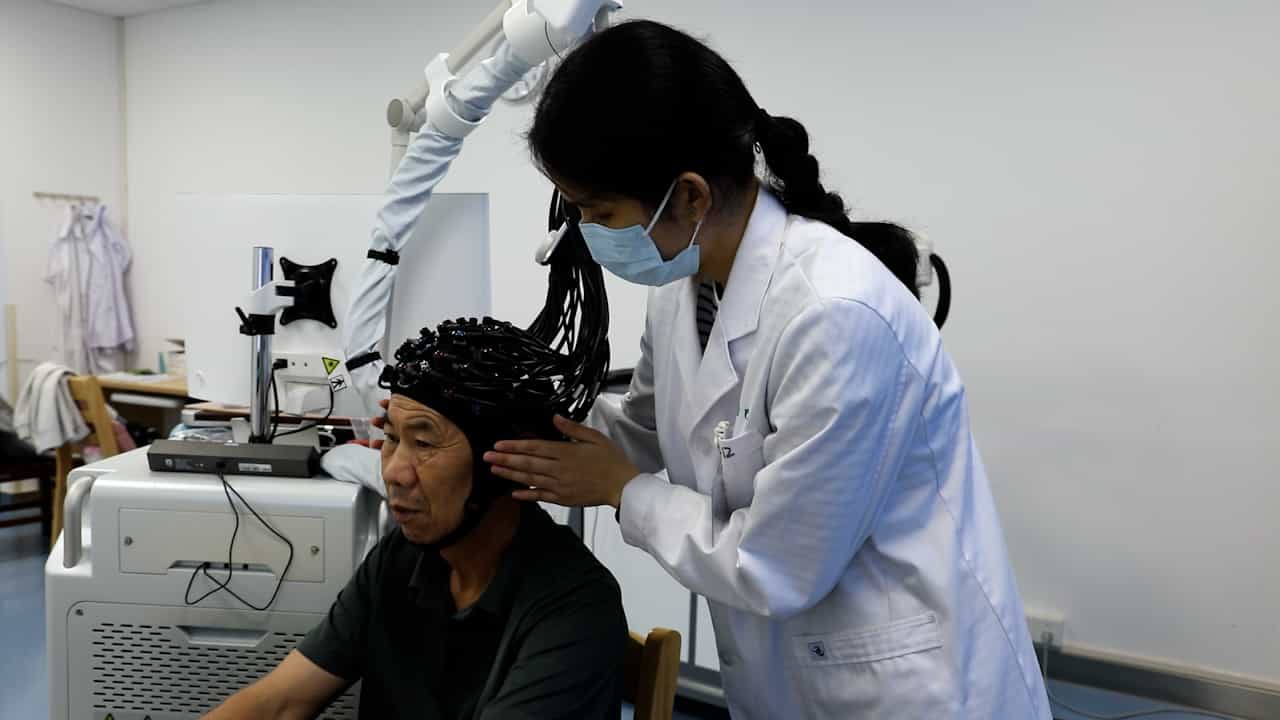

Soft Pneumatic Robot Modulates Graph Theory Metrics of Brain Network for Hand Rehabilitation After Stroke
Published on: October 10, 2025
Inflammatory profiling for precision neurorehabilitation after traumatic brain injury and stroke: a narrative review
Rocco Salvatore Calabrò1, Andrea Calderone1, Alessio Ardizzone2
1Department of Neurorehabilitation, IRCCS Centro Neurolesi Bonino Pulejo, Messina, Italy.

Introduction:
Recovery after traumatic brain injury (TBI) and stroke is heterogeneous, even among patients with similar lesion burden, clinical severity, and rehabilitation exposure. Neuroinflammation is a biologically plausible contributor, but evidence that inflammatory state modifies the effect of a specific rehabilitation treatment remains limited.
Methods:
This structured narrative review, informed by the Scale for the Assessment of Narrative Review Articles (SANRA), evaluates inflammatory biomarkers as candidate modifiers of response to therapeutic exercise, robotics, virtual reality (VR), telerehabilitation, and non-invasive brain stimulation (NIBS). PubMed, Scopus, Embase, and Web of Science were searched from inception through March 23, 2026. Eligibility, selection logic, evidence charting, and a population, intervention, comparator, and outcome framework are reported in tabular Supplementary Material. Evidence was classified as direct interventional, observational human, preclinical or mechanistic, or conceptual inference.
Results:
Inflammatory state is not a simple harmful vs. beneficial binary: timing, persistence, cellular context, structural reserve, systemic physiology, and treatment dose shape interpretation. Blood and cerebrospinal fluid markers, including interleukin-6, C-reactive protein, glial fibrillary acidic protein, neurofilament light chain, and composite immune indices, can support clinically meaningful, longitudinal biological phenotyping, but sampling and assay heterogeneity limit clinical translation. A small randomized stroke study linking very early exercise, serial inflammatory changes, and functional outcomes provides emerging direct evidence, although it did not establish biomarker-defined treatment effect modification. For stroke, human biomarker and rehabilitation evidence is comparatively developed, but prospective interaction testing remains scarce. For TBI, evidence is substantially weaker and predominantly indirect or mechanistic.
Discussion:
Accordingly, the proposed multimodal framework is a hypothesis for prospective trial enrichment, not a validated treatment matching algorithm. Its clinical value depends on standardized serial sampling, dose documentation, rehabilitation-specific outcomes, and externally validated prospective interaction testing within conditions. No single blood test or panel can currently identify rehabilitation responders, and inflammation-guided treatment assignment is not ready for routine care.
