Related Experiment Video
Updated: May 29, 2026
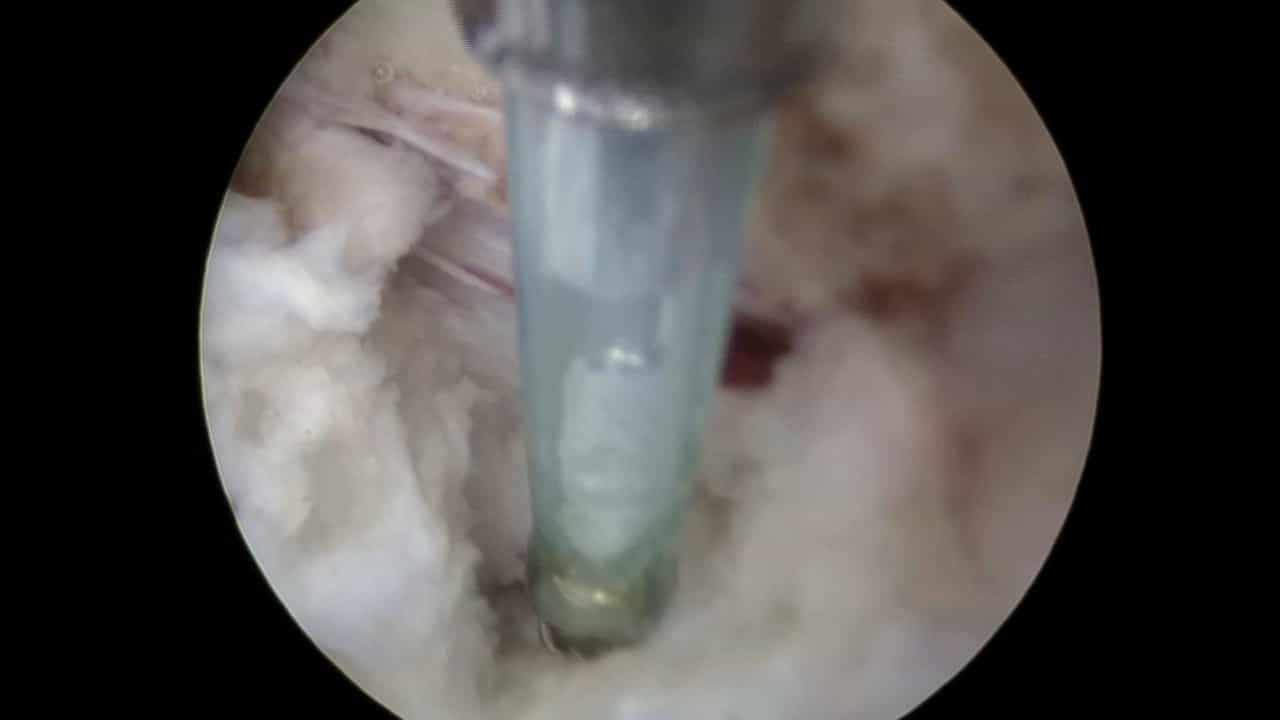

Full-Endoscopic Transforaminal Approach for Lumbar Discectomy
Published on: September 8, 2023
Intracranial, Intra-, and Epidural Pressure Changes During Endoscopic Lumbar Discectomy: A Comparison Between
Alexandra Stauffer1, Jana F Schader1,2,3, Carl M Zipser4
1University Spine Center Zurich, Balgrist University Hospital, Zurich, Switzerland.

Study Design:
Cadaveric laboratory study.
Objectives:
To characterize and compare intracranial, intradural (cervical, thoracic, lumbar), and lumbar epidural pressure changes during transforaminal and interlaminar endoscopic lumbar procedures under gravity and pump irrigation, with and without simulated outflow occlusion.
Summary Of Background Data:
High-pressure irrigation improves visualization and hemostasis during endoscopic lumbar discectomy but may increase spinal canal and intracranial pressures and contribute to neurologic complications if not well controlled.
Methods:
Three fresh-frozen human cadavers were instrumented with pressure probes in the lumbar epidural space (L3-4), intradural space at C5-6, T8-9, and L3-4, and intracranially. At L3-4, transforaminal and interlaminar uniportal approaches were performed using gravity irrigation (50, 100, 130 cmH2O) and two pump systems (30-120 mmHg; arthroscopy pump and spine-certified pump). Each setting was tested with open outflow and with temporary outflow occlusion by blocking the working channel. Pressure readings were recorded as relative increases (Delta mmHg) from baseline.
Results:
Without occlusion, the interlaminar approach produced higher lumbar epidural pressure increases than the transforaminal approach across all irrigation modalities (up to 10 mmHg). Differences at intradural levels and intracranially were small (<5 mmHg). With outflow occlusion, the pressure differential narrowed or reversed, with transforaminal access producing higher lumbar epidural and intradural pressures at higher pump settings. Intracranial pressure differences remained modest, with only small increases under occlusion at higher pump settings.
Conclusions:
Irrigation generates compartment- and approach-specific pressure responses. Interlaminar access shows higher baseline lumbar epidural pressure, whereas transforaminal access is more susceptible to pressure surges during occlusion. Even small intracranial pressure increases may be clinically important in susceptible patients; careful irrigation pressure control and avoidance of prolonged outflow occlusion are recommended.
