Related Experiment Video
Updated: Jun 5, 2026


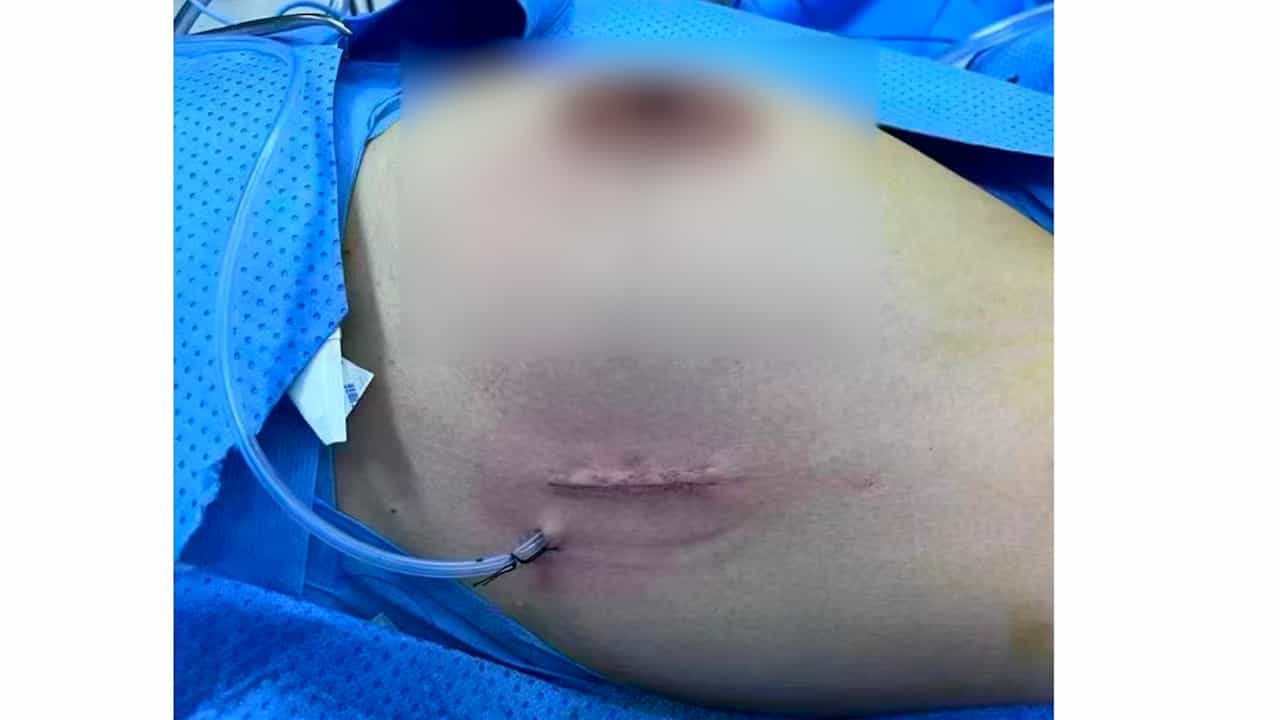
Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Regional Anesthesia as Primary Strategy in Aesthetic Breast Augmentation Surgery: Clinical Outcomes in 627 Sedated
Di Lorenzo Sara1, Andrea Pio Cascino1, Scalisi Alfio2
1Plastic and Reconstructive Surgery, Department of Precision Medicine in Medical, Surgical and Critical Care (Me.Pre.C.C.), University of Palermo, Via del Vespro, 129, 90127, Palermo, Italy.

Background:
Post-operative pain after breast augmentation remains unpredictable, and regional anesthesia alone is seldom described. We evaluated an opioid-free protocol combining pectoral nerves (PECS I-II) and parasternal blocks with intravenous sedation.
Methods:
Between January 2020 and December 2024, 627 women (mean age 35 y) underwent bilateral primary augmentation under ultrasound-guided fascial-plane blocks plus sedation. VAS pain scores were recorded at predefined intervals up to 72 h. Descriptive statistics, cubic modelling of pain trajectories and Kruskal-Wallis tests compared implant planes; cumulative pain was expressed as the 0-72 h area under the curve (AUC).
Results:
Mean VAS was < 2 in all groups by 72 h. Pain peaked at 16 h, highest with dual-plane placement (mean 7.0) and lower with submuscular and pre-pectoral placements (both ≈ 5.5; p < 0.001). Inter-group differences persisted to 48 h but disappeared by 72 h (p = 0.115). AUC confirmed the greatest pain burden for dual-plane (292 VAS·h) versus submuscular (238) and pre-pectoral (200). Implant volume showed only a weak overall correlation with pain (ρ = 0.20) and none within individual planes. No patient required rescue opioids; most resumed normal activities within four days, and no major complications occurred.
Conclusions:
Ultrasound-guided PECS I-II and parasternal blocks with sedation provide safe, effective, opioid-free analgesia for aesthetic breast augmentation. Early pain is determined mainly by the implant plane, not by implant size, and should be considered in surgical planning and postoperative care.
Level Of Evidence Iii:
This journal requires that authors assign a level of evidence to each article. For a full description of these Evidence-Based Medicine ratings, please refer to the Table of Contents or the online Instructions to Authors www.springer.com/00266 .
More Related Videos

Related Concept Videos
 01:16
Local Anesthetics: Clinical Application as Intravenous Regional Anesthesia
One of the advantages of...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:30
Local Anesthetics: Clinical Application as Surface, Infiltration, and Conduction Block Anesthesia
 01:24
General Anesthesia: Overview
General anesthesia induces unconsciousness in the whole body, while the others target specific areas or sensations. It is administered to minimize adverse effects, maintain...
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:13
Local Anesthetics: Pharmacokinetics