Related Experiment Video For Decision framework
Updated: Jun 8, 2026


Computer-Aided Three-Dimensional Visualization in the Treatment of Locally Advanced Thyroid Cancer
Published on: June 9, 2023
Panel-negative strategy for suspected fusion-driven papillary thyroid carcinoma
Yoichiro Okubo1, Ikki Takada2, Mei Kadoya3
1Kanagawa Cancer Center, Department of Pathology, 2-3-2 Nakao, Asahi-ku, Yokohama, Kanagawa, 241-8515, Japan. yoichiro0207@hotmail.com.

Abstract:
Molecular testing in thyroid nodules and papillary thyroid carcinoma (PTC) is not required for every case, but it becomes clinically important when the result may influence diagnostic confidence, surgical planning, including the extent of surgery, or systemic therapy options. Representative scenarios include indeterminate thyroid cytology, clinically advanced or metastatic disease, and recurrent or progressive PTC. In these settings, the key question is not simply whether a common hotspot mutation is present, but whether clinically relevant drivers, including RET and NTRK fusions, have been adequately assessed. Fusion-inclusive molecular testing is preferable when molecular information is required for thyroid nodules or PTC, particularly when the clinical question includes the possibility of a fusion-driven tumor. However, in routine practice, limited or mutation-focused assays, such as BRAF V600E testing or hotspot DNA panels, may already have been performed because of limitations in access, reimbursement, specimen availability, or institutional workflow. Negative results from such assays can be misread as definitive exclusion of clinically relevant fusions, despite pre-analytic constraints and incomplete fusion coverage. This Correspondence does not advocate a hotspot-first workflow, nor does it propose serial add-on testing as a preferred strategy. Rather, we propose a pragmatic "panel-negative" communication and decision-making framework for situations in which limited testing has already been performed and morphologic or clinical suspicion for fusion-driven PTC persists. The approach emphasizes (i) selecting a thyroid-appropriate molecular assay from the outset whenever feasible, (ii) explicitly documenting residual suspicion and the scope of the performed assay in pathology reports, (iii) using pan-TRK immunohistochemistry only as an optional triage tool rather than a rule-out test, and (iv) considering RNA-based or other fusion-optimized assays only when the original clinical question remains unresolved and the result is clinically relevant. This framework is intended to reduce false reassurance from negative limited panels while reinforcing the need for appropriate molecular testing in the correct clinical scenario.
More Related Videos
 07:45
"Sun's Seven-Step Technique" for Endoscopic En-Bloc Resection of Thyroid Cancer via the Chest-Breast Approach
Published on: November 28, 2025
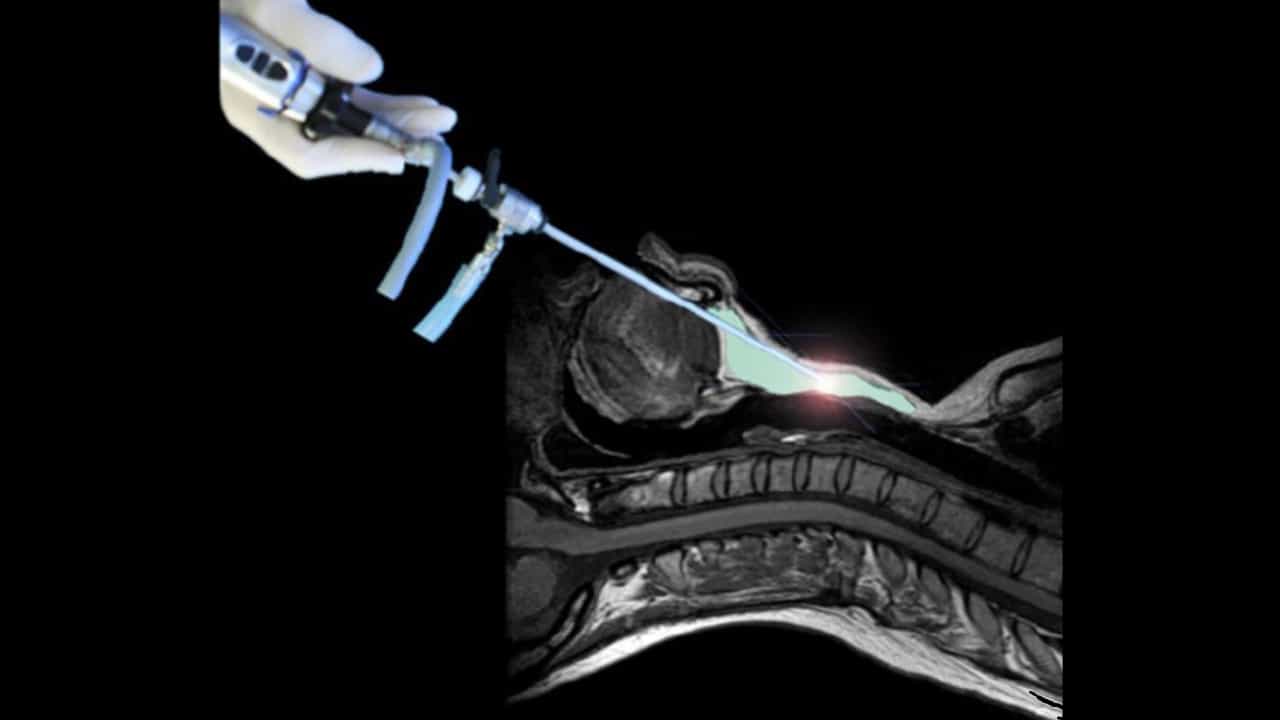 04:01
Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023