Related Experiment Video
Updated: Jun 25, 2026


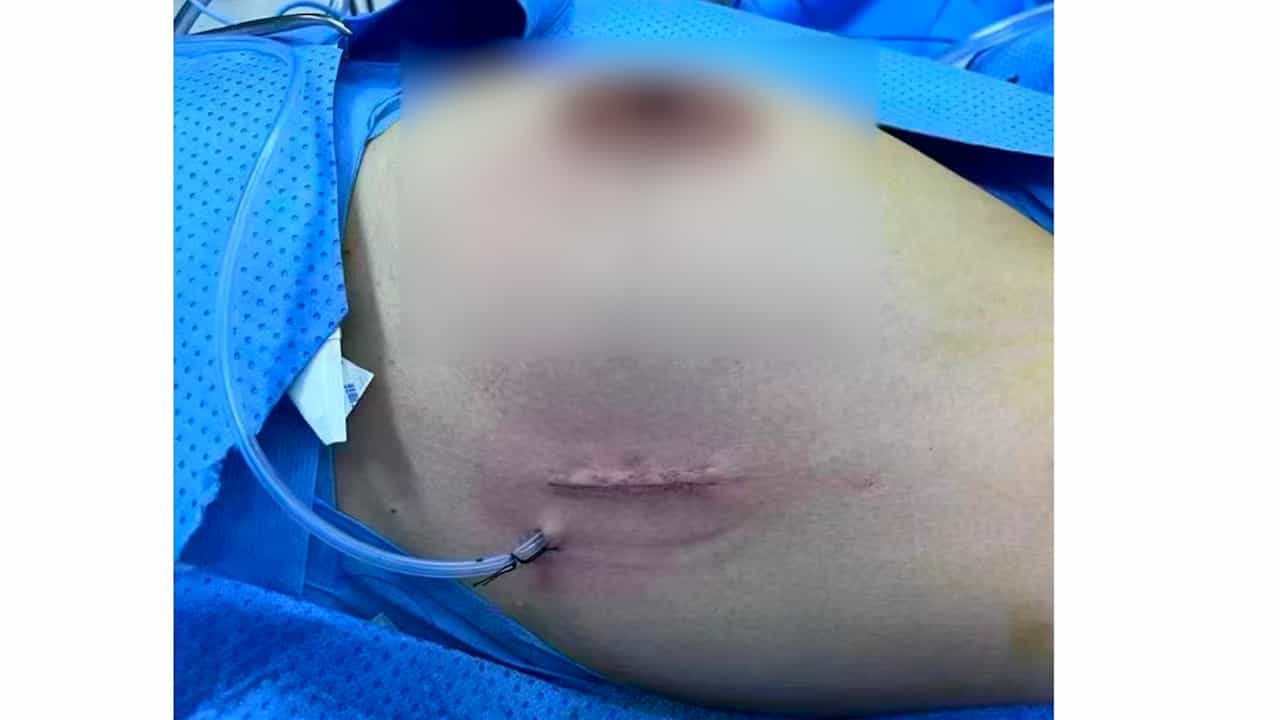
Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Venous Drainage and Nipple-Areolar Complex Necrosis After Nipple-Sparing Mastectomy: A Cadaveric and Prospective

Background:
Nipple-sparing mastectomy (NSM) with immediate implant-based breast reconstruction (IBBR) offers excellent aesthetic outcomes, but nipple-areolar complex (NAC) necrosis remains a major complication. Although arterial insufficiency has been emphasized, venous injury may also play a critical role.
Objectives:
The aim of this study was to characterize NAC venous anatomy and determine whether venous injury contributes to clinically significant NAC necrosis after NSM.
Methods:
The authors performed a cadaveric study of superficial periareolar venous anatomy and a prospective clinical cohort study of 123 breasts undergoing NSM with immediate IBBR. Cutaneous NAC veins were visualized using near-infrared (NIR) imaging, and venous injury was quantified as vein branch loss (VBL). We evaluated predictors of clinically significant NAC necrosis and developed a prediction model compared with intraoperative indocyanine green angiography (ICGA) in 32 breasts.
Results:
Cadaveric dissection demonstrated a polygonal venous network adjacent to the areolar margin. In the clinical cohort, significant NAC necrosis occurred in 19 of 123 breasts (15.4%). On univariate analysis, higher VBL, greater mastectomy weight, higher BMI, and diabetes were associated with NAC necrosis (P < .05). Multivariable analysis demonstrated that the effect of VBL increased with mastectomy weight. The final model showed strong discrimination (area under the receiver operating characteristic 0.902; 95% CI, 0.82-0.98) and identified a low-risk subset among breasts with poor ICGA perfusion in which no significant NAC necrosis occurred.
Conclusions:
Venous integrity is a key determinant of NAC viability after NSM. NIR-based vein analysis enables quantitative assessment of venous injury and may complement ICGA in perioperative risk stratification and surgical planning.
Level Of Evidence: 4 (Risk):
For image description, please refer to the figure legend and surrounding text.