Related Experiment Video
Updated: Jul 1, 2026
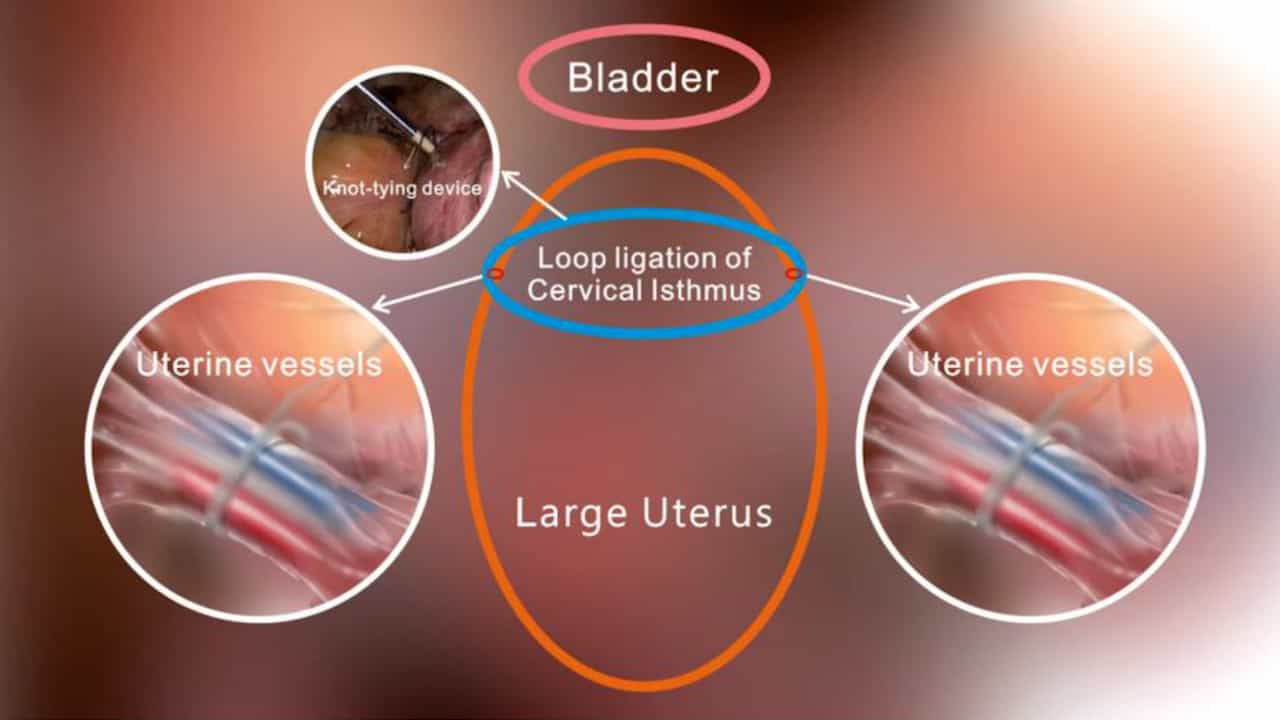

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
[Analysis of posterior uterus approach combined with vascular occlusion in placenta percreta]
1Department of Obstetrics and Gynecology, Xiangya Second Hospital of Central South University, Changsha 410011, China.

Objective: To explore the perinatal outcomes and cost-effectiveness of posterior uterus approach combined with vascular occlusion in placenta percreta (PP). Methods: This study was a retrospective cohort study. Clinical data of 475 pregnant women with PP from six tertiary medical centers in China from January 2018 to April 2023 were collected. After propensity score matching, 324 pregnant women were included and divided into study group (posterior uterus approach combined with vascular occlusion, 162 cases) and control group (abdominal aortic balloon occlusion, 162 cases). The baseline characteristics, maternal and neonatal outcomes [including hysterectomy rate, intraoperative blood loss, blood transfusion rate, length of hospital stay, intensive care unit (ICU) transfer rate] and hospitalization costs were compared between the two groups. Incremental cost-effectiveness ratio (ICER) was used for cost-benefit analysis, and the willingness-to-pay threshold was set at 1 times of gross domestic product per capita in 2023 (CNY 91 700.0). Results: There were no significant differences in baseline characteristics of PP pregnant women between the two groups after matching. The hysterectomy rate (46.9% vs 16.1%), intraoperative blood loss (median: 1 450 vs 800 ml) and blood transfusion rate (77.8% vs 47.5%) in the study group were significantly higher than those in the control group, and the hospital stay was longer (median: 10 vs 7 days). However, the rate of postoperative ICU transfer (3.7% vs 13.6%) and secondary operation (0.0% vs 7.4%) in the study group were significantly lower than those in the control group (all P<0.05). There was no maternal death in the two groups, and there were no statistically significant differences in the incidence of urinary system injury, thrombosis and infection between the two groups (all P>0.05). The rate of neonatal intensive care unit (NICU) admission in the study group was significantly higher than that in the control group (50.6% vs 28.4%, P<0.001). In terms of hospitalization costs, the total hospitalization costs of the study group were significantly lower than those of the control group (median: CNY 29 361.8 vs 35 704.3, P<0.001). Cost-benefit analysis showed that taking non-ICU hospitalization as the effectiveness index, the cost of avoiding one case to be transferred to ICU in the study group was lower than that in the control group (CNY 29 996.5 vs 38 372.8), and the ICER was CNY 84 780.5, which was lower than the willingness-to-pay threshold, and the study group had economic advantages. Conclusions: It is effective for treating PP in posterior uterus approach combined with vascular occlusion. Although it is associated with higher hysterectomy rates and greater blood loss, it is relatively simpler to perform, and results in lower total hospitalization costs. It is suitable for areas with limited medical resources.
Objective: To explore the perinatal outcomes and cost-effectiveness of posterior uterus approach combined with vascular occlusion in placenta percreta (PP). Methods: This study was a retrospective cohort study. Clinical data of 475 pregnant women with PP from six tertiary medical centers in China from January 2018 to April 2023 were collected. After propensity score matching, 324 pregnant women were included and divided into study group (posterior uterus approach combined with vascular occlusion, 162 cases) and control group (abdominal aortic balloon occlusion, 162 cases). The baseline characteristics, maternal and neonatal outcomes [including hysterectomy rate, intraoperative blood loss, blood transfusion rate, length of hospital stay, intensive care unit (ICU) transfer rate] and hospitalization costs were compared between the two groups. Incremental cost-effectiveness ratio (ICER) was used for cost-benefit analysis, and the willingness-to-pay threshold was set at 1 times of gross domestic product per capita in 2023 (CNY 91 700.0). Results: There were no significant differences in baseline characteristics of PP pregnant women between the two groups after matching. The hysterectomy rate (46.9% vs 16.1%), intraoperative blood loss (median: 1 450 vs 800 ml) and blood transfusion rate (77.8% vs 47.5%) in the study group were significantly higher than those in the control group, and the hospital stay was longer (median: 10 vs 7 days). However, the rate of postoperative ICU transfer (3.7% vs 13.6%) and secondary operation (0.0% vs 7.4%) in the study group were significantly lower than those in the control group (all P<0.05). There was no maternal death in the two groups, and there were no statistically significant differences in the incidence of urinary system injury, thrombosis and infection between the two groups (all P>0.05). The rate of neonatal intensive care unit (NICU) admission in the study group was significantly higher than that in the control group (50.6% vs 28.4%, P<0.001). In terms of hospitalization costs, the total hospitalization costs of the study group were significantly lower than those of the control group (median: CNY 29 361.8 vs 35 704.3, P<0.001). Cost-benefit analysis showed that taking non-ICU hospitalization as the effectiveness index, the cost of avoiding one case to be transferred to ICU in the study group was lower than that in the control group (CNY 29 996.5 vs 38 372.8), and the ICER was CNY 84 780.5, which was lower than the willingness-to-pay threshold, and the study group had economic advantages. Conclusions: It is effective for treating PP in posterior uterus approach combined with vascular occlusion. Although it is associated with higher hysterectomy rates and greater blood loss, it is relatively simpler to perform, and results in lower total hospitalization costs. It is suitable for areas with limited medical resources.