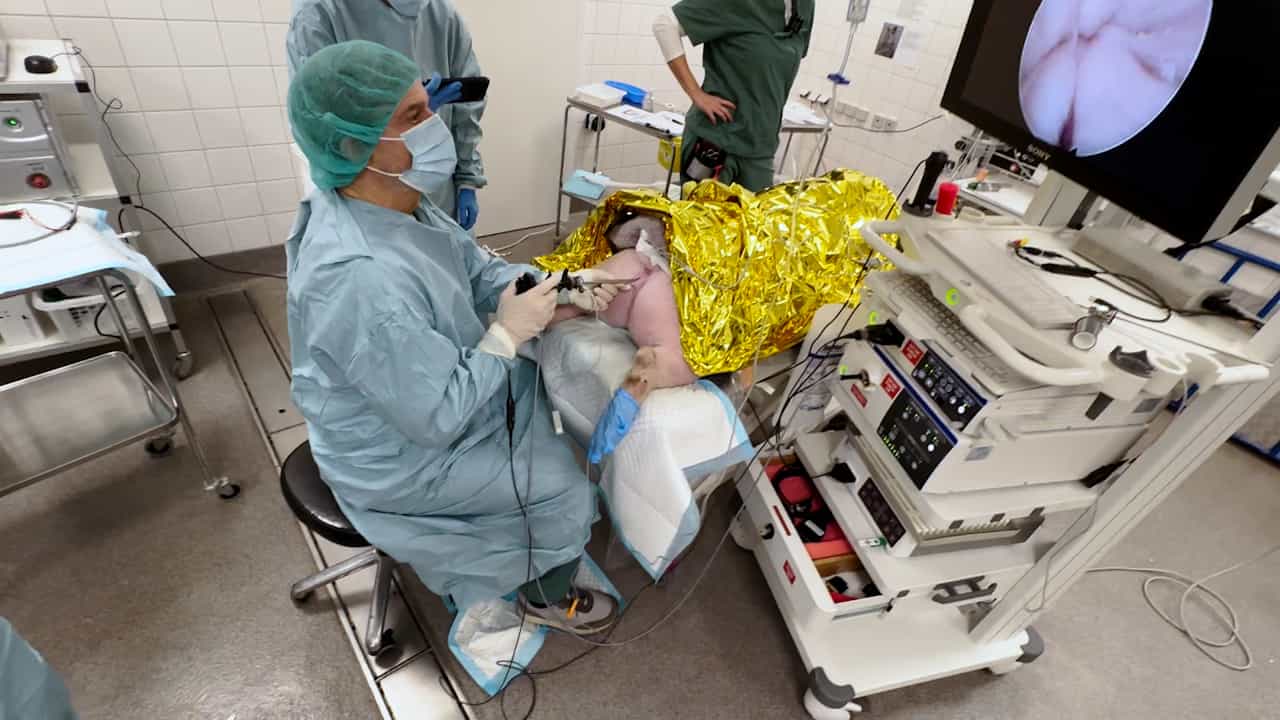
Related Experiment Video
Updated: Jul 12, 2026

Surgical Treatment for Benign Prostatic Hyperplasia: Holmium Laser Enucleation of the Prostate (HoLEP).
Published on: March 6, 2018
High-frequency irreversible electroporation versus transurethral resection of the prostate for benign prostatic
Bi-Ming He1, Rong-Bing Li1, Dong-Yang Li1
1Department of Urology, Shanghai East Hospital, School of Medicine, Tongji University, Shanghai, China.

Background:
Transurethral resection of the prostate (TURP) is the gold standard for treating benign prostatic hyperplasia (BPH) but frequently causes retrograde ejaculation and bleeding. High-frequency irreversible electroporation (H-FIRE) is a non-thermal ablation technique offering tissue selectivity. We aimed to compare the efficacy and safety of H-FIRE versus TURP in men with symptomatic BPH.
Methods:
In this investigator-initiated, single-centre, randomised, double-blind, non-inferiority trial at Shanghai East Hospital, China, men aged 40 years or older with symptomatic BPH (prostate volume 30-100 mL) were assigned (1:1) to undergo H-FIRE or TURP. To maintain blinding, a sham protocol involving perineal dressings and standardised irrigation was used. The co-primary outcomes were change from baseline in maximum urinary flow rate (Qmax) and International Prostate Symptom Score (IPSS) at 3 months. Non-inferiority margins were -4 mL/s for Qmax and 3 points for IPSS. Efficacy was analysed in the intention-to-treat population. This trial is registered with ClinicalTrials.gov, NCT05306145.
Findings:
Between June 30, 2022, and May 25, 2025, 118 participants were enrolled and randomly assigned to H-FIRE (n = 59) or TURP (n = 59). H-FIRE was non-inferior to TURP for both primary endpoints: mean Qmax improvement was 7.95 mL/s with H-FIRE versus 7.84 mL/s with TURP (adjusted difference 0.11 mL/s, 95% CI -2.52 to 2.73; p = 0.001 for non-inferiority); mean IPSS reduction was -13.24 versus -13.75 (adjusted difference 0.50, -1.09 to 2.10; p = 0.001 for non-inferiority). Retrograde ejaculation occurred in 0% (0/59) of patients in the H-FIRE group compared with 54.2% (32/59) in the TURP group (p < 0.0001). H-FIRE was associated with greater haemodynamic stability (mean haemoglobin change +0.82 g/L [95% CI -1.84 to 3.48] versus -12.14 g/L [-14.72 to -9.55]; p < 0.0001) but required longer postoperative catheterisation (median 19 days [IQR 15.0-22.0] versus 4 days [4.0-5.0]). There were no grade 3-4 adverse events, and no deaths occurred in either group.
Interpretation:
At 3 months, H-FIRE provided short-term functional improvement non-inferior to TURP while completely preserving ejaculatory function and minimising blood loss. Although associated with longer temporary catheterisation due to tissue resorption, H-FIRE represents a viable function-sparing alternative for men prioritising sexual health and offers potential for ambulatory management.
Funding:
National Natural Science Foundation of China (No. 82373048) and National Natural Science Foundation of China for Youth (No. 82303612).