Related Experiment Video
Updated: Aug 6, 2026
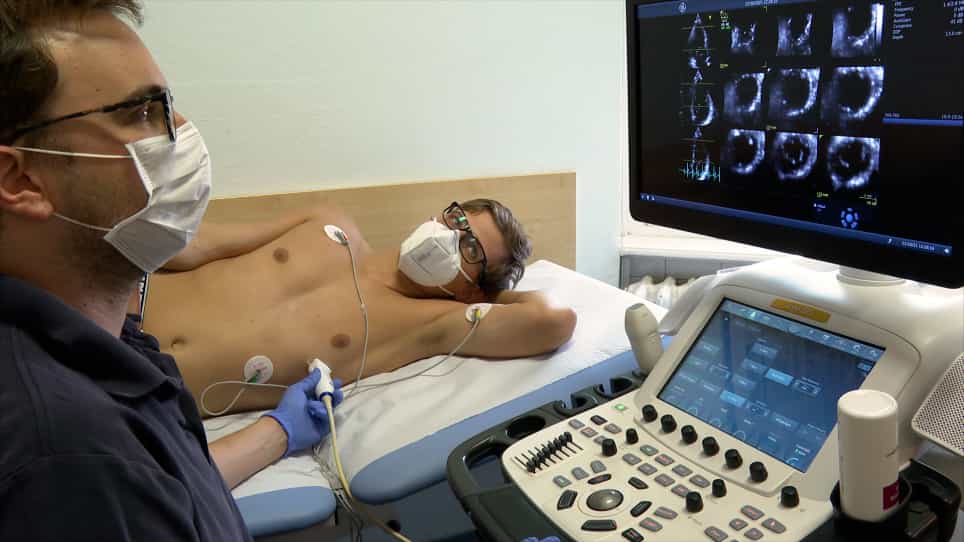

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
Electromechanical Profiling in Genotyped Dilated Cardiomyopathy with Left Bundle Branch Block
Thomas Van Overmeiren1, Lorenzo Bianchi2,3, Max F G H M Venner2,3
1Department of Cardiology, Ghent University Hospital, Ghent, Belgium.

Insights
Genetic testing in dilated cardiomyopathy (DCM) with left bundle branch block (LBBB) has low yield. Genotype-positive patients show distinct electromechanical profiles, poor cardiac resynchronization therapy (CRT) response, and worse outcomes.
Area of Science:
- Cardiology
- Genetics
- Electrophysiology
Background:
- Dilated cardiomyopathy (DCM) management often includes genetic testing.
- Left bundle branch block (LBBB) in DCM patients presents unique diagnostic and therapeutic challenges.
- The interplay between genetic variants, LBBB characteristics, and treatment response in DCM is not fully understood.
Purpose of the Study:
- To investigate the prevalence and impact of pathogenic/likely pathogenic (P/LP) variants in DCM patients with LBBB.
- To analyze the electromechanical profile of genotyped DCM patients with LBBB.
- To determine the relationship between genetic status, electromechanical parameters, cardiac resynchronization therapy (CRT) response, and clinical outcomes.
Main Methods:
- A multicenter cohort of 347 DCM patients with LBBB undergoing genetic testing was analyzed.
- Comprehensive electro- and echocardiographic phenotyping, including speckle-tracking strain analysis, was performed.
- CRT response was assessed by changes in end-systolic volume (ESV) and left ventricular ejection fraction (LVEF).
Main Results:
- Only 6% of DCM patients with LBBB carried P/LP variants.
- Genotype-positive patients displayed atypical LBBB features and reduced mechanical dyssynchrony.
- These patients showed poorer CRT response and worse clinical outcomes (mortality, heart failure hospitalization).
Conclusions:
- Genetic testing has limited diagnostic utility in DCM patients with LBBB.
- A distinct electromechanical profile in genotype-positive DCM with LBBB is associated with suboptimal CRT response and adverse prognosis.
- Combined genetic and electromechanical phenotyping may enhance risk stratification and personalized treatment strategies.
Aims:
Genetic testing is routinely recommended in dilated cardiomyopathy (DCM), yet the prevalence and implications of pathogenic/likely pathogenic (P/LP) variants in patients with DCM and left bundle branch block (LBBB) remain unclear. We therefore investigated the electromechanical profile of genotyped patients with DCM and LBBB, and its relationship with cardiac resynchronization therapy (CRT) response and clinical outcomes.
Methods:
Patients with LBBB were selected from a multicenter cohort of 1206 consecutive DCM patients undergoing genetic testing. All underwent sequencing of 20 clinically validated DCM-related genes (ClinGen) and comprehensive electro- and echocardiographic phenotyping, including speckle-tracking strain analysis, categorizing septal strain curves into five stages (LBBB-0 to LBBB-4). CRT response was assessed as end-systolic volume (ESV) reduction and left ventricular ejection fraction (LVEF) improvement. The clinical endpoints were a composite of all-cause mortality, heart transplantation/left ventricular assist device implantation, and heart failure hospitalization (HFH).
Results:
Among 347 DCM patients with LBBB (median age 60[53-68], median LVEF 31%[23-39]), 22 (6%) exhibited P/LP variants. Genotype-positive patients less frequently fulfilled strict LBBB criteria (Strauss:P<0.001) and exhibited less mechanical dyssynchrony (predominantly LBBB-0/1;P<0.001). They showed attenuated reverse remodeling after CRT (ΔLVEF 1%[-6-6] vs. 14%[7-22];P<0.001) and worse clinical outcomes (both composite outcome and HFH;P<0.001). Conversely, advanced LBBB stages excluded an underlying rare genetic variant. P/LP variant status, LVEF, and LBBB stage independently predicted CRT response and composite outcome.
Conclusions:
Genetic testing has a low diagnostic yield in patients with DCM and LBBB. Genotype-positive variants exhibit a distinct electromechanical profile, characterised by atypical electrocardiographic features and markedly reduced mechanical dyssynchrony, poor CRT response, and worse long-term outcomes. Integrating genetic and electromechanical phenotyping may improve individualized risk stratification and management.


