Related Experiment Video
Updated: Sep 4, 2026
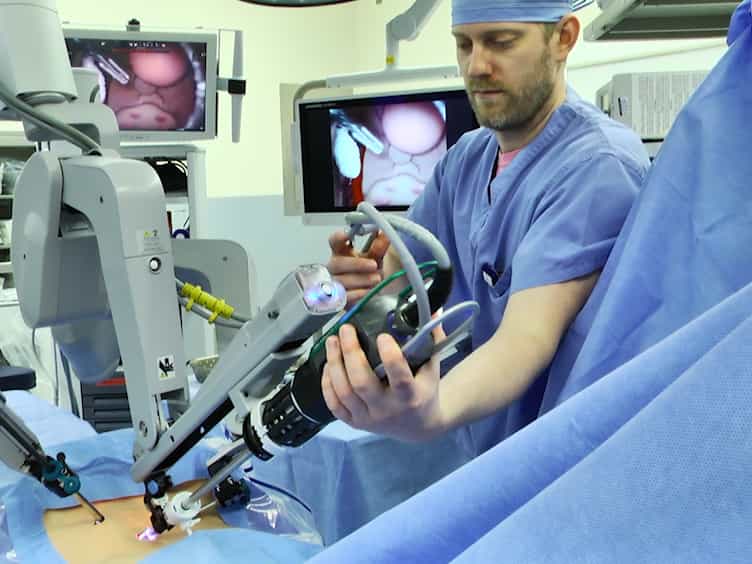

Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Pelvic Stability in Pediatric Trauma: A Gamified Simulation for the Deliberate Practice of Pelvic Sheet Binding
Devin J Shah1, Branae Rollins2, Néhémie P Jules3
1Division of General Pediatric Surgery, Department of Surgery, Children's Hospital Los Angeles, Los Angeles, California; Las Madrinas Simulation Center, Children's Hospital Los Angeles, Los Angeles, California.

Objective:
To evaluate the feasibility and impact of a gamified, low-fidelity simulation activity for pediatric pelvic sheet binding, focused on improving trainee procedural speed, technical proficiency, and self-efficacy through deliberate practice and mastery learning.
Design:
This was a prospective educational pilot study utilizing a pretest/posttest design and a low-fidelity simulation mannequin with haptic feedback. The intervention was developed using Kern's 6-Step Framework and designed to address American Board of Surgery (ABS) Entrustable Professional Activities (EPAs). The activity followed a structured progression to track performance across assessment phases and 2 successive attempts separated by a structured educational session (debriefing with focused feedback, video demonstration, and live demonstration) to evaluate short-term skill acquisition.
Setting:
The study was conducted at a quaternary academic children's hospital during a protected surgical education block in the 2025 to 2026 academic year.
Participants:
A convenience sample of 8 surgical trainees and medical students (PGY2-PGY10 and MS3) participated. Seven completed the presurvey and 6 completed the postsurvey. Participation was voluntary across all stages.
Results:
Time to successful binder application significantly decreased from an average of 239 seconds to 102 seconds (p = 0.012). Technique quality remained high for positioning of the binder around the greater trochanter, maintenance of full spine precautions using the log roll technique, and utilization of clamps to secure the binder. Participant confidence significantly improved from an average of 2.2 to 3.8 on a 5-point Likert scale (p = 0.026), with 83.3% feeling "moderately confident" following the simulation compared to 14.3% at baseline.
Conclusions:
A gamified, low-fidelity simulation using haptic feedback is a feasible and effective method for teaching the rare but critical skill of pediatric pelvic sheet binding. The curriculum successfully utilized deliberate practice to enhance procedural speed and trainee confidence without compromising technical accuracy. This model provides a reproducible framework for addressing core entrustable professional activities in pediatric trauma education.