Related Experiment Video
Updated: Sep 4, 2026
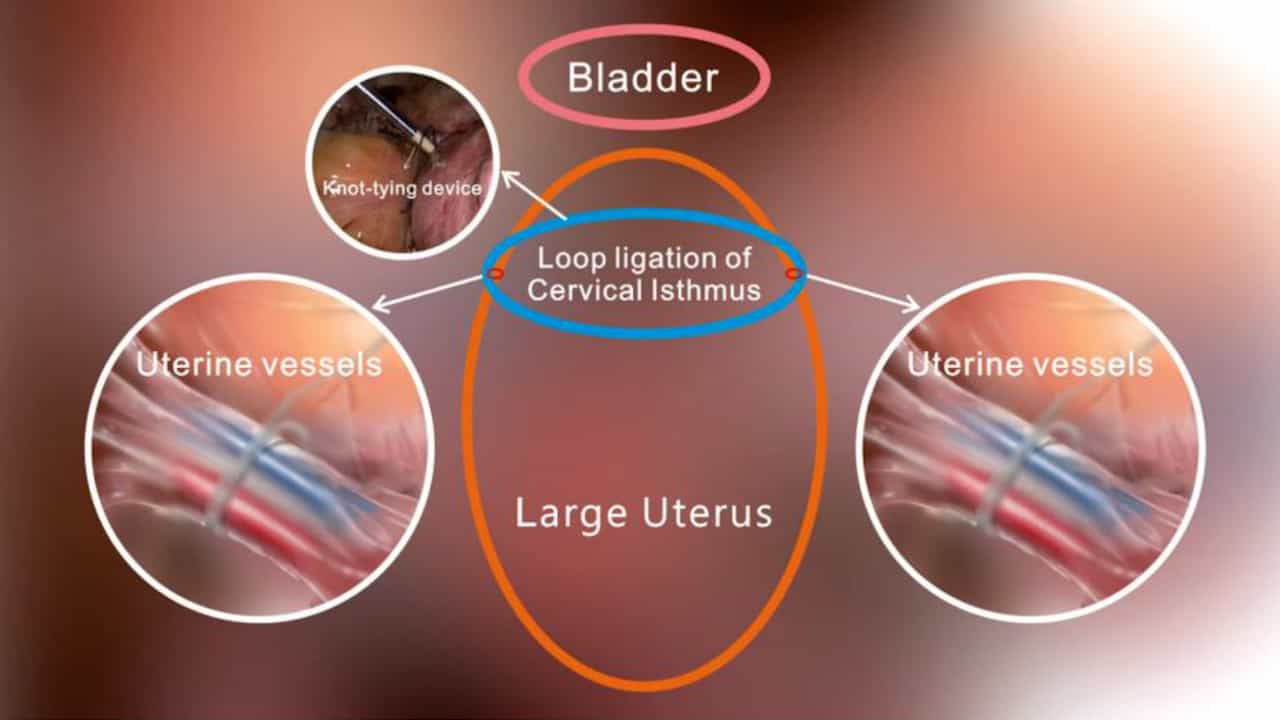
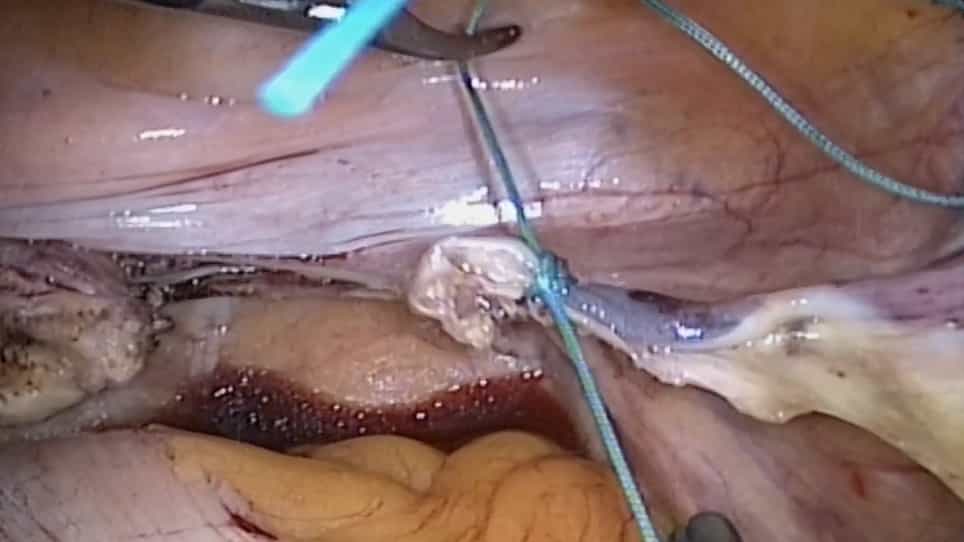
Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Ultrasound-indicated cerclage as a critical decision window in cervical insufficiency: a mini review of
Yong-Jin Park1, Moon-Il Park1,2
1Department of Obstetrics and Gynecology, Dongtan Jeil Women's Hospital, Hwaseong, Republic of Korea.

Ultrasound-indicated cerclage occupies an intermediate position between history-based prophylaxis and emergency or physical examination-indicated cerclage. Current guidelines generally define this intervention by obstetric history and cervical-length thresholds, but these categorical criteria do not fully capture the time-dependent nature of cervical insufficiency. This focused Mini Review synthesizes international guidelines, randomized and meta-analytic evidence, and recent observational studies to examine ultrasound-indicated cerclage as a critical decision window within a dynamic process of cervical remodeling and progressive structural failure. In this framework, sonographic cervical shortening represents a transitional phase in which risk has become clinically visible but may still remain modifiable. Evidence most consistently supports cerclage in selected high-risk singleton pregnancies with prior spontaneous preterm birth or mid-trimester loss and current cervical shortening, whereas benefit is less certain in low-risk populations with an incidentally detected short cervix or after progression to membrane exposure or advanced dilation. Interpretation is limited by heterogeneity in patient selection, cervical state, timing of intervention, and reporting of operative variables. Reframing ultrasound-indicated cerclage as a time-dependent decision window may help explain heterogeneous findings, improve interpretation of guideline differences, and support more precise patient selection. Future studies should report cervical-length trajectory, gestational timing, cervical phenotype, membrane relationship, inflammatory context, and transition to emergency operative states.
Ultrasound-indicated cerclage occupies an intermediate position between history-based prophylaxis and emergency or physical examination-indicated cerclage. Current guidelines generally define this intervention by obstetric history and cervical-length thresholds, but these categorical criteria do not fully capture the time-dependent nature of cervical insufficiency. This focused Mini Review synthesizes international guidelines, randomized and meta-analytic evidence, and recent observational studies to examine ultrasound-indicated cerclage as a critical decision window within a dynamic process of cervical remodeling and progressive structural failure. In this framework, sonographic cervical shortening represents a transitional phase in which risk has become clinically visible but may still remain modifiable. Evidence most consistently supports cerclage in selected high-risk singleton pregnancies with prior spontaneous preterm birth or mid-trimester loss and current cervical shortening, whereas benefit is less certain in low-risk populations with an incidentally detected short cervix or after progression to membrane exposure or advanced dilation. Interpretation is limited by heterogeneity in patient selection, cervical state, timing of intervention, and reporting of operative variables. Reframing ultrasound-indicated cerclage as a time-dependent decision window may help explain heterogeneous findings, improve interpretation of guideline differences, and support more precise patient selection. Future studies should report cervical-length trajectory, gestational timing, cervical phenotype, membrane relationship, inflammatory context, and transition to emergency operative states.