Related Experiment Video
Updated: Sep 24, 2026


A Method to Test the Efficacy of Handwashing for the Removal of Emerging Infectious Pathogens
Published on: June 7, 2017
Adherence to basic hygiene routines in an infectious disease setting: associations with knowledge and professional
Greta Nykvist1, Moa Nilsson2, Katarina Bohm3
1Department of Infectious Diseases, Karolinska University Hospital, Stockholm, Sweden.

Introduction:
Healthcare-associated infections (HAIs) are a major global health concern, leading to increased morbidity, mortality, healthcare costs, and prolonged hospital stays. Adherence to basic hygiene routines is a key preventive measure, yet adherence varies among healthcare professionals.
Objective:
To examine adherence to basic hygiene routines among healthcare professionals in an infectious disease clinic and to explore how knowledge, profession, and work-environment factors influence adherence.
Methods:
A cross-sectional study using a quantitative observational and questionnaire-based design was conducted at an infectious disease clinic in Sweden. A total of 69 healthcare professionals (assistant nurses, registered nurses, and physicians) were recruited through convenience sampling. Data were collected over a four-week period through structured observations, a knowledge test, and a self-assessment questionnaire. The observations were conducted during day and evening shifts using a structured observation protocol. Statistical analyses included descriptive statistics, ANOVA, non-parametric tests, and correlation analyses.
Results:
The overall observed adherence to basic hygiene routines was 76.4% (±20.2). Registered nurses demonstrated significantly higher adherence than physicians. Self-assessed adherence was higher (92.1% ± 3.3), indicating a discrepancy between perceived and observed behavior. Knowledge levels were generally high (median 90.9%, IQR 81.8-97.7), with registered nurses scoring significantly higher than other professions. No significant correlation was found between knowledge and observed adherence. Perceptions of the impact of the work environment factors on hand hygiene varied, with substantial proportions reporting both agreement and disagreement.
Conclusion:
Although healthcare professionals demonstrated good knowledge and generally positive self-assessed adherence, observed adherence to hygiene routines was suboptimal and varied between professions. The lack of correlation between knowledge and adherence suggests that factors beyond knowledge, such as organizational culture and behavioral aspects, are critical. Targeted interventions focusing on behavioral change, feedback, and interprofessional collaboration are needed to improve adherence and reduce HAIs.
More Related Videos


Related Concept Videos
 01:20
Infection
The chain begins with pathogens: bacteria, viruses, fungi, prions, or parasites such as protozoa helminths. These can be present on the skin as transient or resident flora, or they can be acquired from the environment. Identifying and treating the type of infection and...
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:23
Hand hygiene
Hand washing...
 01:26
Standard Precaution
Hand hygiene is the most crucial means to prevent the transmission of disease. Employers are legally required to provide their workers with personal protective equipment (PPE) to minimize exposure or contact with...
 01:19
Handwashing II: Pre-procedure and Initial Procedure Steps
The hand washing procedure itself includes the following steps. First, cover cuts, if any, on hands with a waterproof dressing. Cuts and abrasions can become contaminated with bacteria hindering the ability to clean the area thoroughly. In addition, repeated hand washing can worsen an injury. The nails must be short and clean, without nail paint...
 01:15
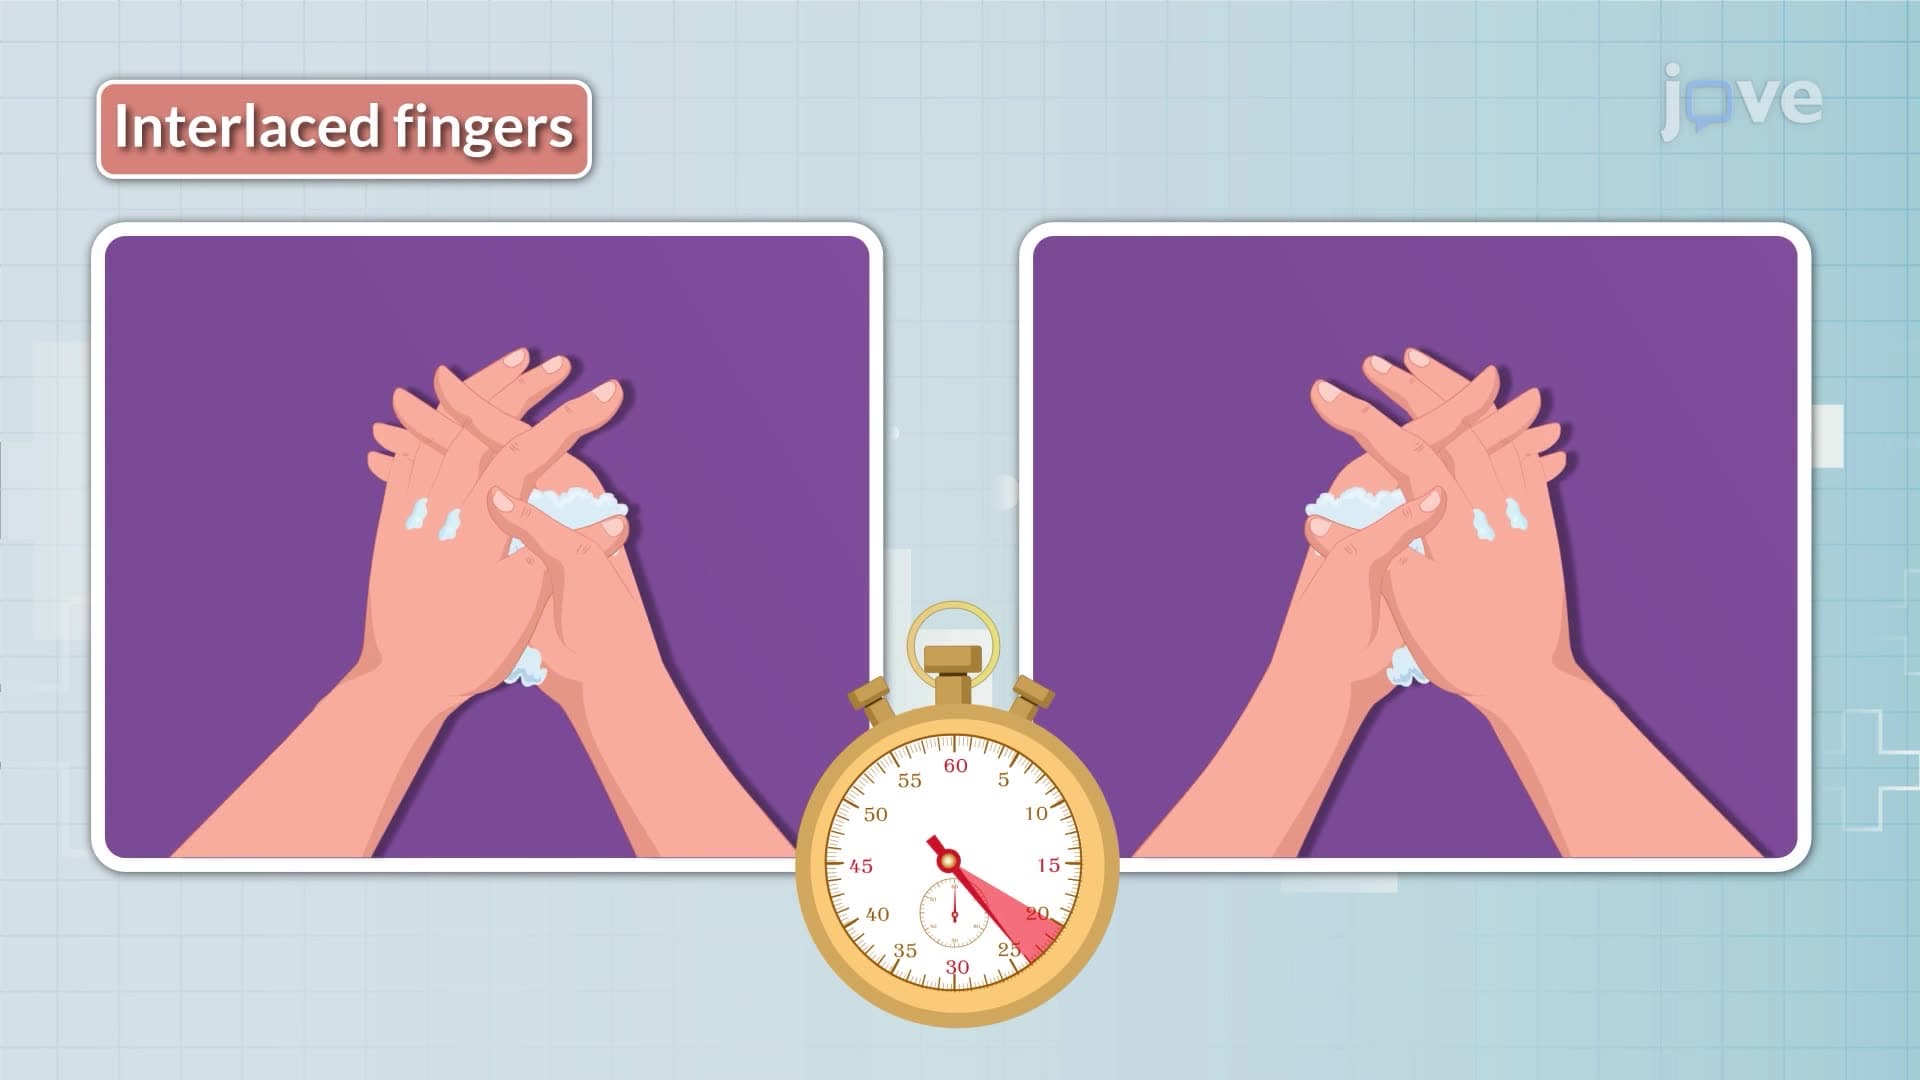
Handwashing III: During the Procedure and Post-Procedure Steps