Related Experiment Video
Updated: Sep 27, 2026
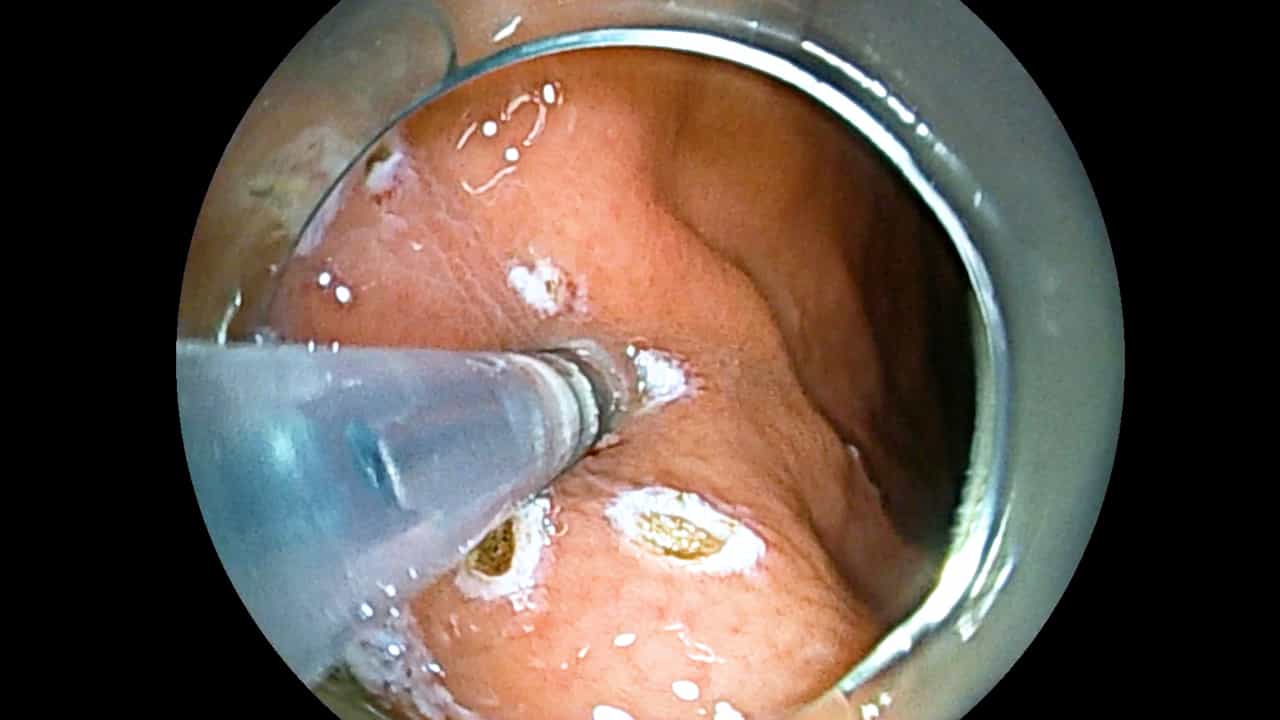

Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Cameron Lesions: Endoscopic Characteristics, Clinical Profile, and Therapeutic Implications-A Retrospective Study of
Viorel Istrate1, Alex-Claudiu Moraru2,3, Sergiu Ungureanu1
1Faculty of Medicine, Nicolae Testemițanu State University of Medicine and Pharmacy, MD-2004 Chisinau, Moldova.

Abstract:
Background and Objectives: Cameron lesions are linear gastric erosions or ulcers that develop at the level of the diaphragmatic constriction within a hiatal hernia. They represent an underrecognized cause of chronic iron-deficiency anemia and upper gastrointestinal bleeding. This study aimed to characterize the demographic, clinical, endoscopic, and therapeutic features of Cameron lesions diagnosed at a tertiary referral digestive endoscopy center in the Republic of Moldova. Methods: This was a retrospective single-center study from Republic of Moldova conducted over a 9-year period (2017-2026). Forty-three consecutive patients with endoscopically confirmed Cameron lesions were included. All examinations were performed by a single experienced endoscopist using high-definition endoscopy systems (Olympus EVIS Exera III and Olympus EVIS X1). Demographic characteristics, hiatal hernia type and size, clinical presentation, endoscopic findings, bleeding stigmata, Helicobacter pylori status, and postoperative outcomes were analyzed. Results: The mean age of the patients was 60.4 years (range, 31-83 years), with a female predominance (65.1%; 28 women and 15 men). The distribution of hiatal hernia types was as follows: type I (axial/sliding), 32.6% (n = 14); type II (paraesophageal/rolling), 34.8% (n = 15); and type III (mixed), 32.6% (n = 14). Cameron lesions developed after failed fundoplication in three patients (6.9%) and were identified in fixed (39.5%), completely reducible (16.3%), and partially reducible (mixed) hernias (44.2%). The main indications for upper gastrointestinal endoscopy were GERD symptoms (53.4%), iron-deficiency anemia (20.9%), prophylactic or postoperative surveillance (18.6%), and overt upper gastrointestinal bleeding (7.0%). Active Cameron lesions were identified in 55.8% of patients, whereas cicatricial and mixed lesions accounted for 30.2% and 13.9%, respectively. Bleeding stigmata were classified according to Forrest as Ia (2.3%), Ib (18.6%), IIa (4.65%), IIb (11.6%), IIc (7.0%), and III (55.81%). Nine patients (20.9%) were identified with active bleeding. Importantly, Cameron lesions were also identified in small hiatal hernias (<3 cm) and in patients with recurrent hiatal hernia after failed fundoplication. Helicobacter pylori infection was detected in 25.6% (n = 11) of patients. Conclusions: This study confirms the well-established association between Cameron lesions, female sex, hiatal hernias, and gastrointestinal bleeding while providing several novel observations, including their occurrence in small hiatal hernias, diagnosis in relatively young adults, and recurrence following failed fundoplication. The findings also highlight the potential contribution of the reducible component of hiatal hernias to lesion development and emphasize the importance of meticulous inspection of the hernia sac during every upper gastrointestinal endoscopic examination.
