Related Experiment Video
Updated: Sep 27, 2026


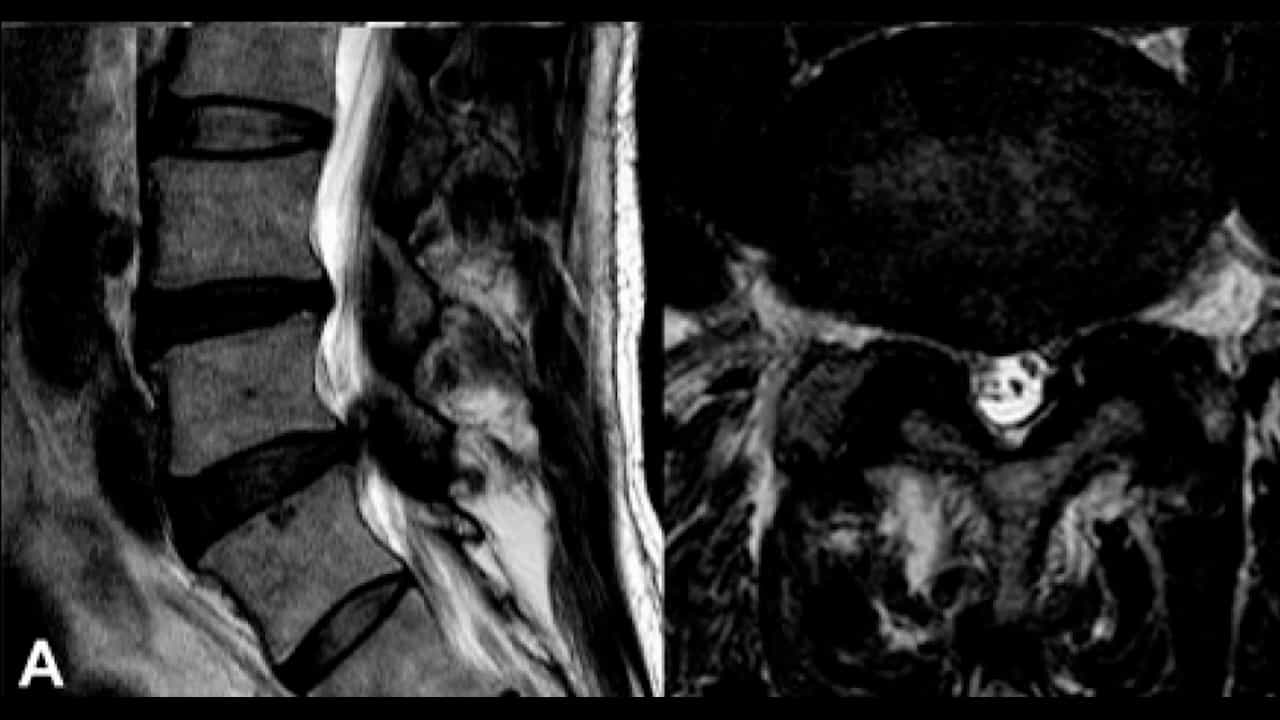
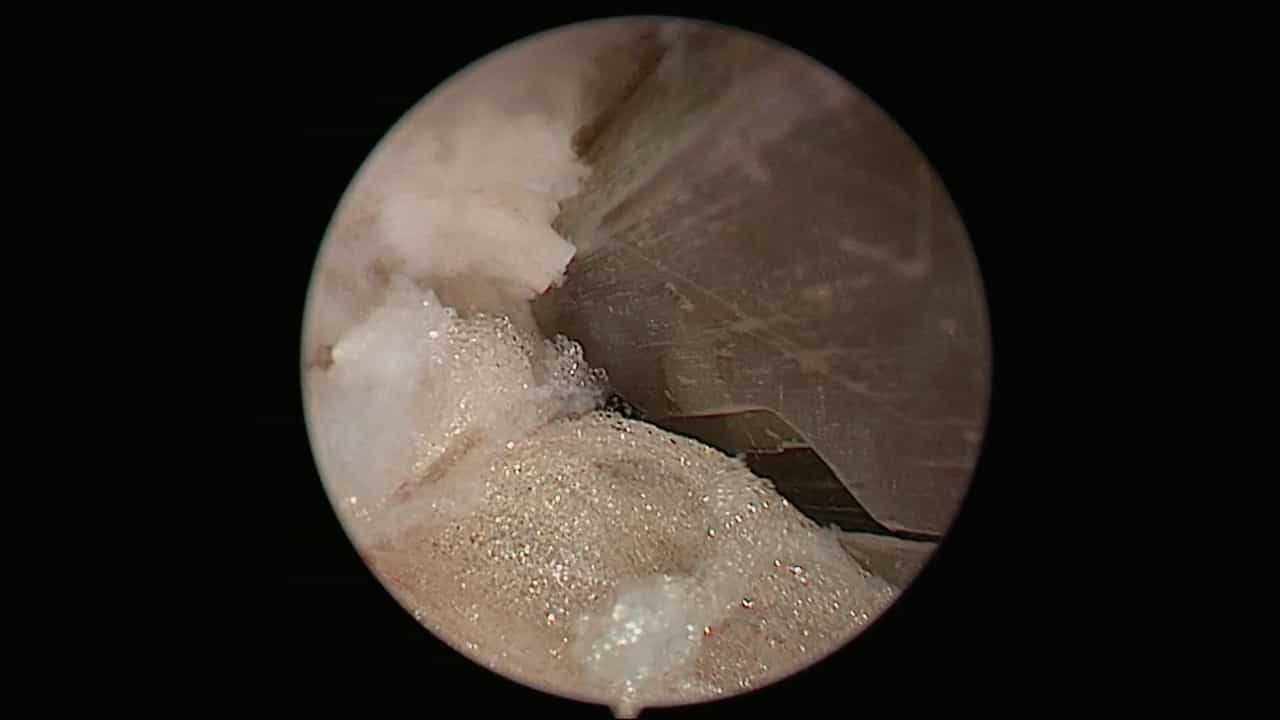
Percutaneous Endoscopic Unilateral-Approach Bilateral Decompression for Lumbar Spinal Stenosis
Published on: February 9, 2024
Full-Endoscopic Unilateral Laminotomy for Bilateral Decompression Under Surgeon-Directed Local Anesthesia in Older
Yong Ahn1, Sungsoo Bae1, Jae-Ouk Lee1
1Department of Neurosurgery, Kyung Hee University Hospital at Gangdong, Kyung Hee University College of Medicine, Seoul 05278, Republic of Korea.

Abstract:
Background and Objectives: Older patients with lumbar spinal stenosis often have comorbidities and limited physiological reserve that complicate conventional decompression under general anesthesia. This study aimed to evaluate the surgical technique and preliminary 1-year clinical outcomes of full-endoscopic unilateral laminotomy for bilateral decompression (FE-ULBD) performed under surgeon-directed local anesthesia. Materials and Methods: This retrospective cohort study included 24 consecutive patients aged ≥ 75 years who underwent FE-ULBD under surgeon-directed local anesthesia for symptomatic central lumbar spinal stenosis between March 2024 and April 2025. Clinical outcomes were evaluated using the visual analog scale (VAS) for leg pain, Oswestry Disability Index (ODI), and modified MacNab criteria. Additionally, perioperative outcomes and complications were analyzed. Results: The mean age of patients was 80.5 ± 3.8 years. The mean VAS scores improved from 8.46 ± 0.72 preoperatively to 2.08 ± 0.83 at 12 months, while ODI scores improved from 68.83% ± 8.07% to 18.34% ± 13.74% (both p < 0.001). Of the 24 patients, 21 (87.5%) achieved excellent or good outcomes. Procedure-related complications included an incidental dural tear in one patient (4.2%) and transient postoperative dysesthesia in 4 patients (16.7%). No major anesthesia-related complications or revision surgeries were observed. Conclusions: FE-ULBD under surgeon-directed local anesthesia was feasible and associated with improvements in pain and function at 12 months in carefully selected older patients. These preliminary findings warrant confirmation in larger prospective studies with a comparator cohort of older patients receiving general anesthesia.