Related Experiment Video
Updated: Sep 28, 2026
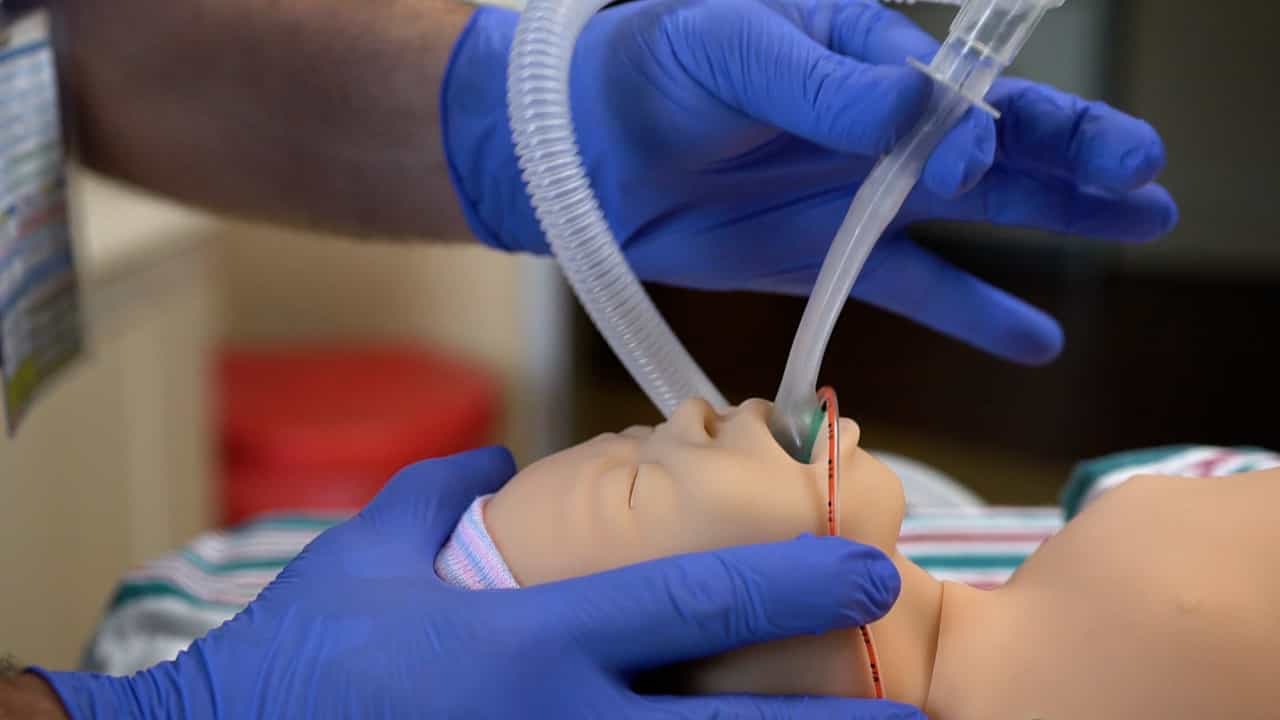

Laryngeal Mask Airway (LMA) Placement in a Neonatal Patient Simulator Using a Non-Inflatable Supraglottic Airway (SGA)
Published on: July 14, 2023
Impact of SGA, AGA, and LGA birthweight subclassification on NICU mortality risk identification: a cohort study
A Nicole Ferguson1, Joseph R Stanton1, Brandi D Jones1
1School of Data Science and Analytics, Kennesaw State University, Kennesaw, GA, USA.

Objective:
To assess whether subdividing small (SGA, <10th), appropriate (AGA, 10th-90th), and large (LGA, >90th percentile) for gestational age (GA) birthweight classifications improves mortality risk estimation among preterm infants in neonatal intensive care units (NICUs).
Study Design:
Data from 25,779 singleton inborn NICU infants (24-30 weeks GA) from the Pediatrix Clinical Data Warehouse (2013-2018) were analyzed. Infant birthweights were subclassified into 12 subgroups (extremely SGA [eSGA], <3rd; moderately SGA [mSGA], 3rd-<10th, 8 AGA categories [3-AGA to 9-AGA]; mLGA, >90th-97th; eLGA, >97th percentile). Mortality probability by birthweight category was modeled using logistic regression.
Result:
Mortality probability was higher for infants classified as eSGA (28.9%, 95% CI [26.4-31.4%]) than mSGA (9.9% [8.7-11.3%]). Smaller AGA infants had higher mortality than larger AGA infants (e.g., 3-AGA: 8.5% [7.5-9.7%] vs. 9-AGA: 5.0% [4.2-5.9%]). Subdividing LGA provided no additional information.
Conclusion:
Subdivision of SGA and AGA birthweight categories may improve mortality risk prediction among premature infants.