Related Experiment Video
Updated: Oct 10, 2026


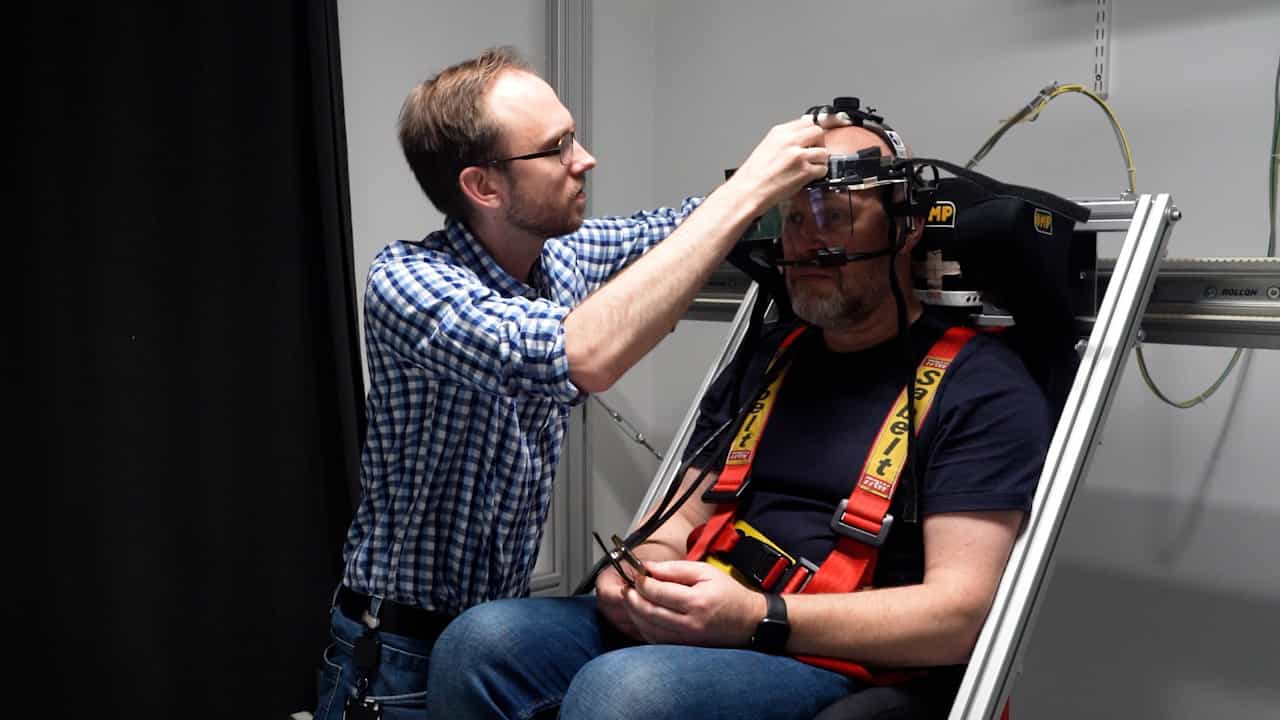
Estimating Vestibular Perceptual Thresholds Using a Six-Degree-Of-Freedom Motion Platform
Published on: August 4, 2022
Data-driven vestibular fMRI in PPPD and residual dizziness after BPPV: a narrative methodological review of AI-based
Bingxing Yang1,2, Liqiong Zhou2, Siqi Wang1,2
1Department of Graduate and Scientific Research, Zunyi Medical University Zhuhai Campus, Zhuhai, Guangdong, China.

Abstract:
Neuroimaging studies of vertigo and chronic dizziness have identified abnormalities across vestibular, visual, somatosensory, and cognitive-emotional networks, but conventional group-level analyses are limited in capturing individual heterogeneity and longitudinal change. This narrative methodological review integrates current evidence and proposes a framework combining functional magnetic resonance imaging (fMRI), artificial intelligence (AI), and advanced statistical modeling, anchored in two priority research scenarios: PPPD phenotyping and longitudinal characterization of residual dizziness after BPPV repositioning. AI, particularly unsupervised learning, may help identify candidate network subtypes from high-dimensional fMRI features, whereas mixed-effects, nonlinear, and latent trajectory models can evaluate their longitudinal stability, clinical relevance, and temporal evolution. Together, these approaches form a complementary pattern-discovery-longitudinal-validation framework. Current evidence, however, remains limited by small samples, single-center designs, technical heterogeneity, and scarce external validation. Accordingly, candidate PPPD subgroups and proposed recovery trajectories after BPPV repositioning should be regarded as hypothesis-generating rather than established fMRI phenotypes. The framework is therefore intended primarily as a research methodology for mechanistic investigation, candidate biomarker discovery, and prospective validation rather than as a clinically deployable decision tool. Future progress will require larger multicenter cohorts, harmonized acquisition and preprocessing, rigorous control of confounding and multiple testing, independent validation, and demonstration of incremental value beyond established clinical assessment.