The Waitlist Paradox: Center Volume, Offer Acceptance, and Pseudo-Access to Liver Transplantation
Related Experiment Video
Updated: Oct 31, 2026
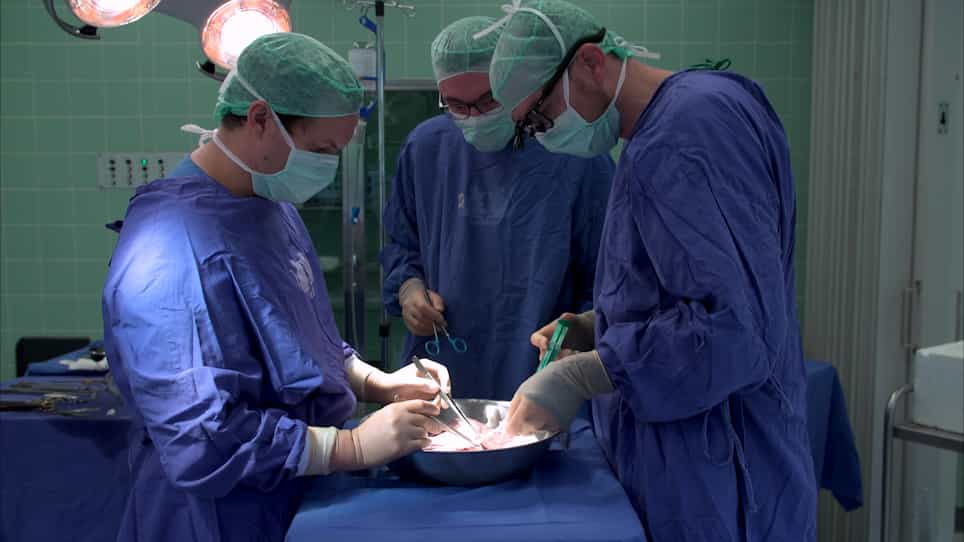
Porcine Liver Transplantation Without Veno-Venous Bypass As an Extended Criteria Donor Model
Published on: August 17, 2022
Qaidar Alizai1, Miho Akabane1, Lorenza Arena1
1Department of Surgery, The Ohio State University Wexner Medical Center and James Comprehensive Cancer Center, Columbus, OH.

Background:
Access to liver transplantation and post-transplant outcomes may vary across centers. We examined the association between center volume and waitlist outcomes among U.S. liver transplant programs.
Methods:
Adult liver transplant programs were identified using Scientific Registry of Transplant Recipients program-specific reports and stratified into quartiles by deceased donor liver transplant (DDLT) volume. Metrics compared across quartiles included deceased-donor transplant rate ratio (DDTR ratio), time-to-transplant ratio, modeled offer acceptance ratio (OAR), waitlist outcomes, graft survival hazard ratios (HRs) and were reported as median and interquartile ranges (IQR).
Results:
DDLT volume increased from Q1 to Q4 (10 [1-33] vs 315 [267-357]; p<0.001). Low-volume centers had lower DDTR ratio (0.35 [0.25-0.82] vs 1.36 [1.02-2.01]; p<0.001) and higher time-to-transplant ratios (1.69 [0.79-2.83] vs 0.82 [0.54-1.34]; p=0.043), while observed waitlist death rates were similar. Overall, OAR increased with volume (Q1 0.51 [0.31-1.05] vs Q4 1.20 [1.13-1.56]), including for PHS high-risk offers, hard-to-place offers, and donors >500 miles away (all p<0.001). Low-volume centers had lower deceased-donor waitlist transplant proportions (31.45% [20.00-41.23] vs 53.62% [46.46-59.86]) and overall waitlist transplant proportions (32.52% [20.50-44.35] vs 55.74% [49.40-61.54]), with higher removals for clinical deterioration, though similar waitlist death percentages (p=0.268).
Conclusions:
Low-volume centers demonstrated lower transplant rates, longer time to transplantation, and lower offer acceptance despite similar waitlist mortality, indicating lower realized access to transplantation among waitlisted candidates. These program-level associations warrant further investigation of candidate selection, offer availability, allocation pathways, and program resources before specific interventions are recommended.

Related Concept Videos
 01:28
Kidney Transplant I: Introduction
 01:26
Kidney Transplant II: Surgical Procedure
 01:24
Tissue Transplantation
The Biology of Tissue Transplantation
The biology of tissue transplantation hinges on the Major Histocompatibility Complex (MHC) molecules. These molecules...