Disease Severity and Frailty Capture Complementary Dimensions of Surgical Risk in Octogenarians with Acute Cholecystitis
Related Experiment Video
Updated: Oct 31, 2026
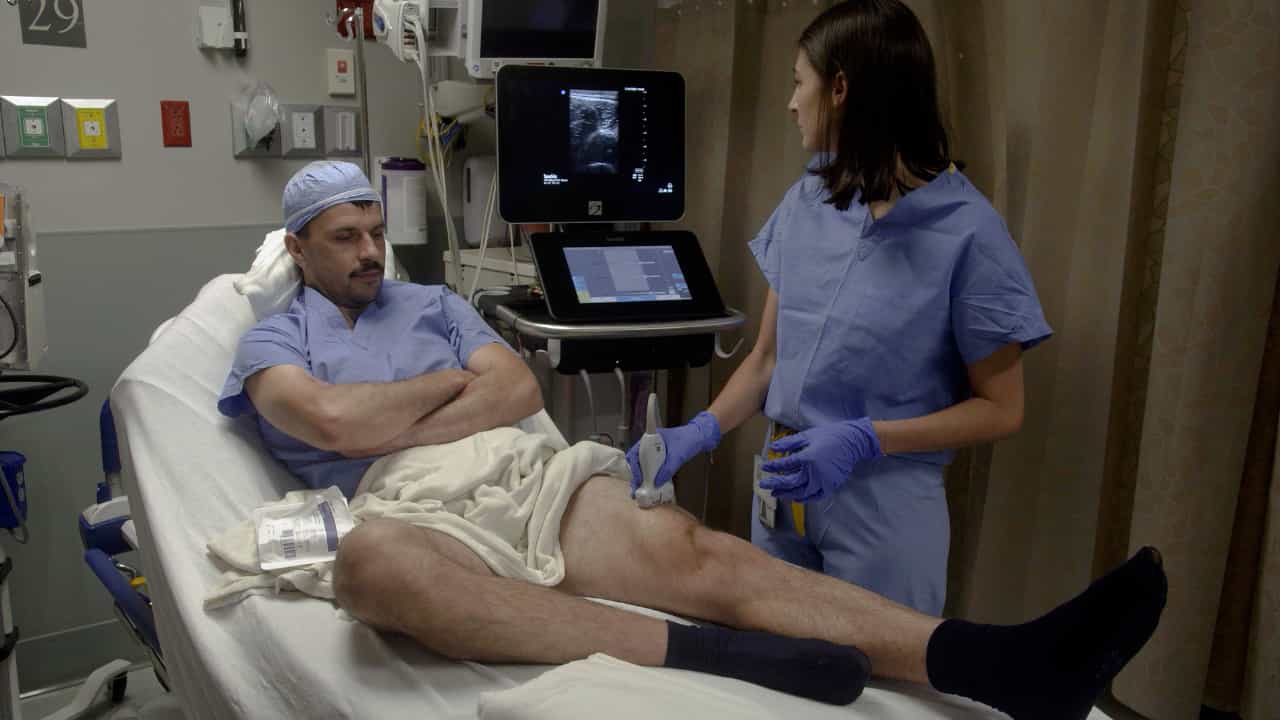
Identifying Frailty Using Point-of-Care Ultrasonography: Image Acquisition and Assessment
Published on: July 26, 2024
David Pinto1, Lena Anthuber1, David Farkas1
1Department of General, Visceral, Transplant and Thoracic Surgery, University Hospital Augsburg, Germany.

Background:
Age alone poorly characterizes perioperative risk in octogenarians with acute cholecystitis. Disease-specific severity, graded by the Tokyo Guidelines 2018 (TG18), and patient-level frailty, measured by the 5-item modified Frailty Index (mFI-5), may reflect different risk dimensions. We assessed their associations with severe morbidity and operative difficulty, whether they are complementary, and the incremental value of C-reactive protein (CRP).
Methods:
Retrospective single-center cohort of patients ≥80 undergoing cholecystectomy for acute cholecystitis within 7 days (2010-2025). The primary endpoint was severe postoperative morbidity (Clavien-Dindo ≥IIIa); the secondary endpoint was difficult cholecystectomy (conversion, bile duct injury, blood loss ≥500mL, or operative time ≥120min). Multivariable logistic regression modeled TG18, mFI-5 (per point), and CRP (per 5mg/dL); complementary information was assessed by nested likelihood-ratio (LR) tests.
Results:
Among 336 patients, severe morbidity occurred in 22.0% and in-hospital mortality in 6.3%. Both scores were independently associated with severe morbidity (mFI-5 OR 1.41, 95% CI 1.06-1.86; TG18 Grade III vs I OR 2.66, 1.25-5.62), and adding TG18 to mFI-5 improved model fit (LR p=0.033). Difficult cholecystectomy (34.8%) was associated with TG18 Grade II (OR 2.28, 1.36-3.81) but not with mFI-5 (LR p=0.970). CRP added no information (both LR p>0.20). Discrimination was poor across all models (AUC ≤0.64).
Conclusions:
In octogenarians, TG18 and mFI-5 capture complementary but non-equivalent dimensions of perioperative risk, TG18 relating to both morbidity and operative difficulty, frailty predominantly to postoperative vulnerability, whereas CRP adds little. Poor discrimination argues against using either as a standalone rule. Both should inform a multidimensional preoperative assessment.
