Feedforward neuromuscular control and dynamic postural stability in people with chronic ankle instability during single-leg landing
Related Experiment Video
Updated: Nov 3, 2026
Evaluating Postural Control and Lower-extremity Muscle Activation in Individuals with Chronic Ankle Instability
Published on: September 18, 2020
Tsz Yin Li1, Zhuoran Wang2, Reece Cascoe2
1National Centre for Sport and Exercise Medicine, School of Sport, Exercise and Health Sciences, Loughborough University, Loughborough, UK; Department of Sports Science and Physical Education, Faculty of Education, The Chinese University of Hong Kong, Hong Kong SAR, China.

Abstract:
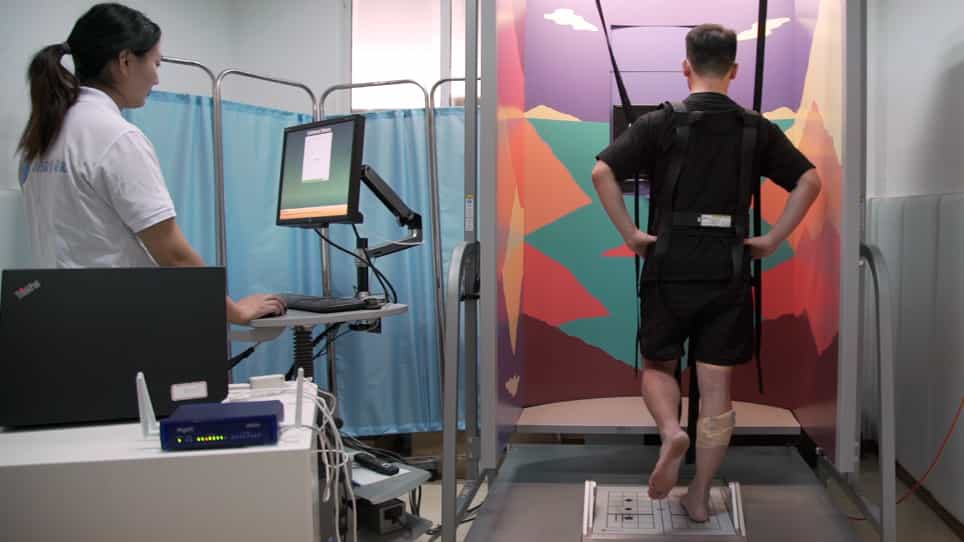
Individuals with chronic ankle instability(CAI) show deficits in neuromuscular control and postural stability. While feedback mechanisms are well-studied, feedforward mechanisms during dynamic tasks remains underexplored. This study compared feedforward neuromuscular control and dynamic postural stability among CAI, coper and healthy groups. Fifteen CAI(23.5 ± 2.9 years, 11 M/4F), fifteen coper(24.1 ± 3.4 years, 12 M/3F) and fifteen healthy participants(25.5 ± 3.5 years, 11 M/4F) performed single-leg drop landings from 30 cm. Total centre of pressure movement during 1-second and 3-second(TOTEX1s&TOTEX3s), mediolateral sway distance(DML), peak vertical GRF(peak vGRF) and root-mean-square of mediolateral GRF in the first 0.4 s(RMS_ML_0.4) were recorded via force plate. Surface electromyography recorded muscle activity 200 ms before landing among tibialis anterior(TA), peroneus longus(PL) and gastrocnemius lateralis(GL). Pre-activation timing was calculated using the Teager-Kaiser energy operator(TKEO). Statistical analysis involved one-way ANOVA(α = 0.05) and Tukey post-hoc testing. Compared to healthy participants, CAI individuals displayed earlier TA(270 ± 73 ms vs. 85 ± 53 ms, p < 0.001) and PL(260 ± 87 ms vs. 102 ± 62 ms, p < 0.001) pre-activations, alongside higher TA activity(76 ± 27% vs. 35 ± 19%, p < 0.001) but lower PL activity(38 ± 14% vs. 77 ± 23%, p < 0.001). Higher RMS_ML_0.4(6.7 ± 1.3%BW vs. 5.6 ± 1.0%BW, p = 0.037), DML(55.6 ± 15.7 mm vs. 39.5 ± 9.0 mm, p < 0.001) and peak vGRF(334 ± 44%BW vs. 286 ± 59%BW, p = 0.041)were observed as well. Coper showed earlier GL pre-activation(169 ± 57 ms vs. 108 ± 67 ms, p = 0.021), increased activity(155 ± 40% vs. 97 ± 29%, p < 0.001) and decreased DML(42.7 ± 7.0 mm vs. 55.6 ± 15.7 mm, p = 0.008) compared to CAI individuals. CAI exhibited postural control deficits and ineffective feedforward control, shown by lower PL activity despite early pre-activation. Rate of force production training is advised. Increased GL activation may serve as a compensatory response in copers after initial ankle sprain.