Related Experiment Video
Updated: Oct 22, 2026
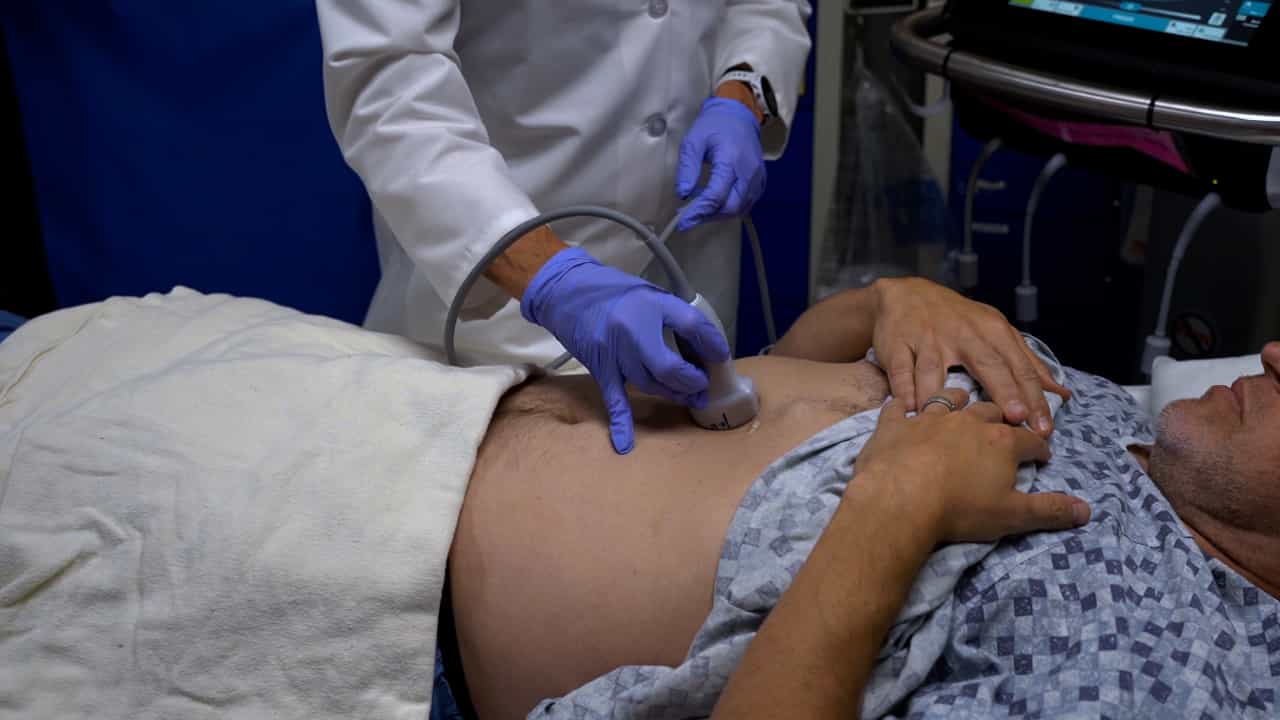
Gastric Point of Care Ultrasound in Adults: Image Acquisition and Interpretation
Published on: September 22, 2023
[Types of duodenal ulcer according to antrum function: its relation to the gastric acid secretory capacity and blood

Abstract:
A series of duodenal ulcer patients was studied to determine the relationship of the integrated postprandial gastrin response with the maximal acid secretory capacity, the ABO blood groups, age of onset of ulcer dyspepsia, and the family history of ulcer dyspepsia of the patients. It was found that: 1. The A, B, AB duodenal ulcer patients had a significantly higher maximal acid gastric secretory capacity (P less than 0.001), significantly earlier age of onset of ulcer dyspepsia (P less than 0.001) and significantly stronger family history of dyspepsia (P less than 0.05) than those patients with O blood group. 2. The integrated gastrin response was significantly higher in "hipersecreting" duodenal ulcer patients (secreted more than 25 mMol/h in response to histamine) than in "normosecreting" duodenal ulcer patients (secreted less than 25 mMol/h) (P less than 0.001) but the values for the latter were not different from normal subjects. 3. There was not statistical significant difference between the mean values of the basal serum gastrim levels of normosecreting duodenal ulcer patients, the hypersecreting duodenal ulcer patients and the normal subjects. 4. A significant positive correlation exists between the maximal acid output and integrated postprandial gastrin response in duodenal ulcer patients. (P less than 0.001). This correlation was negative in the normal subjects (P less than 0.01). 5. This finding supports the existence of a positive relationship between the functioning parietal cell and gastrin cell masses.
More Related Videos

Related Concept Videos
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:30
Peptic Ulcer Disease I: Introduction
An acute ulcer, marked by superficial erosion and minimal inflammation, swiftly resolves upon identifying and addressing the underlying cause. In contrast, a chronic ulcer persists, potentially eroding through the muscular wall and forming fibrous tissue.
Peptic ulcers can also be...
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:25
Peptic Ulcer Disease I: Introduction
 01:24
Peptic Ulcer Disease II: Pathophysiology